
Lisa Jacobson, MD
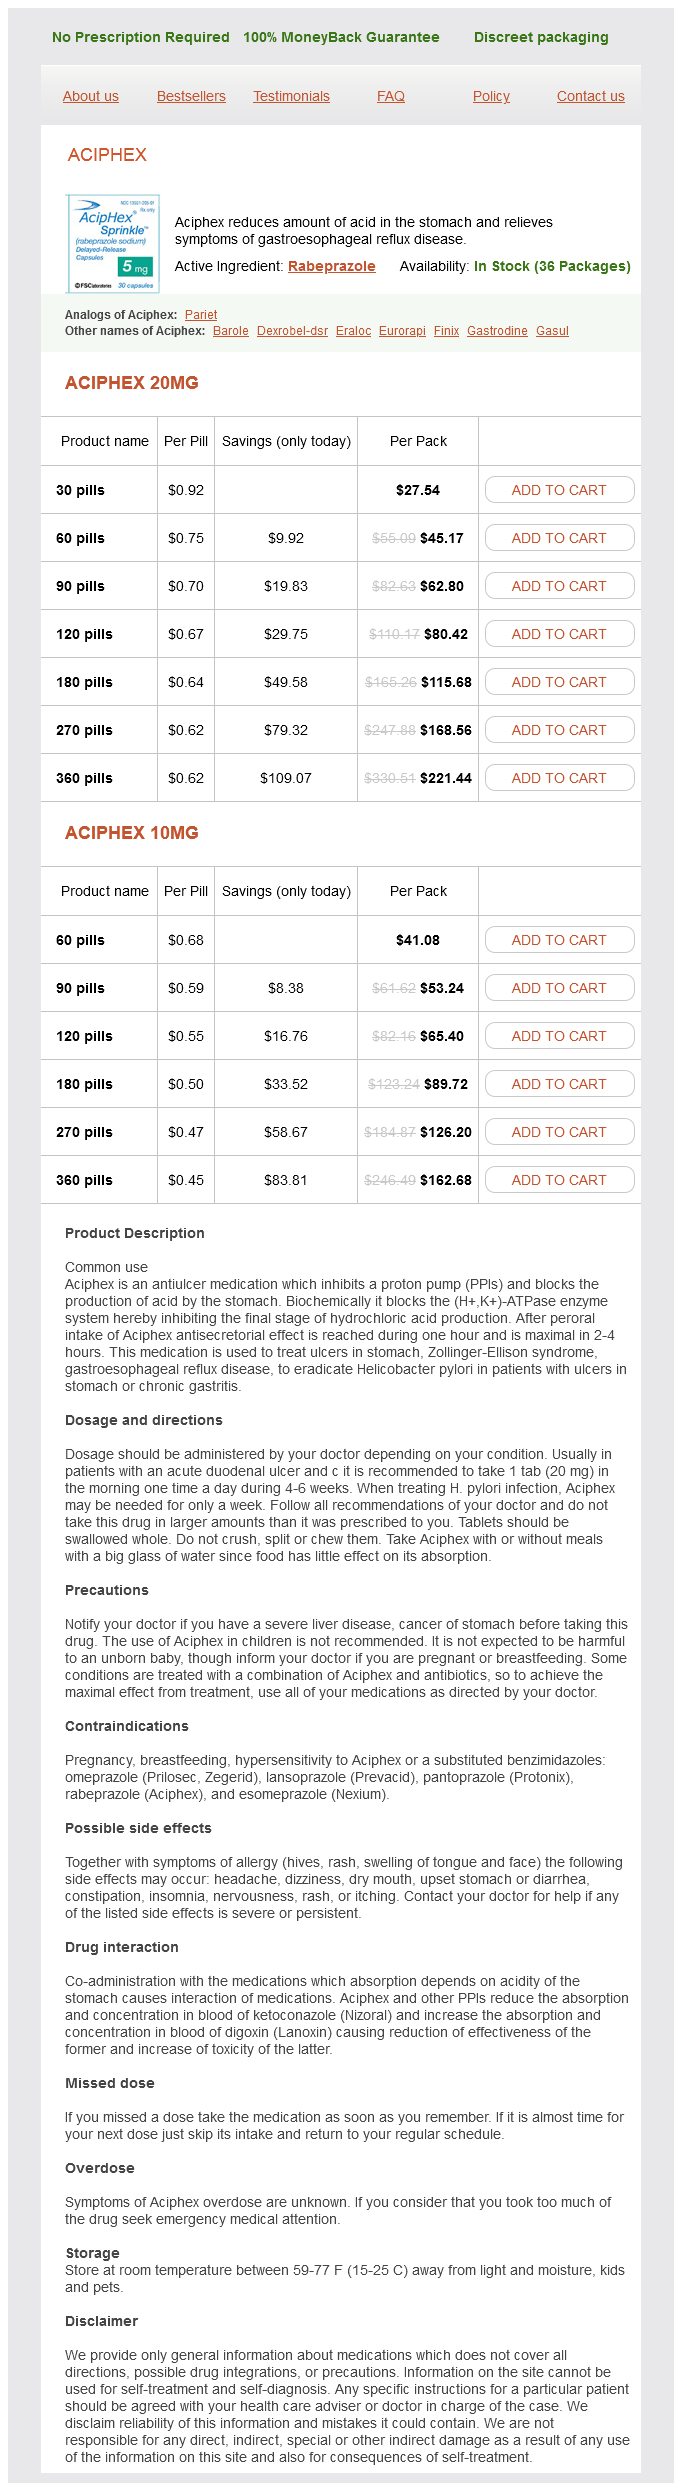
Aciphex dosages: 20 mg, 10 mg
Aciphex packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills

These effects of exogenous albumin are due to quantity growth, immunomodulation, and endothelial stabilization through enhance within the efficient albumin focus (Garcia-Martinez et al, 2013). Ascites will increase the risk of postoperative renal failure, infections, and wound dehiscence. Even if ascites is drained on the time of surgical procedure, it quickly reaccumulates in the postoperative period. Medical therapy, which includes salt restriction and diuretics, is usually thought-about first-line therapy. Blood transfusions have been comparatively minimal within the series, with a median of 3 items for abdominal operations (range, 0 to 21) and four models for cardiothoracic operations (range, zero to 20). Therefore shunts ought to probably be placed several weeks earlier than deliberate operations. In the Nineteen Eighties, charges of major morbidity and mortality in patients with cirrhosis present process cholecystectomy (see Chapter 35) had been as excessive as 35% and 25%, respectively (Aranha et al, 1982; Cryer et al, 1985; Garrison et al, 1984; Schwartz, 1981). A meta-analysis evaluating laparoscopic cholecystectomy in cirrhotic and noncirrhotic patients demonstrated significantly higher rates of morbidity (21% vs. Laparoscopic cholecystectomy presents improved visualization for meticulous dissection and avoids the necessity for a big subcostal or upper midline incision. It is related to less operative blood loss, shorter operative time, and decreased size of hospital stay versus the open process in cirrhotic patients (Puggioni & Wong, 2003). Metaanalysis evaluating laparoscopic and open approaches in cirrhotic sufferers discovered that laparoscopic cholecystectomy appeared to be associated with shorter operative time, decreased complication charges, and reduced size of hospital stay (Laurence et al, 2012). Some specific technical concerns must be thought-about when performing laparoscopic cholecystectomy in a cirrhotic affected person (see Chapter 35). In inserting the umbilical port, specific care have to be taken to keep away from venous collaterals and the umbilical vein. One approach may be to place one of the other ports first, such as the subxiphoid port, after which place the umbilical port under direct visualization. Transillumination of the stomach wall helps the surgeon to avoid these and other venous collaterals during trocar placement. Furthermore, the subxiphoid port ought to be positioned off midline to keep away from the falciform ligament and the recanalized umbilical vein. A subtotal or supracystic cholecystectomy, leaving a half of the gallbladder wall hooked up to the liver mattress and ligating the cystic duct from throughout the gallbladder with a purse-string suture, is an option in patients with giant pericholecystic venous collaterals (Bornman & Terblanche, 1985) (see Chapter 33). Trocars also needs to be removed beneath direct visualization to ensure enough stomach wall hemostasis at the end of the procedure. Finally, if anatomy is unclear or any doubt exists as to the security of continuous laparoscopically, the procedure should be transformed to open. Despite the shortage of controlled trials, the literature supports using alternatives to cholecystectomy, corresponding to a percutaneous cholecystostomy, in this high-risk group (Curro & Cucinotta, 2006; Delis et al, 2010; Yeh et al, 2002). In patients with class C cirrhosis, surgical procedure ought to be deferred until liver illness is better compensated, and alternate interventions, similar to percutaneous cholecystostomy or endoscopic stenting, ought to be used both as definitive remedy or as a bridge to cholecystectomy underneath higher circumstances. Herniorrhaphy Umbilical hernias occur in as many as 20% of sufferers with cirrhosis. The pathogenesis of umbilical hernias within the setting of cirrhosis is multifactorial; ascites causes elevated intraabdominal pressure, poor dietary standing results in decreased abdominal muscle mass and fascial power, and umbilical vein dilation results in enlargement of the preexisting supraumbilical fascial opening (Belghiti & Durand, 1997). In addition to the dangers of bowel incarceration and strangulation that have an result on all sufferers with umbilical hernias, additional distinctive dangers accompany having an umbilical hernia and cirrhosis. Skin ulceration over the hernia could also be associated with the leakage of ascites, sac rupture, bacterial peritonitis, and even evisceration, with very high attendant rates of morbidity and mortality. Although uncommon, spontaneous umbilical rupture is related to as high as a 60% perioperative mortality fee and has been proven to correlate independently with an opposed outcome after emergent repair (Telem et al, 2010). Most sequence published in the literature for the rationale that early 1980s have reported little to no perioperative deaths and relatively low morbidity, although most of them have been comparatively small retrospective studies (Belghiti et al, 1990; de la Pena et al, 2000; Ozden et al, 1998; Runyon & Juler 1985). In contrast, in the group that was observed, problems developed in 10 patients (77%), D. Several different studies have discovered increased problems of patients treated emergently and advocate for elective restore of suitable sufferers not anticipating imminent liver transplantation (Choi et al, 2011; Eker et al, 2011). It is, nonetheless, an necessary consideration in the management of ascites in sufferers into account for hernia repair.
Diseases

Cox H, et al: Well differentiated intrahepatic cholangiocarcinoma in the setting of biliary papillomatosis: a case report and evaluate of the literature, Can J Gastroenterol 19:731�733, 2005. Cuschieri A, et al: Hepatic cryotherapy for liver tumors: improvement and medical analysis of a high-efficiency insulated multineedle probe system for open and laparoscopic use, Surg Endosc 9:483�489, 1995. Donato F, et al: Intrahepatic cholangiocarcinoma and hepatitis C and B virus an infection, alcohol intake, and hepatolithiasis: a case control examine in Italy, Cancer Causes Control 12:959�964, 2001. Ebata T, et al: Portal vein embolization earlier than prolonged hepatectomy for biliary most cancers: current method and evaluate of 494 consecutive embolizations, Dig Surg 29:23�29, 2012. Eckel F, Schmid R: Chemotherapy in advanced biliary tract carcinoma: a pooled analysis of medical trials, Br J Cancer 96:896�902, 2007. Endo I, et al: Intrahepatic cholangiocarcinoma: rising frequency, improved survival, and determinants of outcome after resection, Ann Surg 248:84�96, 2008. Ercolani G, et al: Intrahepatic cholangiocarcinoma: primary liver resection and aggressive multimodal treatment of recurrence considerably delay survival, Ann Surg 252:107�114, 2010. Fujita T: Clinicopathological research of the resected intrahepatic bile duct carcinoma, Jpn J Gastroenterol Hepatol 23:36�46, 1990. Ghiringhelli F, et al: Hepatic arterial infusion of gemcitabine plus oxaliplatin as second-line treatment for locally advanced intrahepatic cholangiocarcinoma: preliminary experience, Chemotherapy 59:354� 360, 2013. Glazer E, et al: Neither neoadjuvant nor adjuvant remedy will increase survival after biliary tract most cancers resection with wide unfavorable margins, J Gastrointest Surg sixteen:1666�1671, 2012. Goto N, et al: Intrahepatic cholangiocarcinoma arising 10 years after the excision of congenital extrahepatic biliary dilatation, J Gastroenterol 36:856�862, 2001. Gruenberger B, et al: Cetuximab, gemcitabine and oxaliplatin in patients with unresectable advanced or metastatic biliary tract cancer: a Phase 2 research, Lancet Oncol 11:1142�1148, 2010. Gu M, Choi J: Epithelial-mesenchymal transition phenotypes are related to patient survival in intrahepatic cholangiocarcinoma, J Clin Pathol 67:229�234, 2014. Guglielmi A, et al: Intrahepatic cholangiocarcinoma: prognostic factors after surgical resection, World J Surg 33:1247�1254, 2009. Guglielmi A, et al: Patterns and prognostic significance of lymph node dissection for surgical therapy of perihilar and intrahepatic cholangiocarcinoma, J Gastrointest Surg 17:1917�1928, 2013. Hakamada K, et al: Late development of bile duct cancer after sphincteroplasty: a ten- to twenty-two-year follow-up research, Surgery 121:488�492, 1997. Harewood G: Endoscopic tissue prognosis of cholangiocarcinoma, Curr Opin Gastroenterol 24:627�630, 2008. Hezel A, Zhu A: Systemic therapy for biliary tract cancers, Oncologist 13:415�423, 2008. Hyder O, et al: Intra-arterial therapy for advanced intrahepatic cholangiocarcinoma: a multi-institutional analysis, Ann Surg Oncol 20: 3779�3786, 2013. Isaji S, et al: Clinicopathological features and outcome of hepatic resection for intrahepatic cholangiocarcinoma in Japan, J Hepatobiliary Pancreat Surg 6:108�116, 1999. Ishimura N, et al: Inducible nitric oxide synthase upregulates cyclooxygenase-2 in mouse cholangiocytes promoting cell growth, Am J Physiol Gastrointest Liver Physiol 287:G88�G95, 2004. Ismail T, et al: Primary hepatic malignancy: the position of liver transplantation, Br J Surg seventy seven:983�988, 1990. Ito K, et al: Adequate lymph node assessment for extrahepatic bile duct adenocarcinoma, Ann Surg 251:675�681, 2010. Kasai K, et al: Efficacy of hepatic arterial infusion chemotherapy using 5-fluorouracil and systemic pegylated interferon -2b for superior cholangiocarcinoma, Ann Surg Oncol 21:3638�3645, 2014. Kawarada Y, et al: Analysis of the connection between clinicopathological factors and survival time in intrahepatic cholangiocarcinoma, Am J Surg 183:679�685, 2002. Kaya M, et al: Treatment of cholangiocarcinoma complicating major sclerosing cholangitis: the Mayo Clinic expertise, Am J Gastroenterol ninety six:1164�1169, 2001. Kiefer M, et al: Chemoembolization of intrahepatic cholangiocarcinoma with cisplatinum, doxorubicin, mitomycin C, ethiodol and polyvinyl alcohol: a 2 middle research, Cancer 117:1498�1505, 2011. Kuhlmann J, et al: Treatment of unresectable cholangiocarcinoma: conventional transarterial chemoembolization in contrast with drugeluting bead-transarterial chemoembolization and systemic chemotherapy, Eur J Gastroenterol Hepatol 24:437�443, 2012. Lai G, et al: erbB-2/neu erbB-2/neu reworked rat cholangiocytes recapitulate key mobile and molecular options of human bile duct most cancers, Gastroenterology 123:2047�2057, 2005. Lamade W, et al: the influence of third-dimensional reconstruction on operative planning in liver surgical procedure, Arch Surg one hundred thirty five:1256�1261, 2000.

Recent advances within the genomic landscape of this tumor have also contributed to characterizing dysregulation in specific pathways and with prognostic features (Eichenmuller et al, 2014; Jia et al, 2014). Both groups are primarily observed in younger girls, usually within the context of oral contraception and develop in an otherwise normal liver. The combined hepatoblastomas combine the epithelial component with mesenchymal-derived tissues of assorted differentiations. Usually, this consists of osteoid-like material, sometimes focally calcified, or primitive spindle cells occurring in fasciculated or free myxoid preparations. Rarely, trabecular bone formation or cartilaginous or rhabdomyoblastic differentiation is identified. Hepatoblastoma is an aggressive neoplasm that invades locally and spreads to regional lymph nodes, lungs, adrenal glands, brain, and bone marrow. Once stage is taken under consideration, the varied histologic subtypes turn into less essential prognostic indicators (Conran et al, 1992). However, complications similar to rupture or bleeding are distinctive, and no proof of malignant transformation has been reported thus far. Heterogeneous areas of necrosis and/or hemorrhage may be noticed, normally in tumors of large size. Hepatocytes are organized in a trabecular pattern with none residual portal tracts. Hepatocytes are normally normal, organized in regular or mildy thickened plates without cytologic atypia lined by a well-preserved sinusoidal framework. Externalviewofasuperficial tumor bulging beneath the capsula, with giant subcapsular and dilated vessels. Soft,well-delineatedtumor with little or no fibrous capsule and small heterogeneous foci of hemorrhage. Vascular modifications, including sinusoidal dilation, peliosis, infarcts, and hemorrhage are frequent. These modifications might go away edematous or fibrotic areas, typically with hemosiderin-laden macrophages. Nevertheless, these tumors share the same medical and imaging traits independently of their number (Dokmak et al, 2009; Lewin et al, 2006). The three major morphologic patterns of liver adenomatosis have been described: the steatotic type, the peliotic/telangiectatic kind, and the combined kind (Lewin et al, 2006). Histologically, the hepatocellular proliferation contains small clusters of arteries embedded in collagen, usually associated with an inflammatory infiltrate (lymphocytes and macrophages) and infrequently ductular proliferation. In addition, foci of sinusoidal dilation and peliotic changes are often present. It is the second most frequent main malignant tumor of the liver (5% to 15% of liver main malignancies) (Malhi et al, 2006; Welzel et al, 2006). Hepatholithiasis (see Chapter 39), cholelithiasis (see Chapter 32), cholangitis (see Chapter 43), chronic pancreatitis (see Chapter 57), and exposure to Thorotrast are also risk components (Chapman, 1999; Kim et al, 2015; Lipshutz et al, 2002). In the intraductal progress sort, tumor usually spreads intraluminally along the ducts. Bloodborne unfold happens later, particularly to the lungs (Jiang et al, 2009; Patel, 2001; Suzuki et al, 2002). These patterns are associated with totally different clinical evolutions, with intraductal development and the periductal infiltration exhibiting the most effective and worst prognosis, respectively (65% survival at 5 years in contrast with lower than 5% at 5 years) (Jiang et al, 2009; Rizvi et al, 2014; Suzuki et al, 2002). In case of enormous tumors, adjacent satellite tv for pc tumoral nodules are generally noticed. The pure periductal-infiltrating type and the intraductal growth pattern are seldom noticed (Guglielmi et al, 2009). Cytoplasm is often pale, barely eosinophilic, and generally more abundant and clear. Mucus secretion may be highlighted by alcian blue staining, though the amount is usually small. Less differentiated tumors could show cribriform formations and/or a cordlike sample, and poorly differentiated cancers are characterised by marked cellular pleomorphism. Usually, the center of the tumor is densely sclerotic and hypocellular, and there may be focal calcifications, whereas the periphery of the tumors is extra cellular. Grossmacroscopy of a small and solitary, well-limited, unencapsulated white tumor developedonacirrhoticliver.

A relatively low but growing incidence is present in Western Europe, the United States, Canada, and Scandinavia (Bosch et al, 2004; El-Serag et al, 2014; Khan 1272 et al, 2002; Seeff et al, 2006). In addition, regardless of very effective therapy for viral hepatitis, the risk for most cancers nonetheless persists in hepatitis C following viral eradication and remains important in hepatitis B (Moon et al, 2015; Papatheodoridis et al, 2015). It happens extra regularly in men than women, with a male/female ratio ranging from 2: 1 to 9: 1, though the cause being not clear (El-Serag et al, 2008). This remark is very according to a multistep process that means progressive malignant transformation of preneoplastic lesions, such as macroregenerative and dysplastic cirrhotic nodules. This progression parallels additionally the rising accumulation of genetic and epigenetic abnormalities in liver cells, from regenerative to malignant nodules (see Chapter 9D). General Chapter 89 Tumors of the liver: pathologic features 1273 nodules bigger than 1. Indeed, its morphologic patterns are varied, beyond the classic classification, based on progress sample and tumor differentiation. Several macroscopic classifications have been proposed, however their medical relevance has not but been confirmed. Presence of distorted hepatic vessels, together with arteries, forming curved buildings on the floor of the tumor mass or seen on the reduce surface, support the concept of an increasing growing sample. Nodule may be solitary or a quantity of throughout the liver when developed as a complication of cirrhosis. Such a distinction is type of inconceivable based on a pathology examine alone however could be addressed with surrogate molecular analysis (Paradis et al, 1998; Sakamoto et al, 1989). The prognostic significance of capsule formation has not yet been definitively settled. This gross classification has limitations because categorization of a tumor within one single progress sample may be difficult. Vascular invasion must be determined with care on the preliminary gross examination (macrovascular invasion). In some instances, intravascular tumor plugs in the shut periphery of a big tumor could also be troublesome to distinguish from satellite tumor nodules. Invasion of enormous bile ducts producing biliary obstruction and hemobilia might be often discovered. In this sample, tumor consists in a number of unconnected small tumors of roughly related size. For nodules smaller than 1 cm, biopsy is generally not beneficial because of its limited performance. These diagnostic standards have been endorsed by most international liver diseases associations (Bruix et al, 2001, 2005). Nevertheless, and regardless of the most important advances in radiologic procedures, the definitive analysis continues to be primarily based typically primarily on accurate examination and interpretation of histologic materials for any small or atypical nodule. Therefore the microscopic evaluation entails the assessement of cytologic traits of tumoral cells and analysis of their architectural pattern (Paradis, 2013; Schlageter et al, 2014). Tumoral cells could current varying levels of hepatocellular differentiation within a single tumor. Nuclei are normally basophilic, often irregular with outstanding nucleoli and a high nuclear/cytoplasmic ratio. Bile canaliculi can often be seen by gentle microscopy or demonstrated by immunostaining. When dilated, they may comprise bile pigment, a attribute characteristic of hepatocellular differentiation. Mallory-Denk bodies, hyaline globules, or eosinophilic ground-glass�like cytoplasmic inclusions can additionally be observed (Salomao et al, 2010). While the tumor evolves to a poorly differentiated phenotype, cell-to-cell heterogeneity, bizarre nuclei, or large tumoral cells may appear. Growth Patterns the arrangement of the cells contributes to the variety of microscopic appearances.
Black Catechu (Catechu). Aciphex.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96408

The right hepatic duct is typically shorter than the left (see Chapter 2); in consequence, tumor is more prone to lengthen to and isolate the best anterior and posterior sectoral ducts, while the left medial and lateral sectors continue to talk. In such instances, it could be Psychological Preparation A thorough discussion of potential outcomes is especially necessary before biliary drainage in patients with high bile duct obstruction. Patients should perceive that, although each effort might be made to set up internal drainage with stents, this is probably not achieved. Two or extra catheters or self-expanding stents could also be required when the tumor extends past the secondary confluence on one facet or the opposite, relying on the scientific objective. Even in the presence of segmental isolation, pruritus usually resolves after biliary drainage. In sure situations, two or extra biliary drainage catheters may be placed without a significant decrease in bilirubin; generally, the bilirubin may even improve. It also is conceivable that intervening cholangitis or progression of illness might play a task. Patients with ascites are less prone to have leakage round a left anterior catheter, so a left approach is most popular when possible. When atrophy or compromise of the portal vein is current, the patient will at all times derive more benefit from drainage of the contralateral practical liver, as beforehand mentioned. Image Guidance In most cases, biliary drainage is carried out with fluoroscopic guidance. Ultrasound is often used for duct puncture from a left-sided approach; but less often from the proper as a end result of bile duct orientation and the necessity to picture via an intercostal house make the use of ultrasound more challenging. This evaluate is especially essential when isolation is suspected and the target is to goal a specific duct. Previously positioned stents, surgical clips, or different radiopaque landmarks can regularly be used to facilitate focusing on. To permit for both basic anesthesia or aware sedation, sufferers take nothing by mouth for six hours earlier than the procedure. They are well hydrated and have practical venous entry, significantly if cholangitis is part of the medical picture. These sufferers can turn into septic and hypotensive, requiring fast volume enlargement. The ability to scan the liver in a single breath maintain and then cine through the images facilitates identification of the level of obstruction and the probability of isolation (see Chapter 18). It also enables the formulation of a 3D mental image of the biliary tree, and understanding the biliary anatomy on this method facilitates a successful, uncomplicated process. It is frequently attainable to anticipate normal variants of bile duct anatomy, which may have a big impact on preprocedure planning (see Chapter 2). Drainage Catheter Versus Primary Stent Placement the suitability of a affected person for main stent placement is decided on the time of biliary drainage based mostly on the indication for the drainage, evidence of contaminated bile, presence of blood or tumor inside the biliary tree, and cholangiographic findings. In sufferers with a presumed sterile biliary tree, an try ought to be made to accomplish this with out ever putting a drainage catheter into the duodenum. Blood clot inside the intrahepatic bile ducts impairs drainage and can cause stent obstruction that will end in bile leaking into the peritoneal cavity from the positioning of duct puncture. When clots are visible within the biliary tree (see Chapter 125), a drainage catheter is positioned until the bile clears, at which era the patient is stented. Catheter manipulation in this group of sufferers is kept to a minimum to diminish the chance of procedure-related sepsis. Predictions concerning the degree of obstruction and degree of isolation of the biliary tree could be made primarily based on the preprocedure imaging research. Patients with Bismuth kind I obstruction can have the complete liver drained with one catheter or stent, as a result of right and left ducts talk freely. Barring one of the previously talked about contraindications, these patients have a primary stent positioned. Some suggest that survival is best when each side of the liver are drained (Chang et al, 1998). In both case, we choose to stent into the frequent bile duct and not into the duodenum if potential so as to preserve function of the sphincter of Oddi. One benefit of the more anatomic Y-shaped configuration stent placement is that if stent occlusion occurs, both stents are approachable endoscopically. In this case, and in the absence of some other contraindication, a patient being drained for pruritus alone may need a primary stent positioned, because only a small portion of the liver must be drained to alleviate pruritus.
An power coagulation system can be utilized instead of, or along with, clips as properly. This separation of the splenic vein from the pancreas can only proceed within the direction toward the spleen as a end result of the vein has already branched into small vessels that can simply be injured on the stage of the splenic hilum. Iacono and colleagues (1998) succinctly summarized the stipulations that allow segmental pancreatectomy to be considered as an inexpensive strategy: small lesions (<5 cm in diameter) (1) which may be benign or low-grade malignant tumors (2), situated within the neck or its contiguous portion (3), and a distal pancreas stump of at least 5 cm in size (4). A crucial adjunct is the provision of frozen-section examination to verify that the lesion is benign or indolent and to confirm a free resection margin (M�ller et al, 2006). Technique the lesser sac is entered, and the anterior facet of the pancreas is broadly uncovered by dividing the adhesions between the posterior floor of the stomach and the pancreas. This is adopted by intraoperative pancreatic ultrasonography to better delineate the lesion and to exclude concomitant lesions which will necessitate a change of plan. Stay sutures are positioned within the superior and inferior pancreatic margins to point out the proximal and distal limits of division and to assist within the subsequent dissection of the pancreas from the splenic vein. The pancreas is then divided proximally, both with a vascular stapler or sharply with a scalpel, no much less than 1 cm to the best of the lesion. If divided sharply, the proximal stump is sealed with interrupted horizontal mattress sutures as described beforehand. The distal stump is then gently retracted toward the left to enable the cautious and tedious means of releasing the splenic vein from the posterior surface, controlling all of the fantastic venous tributaries lying between the splenic vein and the pancreas. The pancreas must be mobilized off the splenic vessels for a minimum of a distance of two to three cm to the left of the planned distal transection aircraft to facilitate reconstruction. The pancreas is then divided distal to the lesion with a scalpel, and the specimen is distributed for analysis and margin evaluation. Our typical technique of reconstruction of the distal stump is to trend a pancreaticogastrostomy utilizing a dunking, invagination technique. Four to six traction sutures, two to three on all sides of the duct, are placed alongside the pancreatic transection edge. The site of the anastomosis is selected and marked along the posterior wall of the stomach, being careful to account for the area wanted for the pancreas to be flipped anteriorly contained in the stomach. A small posterior gastrotomy is then made to the proper of this suture line, limiting it to about 75% of the width of the pancreas to allow a snug match of the pancreas contained in the stomach. These sutures are held on traction to preserve the pancreas inside the stomach while seromuscular sutures on the stomach are placed vascular sutures. If attempts at hemostasis of such vascular injuries are unsuccessful, we divide the splenic pedicle. We keep away from mobilizing the spleen medially into the operative field, as this step is unnecessary and carries the risk of iatrogenic splenic harm. If the vessels need to be divided due to intraoperative bleeding or inability to separate the pancreas, and a call must be made to allow the spleen to perfuse on the brief gastric vessels or to just convert to a splenectomy, then the authors prefer the latter. Segmental (Central) Pancreatectomy Letton and Wilson (1959) have been the primary to describe the strategy of segmental, or central, pancreatectomy for two cases of traumatic transection of the pancreatic isthmus. Following a central segmental resection, the proximal stump was oversewn, and a Roux-en-Y jejunal limb was constructed and anastomosed to the distal stump. Benign or low-malignancy tumors arising from this region present a unique problem. Such operative strategies for a small lesion come at the price of a major lack of regular pancreatic tissue, along with the inherent risk of morbidity and mortality that accompanies such prolonged pancreatectomies. Perhaps essentially the most beneficial attraction appears to be the excellent preservation of endocrine perform. On the other hand, the prime concern when performing a central pancreatectomy is whether or not pancreatic fistula rates are considerably higher as a result of two attainable sources of pancreatic leakage, particularly, a pancreatic stump and D. The anterior gastrotomy is then closed, which may normally be achieved with a single sew. This technique permits the pancreas to be dunked inside the stomach in a tension-free manner.

In such sufferers, the distal splenorenal shunt may worsen ascites rather than relieve it. Hepatic Cirrhosis, Portal Hypertension, and Hepatic Failure Chapter eighty five Portal hypertensive bleeding: the place of portosystemic shunting 1225 goal of preserving hepatic operate better than nonselective shunts remains controversial. Controlled trials have shown decreased portosystemic encephalopathy after the distal splenorenal shunt. Henderson and colleagues (1983) confirmed that portal flow is maintained in most patients with nonalcoholic cirrhosis and noncirrhotic portal hypertension, but portal circulate quickly collateralizes to the shunt in patients with alcoholic cirrhosis, particularly if alcohol consumption continues. Despite surgical interruption of collaterals that join the superior mesenteric venous system to the gastrosplenic system, collaterals gradually develop via a pancreatic network termed the pancreatic siphon. A distal splenorenal shunt requires a patent splenic vein, preferably no less than 7 mm in diameter. Six of seven controlled trials evaluating the distal splenorenal shunt with nonselective shunts have evaluated alcoholic cirrhotic sufferers and have been summarized by Jin and Rikkers (1991). Four of the seven trials confirmed less encephalopathy after a selective shunt, whereas the opposite trials confirmed no difference in encephalopathy rates. When the distal splenorenal shunt was in contrast with repeated endoscopic therapy, rebleeding was less frequent with selective shunts, but hepatic portal perfusion was better maintained by sclerotherapy. Encephalopathy charges were comparable in both groups (Henderson et al, 1990; Rikkers et al, 1993). Another indication for surgical procedure, rather than sclerotherapy, is poor entry to superior medical care. Such patients profit from an initial selective shunt, quite than long-term sclerotherapy, as a result of the latter requires a quantity of visits to a medical middle. Small-diameter H-graft shunting was encouraged in those patients who have been neither eligible nor suitable for liver transplantation (Rosemurgy et al, 2007). Side-to-side shunts have the benefit of relieving ascites by decreasing intrahepatic sinusoidal pressure in addition to reducing the portal venous pressure gradient. They are also efficient in decompressing varices and preventing recurrent variceal bleeding. Portacaval shunts involving dissection within the hilum of the liver inevitably end in postoperative scarring within the hilum and make subsequent liver transplantation more difficult, with the added potential morbidity and mortality. Nevertheless, liver transplantation in patients with previous portacaval shunts may be accomplished safely. A side-to-side portacaval shunt is carried out via a transverse upper abdominal incision. A venotomy is made longitudinally in every vein approximately 2 cm in length, and keep sutures of 6-0 polypropylene are positioned on the corners. These stay sutures are tied down, and the anastomosis is performed with a running technique. Partial Shunt the partial shunt proposed by Sarfeh and colleagues (1986) is a way of decompressing varices whereas preserving hepatic portal perfusion. A prospective randomized trial of partial (8-mm diameter) and nonselective (16-mm diameter) interposition portacaval shunts showed a decrease frequency of encephalopathy after the partial shunt, however related survival was reported after each types of shunts (Sarfeh & Rypins, 1994). The largest sequence of partial shunts was reported by Rosemurgy and colleagues (2007) and contains one hundred seventy patients older than 18 years. The accomplished anastomosis normalizes portal pressures and leads to hepatofugal blood move through the shunt. We have had no problems from removing of 1 internal jugular vein and have had no shunt thromboses. An incision similar to a carotid endarterectomy incision is made along the anterior border of the sternocleidomastoid muscle. Branches are doubly ligated and divided, and the jugular vein is dissected free from the clavicle to the mastoid. Flow must be 1 to 2 L/min, and considerably decrease flow charges should immediate inspection of the graft for technical problems. The significant advantage of the meso-Rex shunt is that it restores portal blood circulate to the liver and relieves portal hypertension, a super combination that will protect liver integrity and function long run. This shunt is more commonly utilized in kids, although selected adults might profit as nicely. Distal Splenorenal Shunt A distal splenorenal shunt is carried out via a transverse upper stomach incision (see Chapter 86). The gastrocolic omentum is taken down such that the right gastroepiploic vein is split, however the short gastric veins are left intact.

Other priorities for these sufferers are administration of capsular pain and ascites and maintenance of sufficient dietary consumption. They constitute 10% of main hepatic tumors, and although many are sporadic, conditions leading to persistent inflammation of biliary epithelium represent significant danger components for his or her growth. A specific staging system has been developed, and for patients with liver-only illness, R0 resection presents the prospect of remedy in 20% to 30%. Alvaro D: Serum and bile biomarkers for cholangiocarcinoma, Curr Opin Gastroenterol 25:279�284, 2009. Alvaro D, et al: Serum and biliary insulin-like progress factor 1 and vascular endothelial progress consider figuring out the cause of obstructive cholestasis, Ann Intern Med 2:451�459, 2007. Andersen J, et al: Genomic and genetic characterization of cholangiocarcinoma identifies therapeutic targets for tyrosine kinase inhibitors, Gastroenterology 142:1021�1031, 2012. Ayaru L, et al: Diagnosis of pancreatobiliary malignancy by detection of minichromosome upkeep protein 5 in bile aspirates, Br J Cancer 6:1548�1554, 2008. Berquist A, Broome U: Hepatobiliary and extra-hepatic malignancies in main sclerosing cholangitis, Best Pract Res Clin Gastroenterol 15:643�656, 2001. Bergquist A, et al: Risk factors and medical presentation of hepatobiliary carcinoma in sufferers with major sclerosing cholangitis, Hepatology 27:311�316, 1998. Bhudhisawasdi V, et al: Evaluation of postoperative adjuvant chemotherapy for intrahepatic cholangiocarcinoma sufferers undergoing R1 and R2 resections, Asian Pac J Cancer Prev 13(Suppl):169�174, 2012. Burger I, et al: Transcatheter arterial chemoembolization in unresectable cholangiocarcinoma: preliminary experience in a single institution, J Vasc Interv Radiol 16:353�361, 2005. Case Records of the Massachusetts General Hospital: N Engl J Med 304:893�899, 1981. Characharoenwitthaya P, et al: Utility of serum tumour markers, imaging and biliary cytology for detecting cholangiocarcinoma in major sclerosing cholangitis, Hepatology 48:1106�1117, 2008. Cherqui D, et al: Intrahepatic cholangiocarcinoma: outcomes of aggressive surgical remedy, Arch Surg a hundred thirty:1073�1078, 1995. Chu K, et al: Malignancy associated with hepatolithiasis, Hepatogastroenterology 44:352�357, 1997. Chung V: Systemic remedy for hepatocellular carcinoma and cholangiocarcinoma, Surg Oncol Clin N Am 24:187�198, 2015. Single middle experience with 27 resections in 50 sufferers over a 5-year interval, Ann Surg 241:134�143, 2005. Lang H, et al: Operations for intrahepatic cholangiocarcinoma: singleinstitution expertise of 158 sufferers, J Am Coll Surg 208:218�228, 2009. Lempinen M, et al: Enhanced detection of cholangiocarcinoma with serum trypsinogen-2 in patients with severe bile duct strictures, J Hepatol 47:677�683, 2007. Lesurtel M, et al: Intrahepatic cholangiocarcinoma and hepatolithiasis: an unusual association in Western countries, Eur J Gastroenterol Hepatol 14:1025�1027, 2002. Liu L, et al: Serum ranges of variants of transthyretin downregulation in cholangiocarcinoma, J Cell Biochem 104:745�755, 2009. Liver Cancer Study Group of Japan: Primary liver most cancers in Japan: clinicopathologic features and outcomes of surgical treatment, Ann Surg 211:277�287, 1990. Liver Cancer Study Group of Japan: General guidelines for the scientific and pathological examine of main liver most cancers, ed 2, Tokyo, 2003, Kanehara. Lumachi F, et al: Measurement of serum carcinoembryonic antigen, carbohydrate antigen 19-9, cytokeratin-19 fragment and matrix metalloproteinase-7 for detecting cholangiocarcinoma: a preliminary case-control research, Anticancer Res 34:6663�6667, 2014. Luo X, et al: Survival outcomes and prognostic factors of surgical therapy for all potentially resectable intrahepatic cholangiocarcinoma: a large single-center cohort study, J Gastrointest Surg 18:562� 572, 2014. MacDonald O, Crane C: Palliative and postoperative radiotherapy for biliary tract cancer, Surg Oncol Clin N Am eleven:941�954, 2002. Manfredi R, et al: Magnetic resonance imaging of cholangiocarcinoma, Semin Liver Dis 24:155�164, 2004. Marcos L, et al: Update on hepatobiliary flukes: fascioliasis, opisthorchiasis and clinorchiasis, Curr Opin Infect Dis 21:523�530, 2008. Marumoto M, et al: Systemic gemcitabine mixed with hepatic arterial infusion chemotherapy with cisplatin, 5-fluorouracil and isovorin in the treatment of advanced intrahepatic cholangiocarcinoma: a pilot research, Hepatogastroenterology sixty one:162�167, 2014. Morris-Stiff G, et al: Cholangiocarcinoma complicating major sclerosing cholangitis: a 24 yr experience, Dig Surg 25:126�132, 2008.

Eisenberg E, et al: Neurolytic celiac plexus block for therapy of most cancers pain: a meta-analysis, Anesth Analg 80:290�295, 1995. Fusai G, et al: Outcome of R1 resection in patients undergoing pancreaticoduodenectomy for pancreatic most cancers, Eur J Surg Oncol 34: 1309�1315, 2008. Gehring S, et al: Kupffer cells abrogate cholestatic liver injury in mice, Gastroenterology 130(3):810�822, 2006. Gillen S, et al: Palliative resections versus palliative bypass procedures in pancreatic most cancers: a scientific evaluation, Am J Surg 203(4):496�502, 2012. Girelli R, et al: Feasibility and security of radiofrequency ablation for regionally advanced pancreatic most cancers, Br J Surg 97(2):220�225, 2010. Gudjonsson B: Pancreatic most cancers: survival, errors and evidence, Eur J Gastroenterol Hepatol 21:1379�1382, 2009. H�ser N: Systematic evaluation and meta-analysis of prophylactic gastroenterostomy for unresectable superior pancreatic most cancers, Br J Surg 96:711�719, 2009. Ihse I, et al: Bilateral thoracoscopic splanchnicectomy: effects on pancreatic pain and function, Ann Surg 230:785�790, 1999. Khashab M, et al: Enteral stenting versus gastrojejunostomy for palliation of malignant gastric outlet obstruction, Surg Endosc 27(6):2068� 2075, 2013. Kohan G, et al: Laparoscopic hepaticojejunostomy and gastrojejunostomy for palliative remedy of pancreatic head most cancers in forty eight sufferers, Surg Endosc 29(7):1970�1975, 2015. Kuriansky J, et al: Simultaneous laparoscopic biliary and retrocolic gastric bypass in patients with unresectable carcinoma of the pancreas, Surg Endosc 14:179�181, 2000. Lavu H, et al: Margin positive pancreaticoduodenectomy is superior to palliative bypass in regionally superior pancreatic ductal adenocarcinoma, J Gastrointest Surg 13(11):1937�1946, dialogue 1946-1947, 2009. Leksowski K: Thoracoscopic splanchnicectomy for management of intractable pain due to superior pancreatic cancer, Surg Endosc 15:129� 131, 2001. Lesurtel M, et al: Palliative surgical procedure for unresectable pancreatic and periampullary cancer: a reappraisal, J Gastrointest Surg 10:286�291, 2006. Mizuguchi K, et al: Short-term effects of exterior and internal biliary drainage on liver and mobile immunity in experimental obstructive jaundice, J Hepatobiliary Pancreat Surg 11(3):176�180, 2004. Nagaraja V, et al: Endoscopic stenting versus operative gastrojejunostomy for malignant gastric outlet obstruction: a scientific review and meta-analysis of randomized and non-randomized trials, J Gastrointest Oncol 5(2):92�98, 2014. Narayanan G, et al: Vessel patency publish irreversible electroporation, Cardiovasc Intervent Radiol 37(6):1523�1529, 2014. Navarra G, et al: Palliative antecolic isoperistaltic gastrojejunostomy: a randomized managed trial evaluating open and laparoscopic approaches, Surg Endosc 20(12):1831�1834, 2006. Rhodes M, et al: Laparoscopic biliary and gastric bypass: a useful adjunct in the therapy of carcinoma of the pancreas, Gut 36:778� 780, 1995. Roy A, et al: Stenting versus gastrojejunostomy for administration of malignant gastric outlet obstruction: comparability of medical outcomes and prices, Surg Endosc 26(11):3114�3119, 2012. Seicean A, et al: Pain palliation by endoscopic ultrasound-guided celiac plexus neurolysis in sufferers with unresectable pancreatic cancer, J Gastrointestin Liver Dis 22(1):59�64, 2013. Singh S, et al: Palliative surgical bypass for unresectable periampullary carcinoma, Hepatobiliary Pancreat Dis Int 7:308�312, 2008. Slaar A, et al: Predicting distant metastasis in sufferers with suspected pancreatic and periampullary tumors for selective use of staging laparoscopy, World J Surg 35(11):2528�2534, 2011. Suzuki O, et al: Laparoscopic modified Devine exclusion gastrojejunostomy as a palliative surgery to relieve malignant pyloroduodenal obstruction by unresectable cancer, Am J Surg 194:416�418, 2007. Tachezy M, et al: Bypass surgical procedure versus deliberately incomplete resection in palliation of pancreatic cancer: is resection the lesser evil Thomassen I, et al: Incidence, prognosis, and possible therapy strategies of peritoneal carcinomatosis of pancreatic origin: a populationbased research, Pancreas 42(1):72�75, 2013. Ueda J, et al: Hepaticocholecystojejunostomy as efficient palliative biliary bypass for unresectable pancreatic cancer, Hepatogastroenterology 61(129):197�202, 2014. Endocrine Tumors Chapter 69 Palliative treatment of pancreatic and periampullary tumors1053. Weber A, et al: Self-expanding metallic stents versus polyethylene stents for palliative treatment in sufferers with superior pancreatic cancer, Pancreas 38:e7�e12, 2009. Crippin Surgery in the affected person with continual hepatitis can create a number of dilemmas within the preoperative, perioperative, and postoperative phases. Intraoperatively, both technical and anesthesiology considerations will probably have an result on the result (see Chapters 24 and 103).
Sobota, 45 years: However, in metabolic causes or those associated with alcohol abuse, the pain could also be poorly localized and fewer acute in onset (Whitcomb, 2006).
Gunock, 53 years: Crippin Surgery within the affected person with continual hepatitis can create multiple dilemmas in the preoperative, perioperative, and postoperative phases.
Innostian, 25 years: Singhal D, et al: Palliative administration of hilar cholangiocarcinoma, Surg Oncol 14(2):59�74, 2005.
Ramon, 54 years: Failure to administer these agents incessantly leads to persistent an infection in the neonate, because of the shortcoming of an immature immune system to eradicate hepatitis B viremia (Lok, 2002).
Mitch, 34 years: Kaya M, et al: Treatment of cholangiocarcinoma complicating major sclerosing cholangitis: the Mayo Clinic experience, Am J Gastroenterol ninety six:1164�1169, 2001.
Umul, 59 years: Delhaye M, et al: Extracorporeal shock-wave lithotripsy of pancreatic calculi, Gastroenterology 102:610�620, 1992.
Nasib, 57 years: Optimal fluid steadiness also reduces cardiac, pulmonary, and renal issues, which might reduce length of stay.
Onatas, 33 years: Primary sarcomas of the gallbladder, together with embryonal rhabdomyosarcoma, leiomyosarcoma, malignant fibrous histiocytoma, angiosarcoma, and Kaposi sarcoma, have been reported and are extraordinarily rare.
References

Desarrolló: Grupo Guadalupe S.R.L.