
Mark Kozak, MD
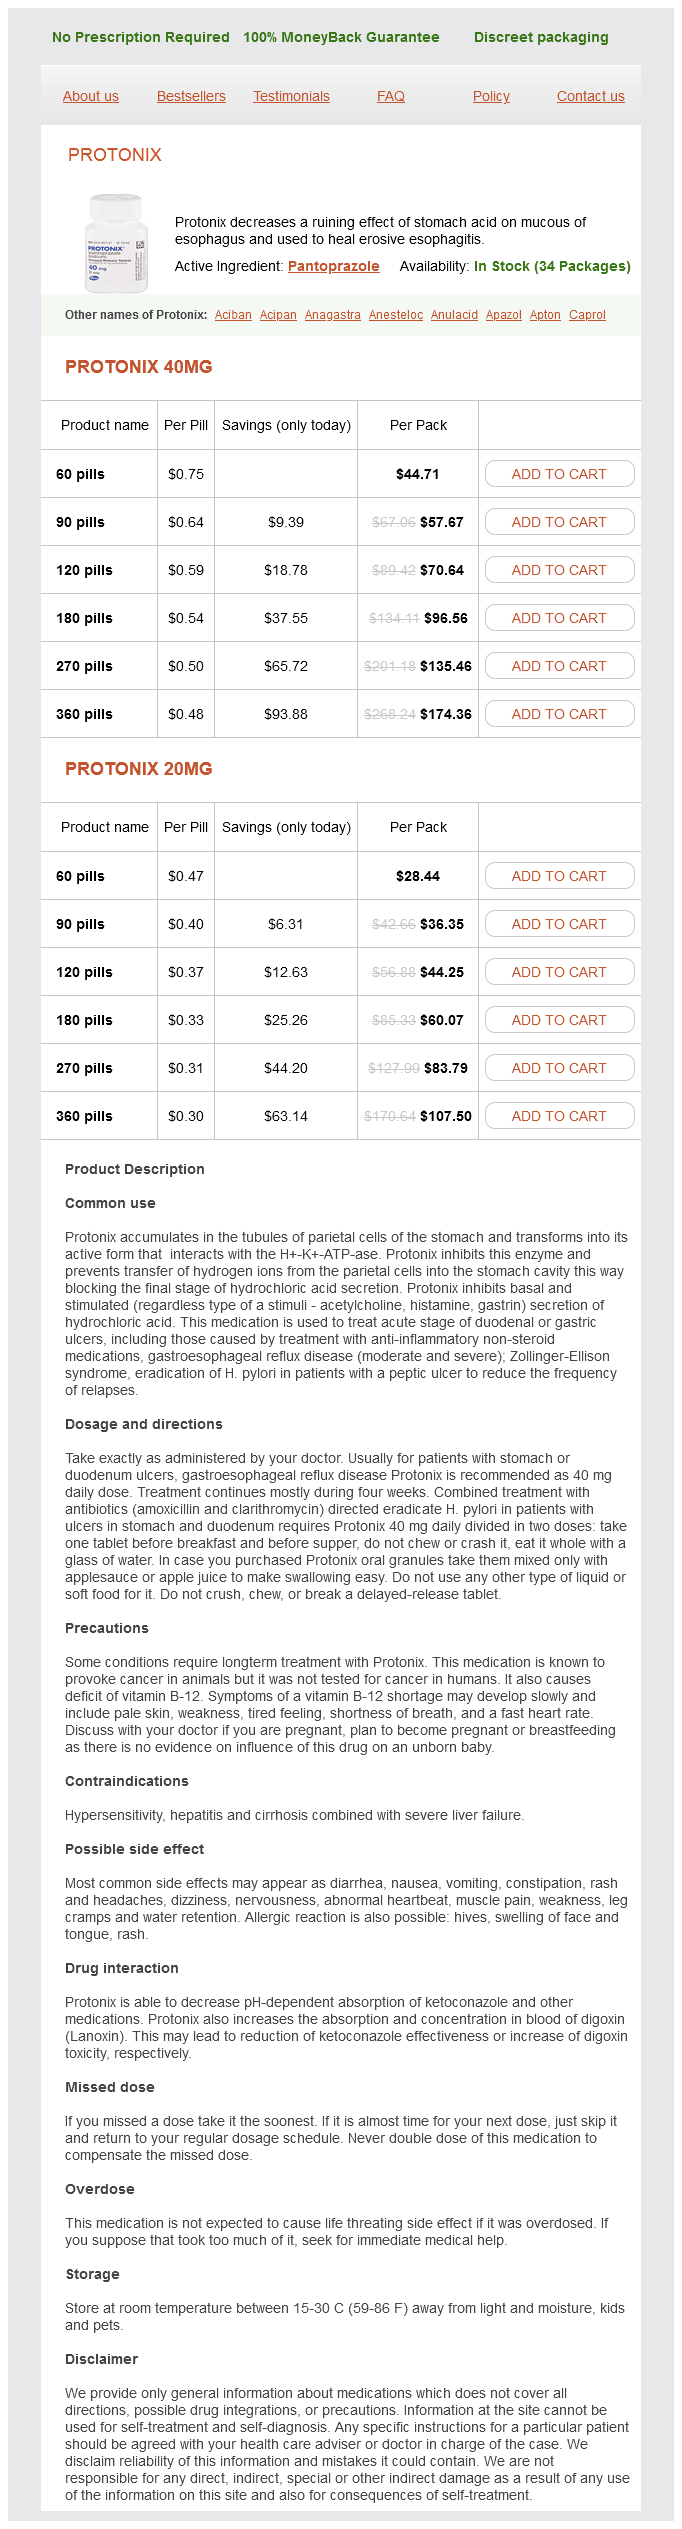
Protonix dosages: 40 mg, 20 mg
Protonix packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills

PregnancyandChildbearing After successful kidney transplantation, levels of follicle-stimulating hormone, luteinizing hormone, and testosterone often become normal and spermatogenesis improves (Akbari et al, 2003; Kheradmand and Javadneia, 2003). It is really helpful, however, that impregnation be delayed for no less than 1 year after transplantation (Armenti et al, 1998). Successful renal transplantation usually restores fertility in premenopausal girls. Guidelines for preventing transmission of human immunodeficiency virus through transplantation of human tissue and organs. Experience with 750 consecutive laparoscopic donor nephrectomies: is it time to use a standardized classification of issues The impact of accepting dwelling kidney donors with mild hypertension or proteinuria on transplantation charges. Morbidity and mortality after residing kidney donation, 1999�2001: survey of United States transplant centers. Living kidney donor evaluation: challenges, uncertainties and controversies amongst transplant nephrologists and surgeons. Analytical interferences in point-of-care testing glucometers by icodextrin and its metabolites: an overview. Survival improvement amongst patients with end-stage renal illness: tendencies over time for transplant recipients and wait-listed sufferers. Organ Procurement and Transplantation Network/Scientific Registry of Transplant Recipients. End stage polycystic kidney illness: indications and timing of native nephrectomy relative to kidney transplantation. A great tool for evaluation of perioperative cardiac morbidity in kidney transplant recipients. Cancers of the kidney and urinary tract in sufferers on dialysis for end-stage renal illness: analysis of knowledge from the United States, Europe, and Australia and New Zealand. Transurethral resection of the prostate in kidney transplant recipients: urological and renal useful outcomes at long-term follow-up. Efficacy of hemodialysis and renal transplantation on reproductive operate in men with finish stage renal illness. History of the Banff classification of allograft pathology as it approaches its 20th year. Should intravesical Bacillus Calmette-Gu�rin be employed in transplant recipients with bladder carcinoma Hematopoietic cell transplantation for tolerance induction: animal models to scientific trials. Renal autotransplantation and modified pyelovesicostomy for intractable metabolic stone disease. Complications following unstented parallel incision extravesical ureteroneocystostomy in 1,000 kidney transplants. Long-term comparative outcomes between 2 frequent ureteroneocystostomy methods for renal transplantation. Fibrin sealant sclerotherapy for treatment of lymphoceles following renal transplantation. The diploma of damage to the kidney and the impact on overall renal perform is dependent upon the severity of the obstruction (partial or complete, unilateral or bilateral), the chronicity of the obstruction (acute vs. The explanation for urinary tract obstruction could be congenital or acquired and benign or malignant, and a list of possible etiologic elements is supplied in Box 48-1. The histologic derangements associated with obstruction are localized primarily to the interstitial compartment of the kidney and include large tubular dilation, progressive interstitial fibrosis, and a loss in renal mass secondary to apoptotic cell dying (Misseri et al, 2004). These adjustments and any resulting impression on renal function are collectively referred to as obstructive nephropathy. Although urinary tract obstruction typically leads to hydronephrosis, or dilation of the renal pelvis and/or calyces, hydronephrosis can be present in the absence of obstruction. The prognosis of urinary tract obstruction due to this fact requires other scientific and radiographic findings, rather than the presence of hydronephrosis alone. Flank pain secondary to stretching of the amassing system is the most common symptom in sufferers with acute obstruction; is often an unrelenting, excruciating pain that can radiate to the lower abdomen and testicles or labia on the affected side; and is usually associated with nausea or vomiting. In distinction, persistent obstruction of the urinary tract is usually a relatively painless phenomenon and sufferers could additionally be totally asymptomatic. Obstruction of the bladder outlet is most frequently related to voiding signs of frequency, urgency, hesitancy, nocturia, poor urinary stream, and the feeling of incomplete emptying. Anuria is a rare but dramatic and pretty particular presenting signal of urinary tract obstruction.

Effect of parenchymal quantity preservation on kidney perform after partial nephrectomy. Nephrectomy and vena caval thrombectomy in patients with metastatic renal cell carcinoma. Preoperative embolization of retroperitoneal hemangiopericytomas as an aid in their removal. Clinical outcome of surgical management for sufferers with renal cell carcinoma involving the inferior vena cava. Response of the first tumor to neoadjuvant sunitinib in patients with advanced renal cell carcinoma. Patients with pT1 renal cell carcinoma who die from disease after nephrectomy could have unrecognized renal sinus fats invasion. Reclassification of sufferers with pT3 and pT4 renal cell carcinoma improves prognostic accuracy. Implications of B7-H1 expression in clear cell carcinoma of the kidney for prognostication and therapy. Costimulatory B7-H1 in renal cell carcinoma sufferers: indicator of tumor aggressiveness and potential therapeutic goal. Tumor B7-H1 is associated with poor prognosis in renal cell carcinoma sufferers with long-term follow-up. Renal function after partial nephrectomy: impact of heat ischemia relative to quantity and high quality of preserved kidney. Is renal sinus fats invasion the identical as perinephric fat invasion for pT3a renal cell carcinoma Complications of contemporary open nephron sparing surgery: a single institution expertise. Primitive neuroectodermal tumor of the kidney: a single institute series of sixteen patients. Collecting duct (Bellini duct) renal cell carcinoma: a nationwide survey in Japan. Ki-67 and coagulative tumor necrosis are impartial predictors of poor end result for sufferers with clear cell renal cell carcinoma and not surrogates for one another. Image-guided biopsy-diagnosed renal cell carcinoma: crucial appraisal of technique and long-term follow-up. A postoperative prognostic nomogram predicting recurrence for patients with typical clear cell renal cell carcinoma. Renal cell carcinoma extending into the inferior vena cava: the prognostic significance of the level of vena caval involvement. Growth characteristics of renal cortical tumors in patients managed by watchful waiting. Racial/ethnic and gender disparities in renal cell carcinoma incidence and survival. High-density mapping of chromosomal arm 1q in renal amassing duct carcinoma: region of minimal deletion at 1q32. Guidelines for the surveillance of localized renal cell carcinoma based mostly on the patterns of relapse after nephrectomy. Clinical and pathological features related to prognosis in sufferers with papillary renal cell carcinoma. Positive margin throughout partial nephrectomy: does cancer remain in the renal remnant Renal medullary carcinoma: medical, pathologic, immunohistochemical, and genetic evaluation with pathogenetic implications. Elucidation of the molecular signatures of renal cell carcinoma by gene expression profiling. Population-level comparative effectiveness of laparoscopic versus open radical nephrectomy for patients with kidney cancer. A section 2 trial of sunitinib in patients with advanced non�clear cell renal cell carcinoma. Prognostic impact of histological subtype on surgically treated localized renal cell carcinoma. Renal cell carcinoma invading the urinary amassing system: implications for staging.

Conservative therapy should be the first-line remedy and contains scrotal elevation and assist, warmth or ice (as wanted for comfort), and nonsteroidal anti-inflammatory medication. Conservative remedy ought to be employed for a minimal of 3 months for postvasectomy pain. Spermatic wire blocks and pain administration techniques should be thought-about after failure of conservative therapy. Surgical remedy could be thought-about on an individualized basis if the aforementioned strategies fail. When pain is clearly localized to a sperm granuloma, excision of the granuloma and intraluminal cautery occlusion of the vas deferens may relieve the pain and stop recurrence (Schmidt, 1979). Epididymectomy has been performed in sufferers who had point tenderness to the epididymis and epididymal dilation after vasectomy and failed conservative therapy. Predictors of poor outcomes with epididymectomy are atypical symptoms, concomitant erectile dysfunction, and a normal-appearing epididymis on scrotal ultrasonography (West et al, 2000). Of patients who were correctly chosen for epididymectomy, 50% have been cured of postvasectomy pain syndrome (Chen and Ball, 1991). The affected person must contemplate that vasectomy reversal will not be possible after epididymectomy. Vasectomy reversal rendered 69% of sufferers with postvasectomy ache syndrome pain-free (Nangia et al, 2000). Although it has been evaluated in solely a small variety of patients, microscopic denervation of the spermatic twine in patients who failed conservative treatment resulted in full pain relief in 76% of these men (Ahmed et al, 1997). The final resort consideration after failure of conservative and extra invasive interventions have failed is orchiectomy for severe intractable ache after vasectomy. Pain aid was reported in 73% of males who underwent inguinal orchiectomy versus 55% of men who underwent scrotal orchiectomy for postvasectomy ache syndrome (Davis et al, 1990). Minimizing inflammation near the vas deferens would offer the optimum condition for microscopic vasectomy reversal in the future (Mammen et al, 2008). Time to attain azoospermia is variable, although greater than 80% of patients obtain azoospermia by 3 months and after 20 ejaculations. These information level to obtaining a semen analysis at three months and 20 ejaculations after vasectomy to reveal azoospermia. Additional samples must be submitted if the initial semen analysis has motile sperm or greater than a hundred,000 nonmotile sperm/mL. Vasectomy must be repeated if any motile sperm are seen within the ejaculate 6 months after the initial vasectomy (American Urological Association, 2012). This take a look at was developed to improve compliance with postvasectomy evaluation of semen parameters. The SpermCheck Vasectomy check was 96% correct at predicting whether sperm counts have been larger or less than a threshold of 250,000 sperm/ mL (Klotz et al, 2008). Local problems of vasectomy include hematoma, infection, Fournier gangrene, chronic scrotal pain, and traumatic fistula/scrotal sinus (Awsare et al, 2005). The most necessary predictor of postoperative issues is surgeon quantity and experience (Kendrick et al, 1987). The rate of infection from vasectomy with the standard approach was reported to be between 12% and 38% however decreased to 0. Although exceedingly rare, Fournier gangrene has been reported as a complication in males undergoing vasectomy (de Diego Rodr�guez et al, 2000; Romero P�rez et al, 2004). The medical literature on postvasectomy ache syndrome, or long-term scrotal ache after surgical procedure, consists of research with small pattern sizes, nonvalidated ache measures, high nonresponse charges, and variable end result measures. The most robust research identified the incidence of chronic scrotal ache severe sufficient to seek medical attention to be 0. Detection bias is believed to be the source of this association of prostate most cancers with vasectomy (Millard, 1999). Previous studies advised that vasectomy may be a risk factor for patients with major progressive aphasia, a dementia syndrome with aphasia as the presenting symptom (Weintraub et al, 2006).

Endoureteropyelotomy: percutaneous therapy of ureteropelvic junction obstruction. Management of secondary ureteropelvic junction obstruction after failed major laparoscopic pyeloplasty. Treatment of idiopathic retroperitoneal fibrosis with colchicine and steroids: a case series. Advances in radiographic staging, improvements in hemodynamic monitoring, and wider use of angioembolization have improved the charges of renal preservation and decreased pointless surgery. The majority of blunt and lots of penetrating accidents to the kidneys not require open surgical intervention. Close follow-up of these patients and timely therapy of nonoperative failures or issues are still necessary. PresentationandHistory Motor automobile accidents, falls from heights, and assaults contribute to the vast majority of blunt renal trauma. Direct transmission of kinetic vitality and fast deceleration forces place the kidneys at risk. Perhaps the most important data to get hold of within the historical past of blunt renal damage is the extent of deceleration involved in high-velocity impression trauma. Significant acceleration/deceleration could cause uncommon but lethal renovascular injuries. These occur when the kidney tears at retroperitoneal factors of fixation such because the renal hilum or ureteropelvic junction, leading to renal artery thrombosis, renal vein disruption, and renal pedicle avulsion. For instance, nearly all of the renal accidents after automobile accidents had been caused by unrestrained drivers with direct influence on the steering wheel or side influence with the lateral door, often with 30 cm or more of door incursion (Kuan et al, 2007). Understanding details of the accident from first responders on the scene can improve the extent of suspicion for renal harm. Gunshot wounds comprise the great majority of the penetrating trauma, with stab wounds a distant second (86% vs. Penetrating mechanisms result in higher rates of significant and protracted renal bleeding, want for renorrhaphy/nephrectomy, and issues when managed nonoperatively. Of all sufferers sustaining renal trauma in a large urban sequence, renal gunshot wounds occurred in roughly 4% (McAninch et al, 1993). Stab wounds from assault or self-inflicted injuries could cause each renovascular and parenchymal injuries. Common entry sites including the higher abdomen, flank, and decrease chest ought to alert the clinician to potential renal involvement. Trauma to the anterior axillary line is extra vulnerable to damage necessary renal constructions such because the renal hilum and pedicle in comparison with the posterior axillary line, which more generally ends in parenchymal injury. Should the weapon be recovered, its dimensions should be noted as a result of the length and width give priceless data on its penetrating and harmful traits. With a blunt mechanism, cervical backbone immobilization is remitted until confirmed intact by radiography. The presence of a flank hematoma, stomach or flank tenderness, rib fractures, and penetrating injuries to the low thorax or flank point out potential renal harm. Ipsilateral rib fracture can increase the incidence of significant renal trauma threefold. Gunshot accidents could be deceptive in that small entrance wounds may underestimate bigger tissue destruction throughout the physique. Bullet fragments can create secondary missiles, leading to multiple harm tracts. Gross hematuria has been observed in minor renal contusions, and microscopic hematuria has been seen in some with extreme renal accidents. In patients with blunt trauma, microscopic hematuria related to shock considerably will increase the incidence of extreme renal accidents (Nicolaisen et al, 1985; Mee and McAninch, 1989; Mee et al, 1989; Miller and McAninch, 1995). The first aliquot of urine obtained by catheterization or voiding is used to determine the presence of hematuria. Later urine samples could also be diluted by diuresis from resuscitation fluids, leading to an underestimation or absence of hematuria. The dipstick technique is rapid and has a sensitivity and specificity for detection of microhematuria of more than 97%, despite the precise fact that a poor correlation with actual urinalysis was noted in a single research (Chandhoke and McAninch, 1988). Indications for Renal Imaging the factors for radiographic imaging include the following: 1.

The syndrome of distal (type 1) renal tubular acidosis: medical and laboratory findings in fifty eight circumstances. Comparative research of the influence of three kinds of mineral water in patients with idiopathic calcium lithiasis. Solid part assay of urine cystine supersaturation within the presence of cystine binding medication. Is estrogen preferable to surgical procedure for postmenopausal girls with primary hyperparathyroidism Chlorthalidone promotes mineral retention in patients with idiopathic hypercalciuria. Urinary composition and lithogenic danger in regular topics following oligomineral versus bicarbonatealkaline excessive calcium mineral water intake. Effects of aminobisphosphonates and thiazides in patients with osteopenia/ osteoporosis, hypercalciuria, and recurring renal calcium lithiasis. Renal oxalate excretion following oral oxalate hundreds in sufferers with ileal illness and with renal and absorptive hypercalciurias: effect of calcium and magnesium. Metabolic evaluation of youngsters with urolithiasis: are grownup references for supersaturation appropriate Effect of vitamin C supplements on urinary oxalate and pH in calcium stone-forming patients. Effects of water hardness on urinary danger factors for kidney stones in patients with idiopathic nephrolithiasis. The effects of a single night dose of alkaline citrate on urine composition and calcium stone formation. Effect of modifications in epidemiological components on the composition and racial distribution of renal calculi. Potassium-magnesium citrate is an effective prophylaxis against recurrent calcium oxalate nephrolithiasis. The explanation for maintained hypercalciuria after the surgical cure of main hyperparathyroidism is a defect in renal calcium reabsorption. Failure of thiazide diuretics to enhance plasma calcium in mild primary hyperparathyroidism. The influence of a excessive dietary consumption of purine-rich animal protein on urinary urate excretion and supersaturation in renal stone illness. Effects of magnesium oxide on the crystallization of calcium salts in urine in sufferers with recurrent nephrolithiasis. A comparability of the consequences of potassium citrate and sodium bicarbonate within the alkalinization of urine in homozygous cystinuria. Acetohydroxamic acid: medical research of a urease inhibitor in patients with staghorn renal calculi. Randomized, double-blind trial of Lithostat (acetohydroxamic acid) in the palliative remedy of infectioninduced urinary calculi. Assessment of citrate concentrations in citrus fruit-based juices and beverages: implications for administration of hypocitraturic nephrolithiasis. Comparison of 2mercaptopropionylglycine and d-penicillamine within the treatment of cystinuria. Similarity of urinary threat elements among stoneforming patients in five regions of the United States. Cystinuria: impact of d-penicillamine on plasma and urinary cystine concentrations. A potential study of the consumption of nutritional vitamins C and B6, and the chance of kidney stones in males. Penicillamine remedy for pediatric cystinuria: experience from a cohort of American children. Spiral computed tomography: position in determination of chemical compositions of pure and blended urinary stones-an in vitro examine. Modified technique of percutaneous cystolithotripsy using a brand new instrument: combined single-step trocardilator with self-retaining adjustable access sheath. Estrogen replacement may be an alternative alternative to parathyroid surgical procedure for the remedy of osteoporosis in aged postmenopausal girls presenting with major hyperparathyroidism: a preliminary report. Risk of calcium oxalate nephrolithiasis in postmenopausal girls supplemented with calcium or combined calcium and estrogen. Differentiating primary from secondary hyperparathyroidism in stone patients: the "thiazide challenge". Diabetic kidney stone formers excrete extra oxalate and have decrease urine pH than nondiabetic stone formers. Abnormalities of 24-hour urine composition in first-time and recurrent stone-formers.

Since the mid-1970s, the overall incidence of bladder calculi appears to have stabilized or decreased among males and increased slightly for females; these developments are doubtless caused by the increase within the dimension of the aged inhabitants as life expectancies lengthen, in addition to by an general improve within the variety of female genitourinary procedures carried out annually (Schwartz and Stoller, 2000; Terai et al, 2008; Yasui et al, 2008). Bladder calculi may come up de novo within the bladder or may result from the maturation of stone nidi that migrate from the higher tracts and subsequently fail to be voided spontaneously. The frequent absence of calcium oxalate within the nucleus of most bladder stones additional suggests in opposition to an upper tract origin (Douenias et al, 1991; Vanwaeyenbergh et al, 1995). The pathogenesis and composition of bladder calculi depend largely on the inciting pathologic course of and the presence or absence of an infection. The composition of stones ensuing from anatomic obstruction varies with geography and ethnicity. In Europe, struvite, calcium phosphate, and uric acid predominate, whereas in Japan uric acid calculi are uncommon and calcium stones are increasing in incidence, now representing 72% of all stones present in a recent sequence. Stones are normally solitary, although a quantity of stones could exist in 25% to 30% of patients (Sarica et al, 1994). Often a international physique within the bladder will encrust initially with calcium oxalate as a result of the conventional stasis that happens with the storage of urine. Should infection supersede, speedy coalescence of the stone might occur as struvite is deposited on the nascent stone (Dalton et al, 1975; Khan and Wilkinson, 1990; Vanwaeyenbergh et al, 1995; Schwartz and Stoller, 2000). The vast majority of intravesical foreign bodies result from iatrogenic interventions, though self-mutilation performs a task in a minority of patients (Dalton et al, 1975; Douenias et al, 1991; Schwartz and Stoller, 2000); complications ensuing from urogynecologic interventions predominate. Inadvertent violation of the bladder with suture materials during suspension or sling procedures is a common supply of an intravesical overseas physique. This error is commonly not detected intraoperatively, underscoring the importance of thorough cystoscopic inspection earlier than the conclusion of the procedure (Zderic et al, 1988). Along with the rise in recognition of incontinence surgical procedure involving artificial mesh, similar to tension-free vaginal tape procedures, a rise has been noted in calculi forming on parts of the mesh which have eroded into the bladder (Chamary, 1995; Koelbl et al, 2001; Irer et al, 2005; Mustafa and Wadie, 2007). In addition, erosion of wire suture used for cerclage has been reported (Ehrenpreis et al, 1986). Stone encrustation of migrated intrauterine gadgets, pessaries, and contraceptive diaphragms has also been reported (Staskin et al, 1985; Khan and Wilkinson, 1990; Mahazan, 1995; Chow et al, 1997; Maskey et al, 1997; Schwartz and Stoller, 2000; Demirci et al, 2003; Chae et al, 2012). In addition, unrecognized anorectal impalement, although an unusual incidence, has been reported to provide a international physique nidus for bladder stone formation (Guha et al, 2012). Stones may also kind on nondegradable surgical clips placed close to the vesicourethral anastomosis which have migrated into the bladder; such stones have been reported with both metal and plastic clips, though the true incidence of this complication remains unclear (Banks et al, 2008; Kadekawa et al, 2009; Mora et al, 2010; Yi et al, 2010). In addition, necrotic tissue resulting from chemical ablation of the prostate for benign prostatic hyperplasia has been cited as a nidus for stone formation (Ikari et al, 2005), as has the presence of intraprostatic stents (Chiu et al, 1991; Squires and Gillatt, 1995). Migration of seeds following prostate brachytherapy is frequent and may be associated with bladder stone formation (Sugawara et al, 2009; Miyazawa et al, 2012; Leapman et al, 2014). Erosion of an inflatable penile prosthesis and synthetic urinary sphincters leading to stone encrustation has also been reported (Dupont and Hochman, 1988; Barroso et al, 2000; Bartoletti et al, 2000). The growth of bladder calculi is an rare complication of long-term urinary tract drainage. Encrustation of short-term ureteral stents is a typical discovering, although vital intravesical stone formation might happen in cases where the stent is left resident for an prolonged period (Giannakopoulos et al, 2001; Damiano et al, 2002; Hao et al, 2008; Vanderbrink et al, 2008; Waters et al, 2008). Long-term bladder drainage can also result in bladder lithiasis, with a reported incidence of 0. Even sufferers who carry out clean intermittent catheterization is probably not immune, as a outcome of inadvertent introduction of hair into the bladder with the passage of the catheter might present a nidus for stone formation (Derry and Nuseibeh, 1997). On uncommon events, intravesical calculi may also come up because of the migration and erosion of overseas bodies unrelated to genitourinary manipulation. These embody orthopedic cement, surgical clips, ventriculoperitoneal shunts, and abandoned gallbladder stones ensuing from spillage throughout cholecystectomy (Radford and Thomson, 1989; Chia and Ross, 1995; Maier and Treu, 1996; Eichel et al, 2002). Neurogenic Bladder and Spinal Cord Injury Neurogenic bladder resulting from spinal wire harm or myelomeningocele locations patients at elevated risk of bladder stone formation. For adults with spinal twine harm, the danger for bladder stone formation peaks at three months after the initial injury, and inside 10 years 15% to 30% of patients may have fashioned at least one stone (Chen et al, 2001). Unfortunately, after a affected person has fashioned one stone, the danger for subsequent stone formation quadruples (Ord et al, 2003). The degree and severity of the spinal wire damage appears to be carefully correlated with the chance of bladder stone formation, particularly after the first 12 months (Chen et al, 2001; Sugimura et al, 2008).

Boyce and colleagues (1962) found that substance A is immunologically unique and present within the matrix part of all stone formers. Moore and Gowland (1975) determined that substance A is composed of three or four distinct antigens distinctive to stones that had been detected within the urine of 85% of stone formers but in no regular individuals. A study utilizing reverse-phase, high-performance liquid chromatography and tandem mass spectrometry to evaluate calcium oxalate stones identified 68 distinct proteins with 95% confidence, including a big variety of inflammatory proteins (immunoglobulins, defensin-3, clusterin, complement C3a, kininogen, and fibrinogen) (Canales et al, 2008). Comparing the matrix part of thirteen calcium oxalate and 12 calcium phosphate stones, these investigators found that inflammatory proteins comprised the predominant proteins in both stone types, with many proteins in widespread, suggesting a shared pathogenesis for the two stone sorts that involves inflammation (Canales et al, 2010). The actual position of matrix in stone formation, whether or not as promoter, inhibitor, or passive bystander, has but to be elucidated. Calcium absorption in the kidney is complex, however current work has begun to elucidate the proteins and mechanisms concerned. On common, solely 1% to 3% of filtered calcium is excreted in the urine, with most being reabsorbed paracellularly within the renal proximal tubule (60% to 65%) and thick ascending limb of the loop of Henle (25% to 30%). The remaining 8% to 10% of filtered calcium is reabsorbed transcellularly within the distal convoluted tubule (Friedman, 2007). The paracellular absorption of calcium in the proximal tubule and thick ascending limb of the loop of Henle occurs by a number of mechanisms. First, calcium travels by way of paracellular channels discovered at the tight junctions of epithelial cells within the proximal tubule. The integral membrane proteins of the tight junction embrace occludin, junctional adhesion molecules, and claudins (Furuse et al, 1993; Ebnet et al, 2004; Hou, 2013). Claudins are a family of proteins with 4 transmembrane domains (Lal-Nag and Morin, 2009; Hou, 2013), including claudin-2, which has been implicated in paracellular reabsorption of calcium and different cations in the proximal tubule (Muto et al, 2010), and claudin-16 and claudin-19, which kind a paracellular channel advanced that permits selective cation permeation within the thick ascending limb (Hou et al, 2008, 2009). Calcium is passively reabsorbed from the lumen of the thick ascending limb of the loop of Henle into the interstitial space through a paracellular pathway pushed by a lumen-positive transepithelial voltage gradient (Hou, 2013). The positive luminal voltage happens because of apical potassium secretion and basolateral chloride secretion, as well as by the use of a transepithelial NaCl concentration gradient over the cation-selective paracellular channel within the thick ascending limb. Transcellular calcium absorption in the distal convoluted tubule happens by way of a quantity of mechanisms (Mensenkamp et al, 2006, 2007). Calcium is sure within the cell to a chaperone protein (calbindin-D28k), which facilitates diffusion throughout the cell from the apical to the basolateral house where calcium can then exit. By a means of intestinal adaptation, absorption of calcium varies with calcium intake. At times of low calcium intake, fractional calcium absorption is enhanced; during excessive calcium consumption, fractional calcium absorption is lowered. With a calcium-rich diet, a nonsaturable, paracellular pathway for calcium absorption predominates. A saturable, vitamin D�dependent transcellular pathway constitutes the main pathway for intestinal calcium absorption when calcium intake is restricted; this pathway is downregulated by a food regimen replete in calcium (Buckley and Bronner, 1980; Bronner et al, 1986). A small quantity of calcium is secreted into the lumen of the gut, thereby reducing internet calcium absorption such that, overall, 100 to 300 mg of a complete average calcium intake of 600 to 1200 mg day by day will be absorbed. Calcium is absorbed within the ionic state, and incomplete calcium absorption is due in part to formation of soluble calcium complexes in the intestinal lumen. Therefore substances that complicated with calcium, such as phosphate, citrate, oxalate, sulfate, and fatty acids, scale back the supply of ionic calcium for absorption (Allen, 1982). Calcium readily complexes with phosphate in the intestinal lumen, but as a end result of calcium phosphate formation is dependent on pH (pK = 6. On the opposite hand, calcium oxalate complicated formation shows less pH dependence and complex formation is much less reversible. Calcitriol acts on the bone and kidney in addition to its action in rising intestinal calcium absorption. At low phosphorus concentrations (1 to three mmol/L), saturable absorptive transport occurs. At greater phosphorus levels, absorption will increase without saturation (Walton and Gray, 1979). Phosphate absorption is extremely pH dependent; low luminal pH reduces whereas excessive pH enhances phosphate transport. Approximately 65% of absorbed phosphate is excreted by the kidney and the remainder by the gut.
Surus, 45 years: This discovering is supported by an extra examine demonstrating the efficacy of medical prophylaxis when administered in a personal follow setting (Mardis et al, 2004). Effect of initial shock wave voltage on shock wave lithotripsy�induced lesion size throughout step-wise voltage ramping. Saturation-inhibition index as a measure of the chance of calcium oxalate stone formation within the urinary tract. Impact of stone location on success rates of endoscopic lithotripsy for nephrolithiasis.
Brenton, 46 years: Stab wounds from assault or self-inflicted injuries may cause both renovascular and parenchymal accidents. The behavior of the isolated rabbit renal calix and pelvis compared with that of the ureter. Acute rejection classically occurs roughly 5 days after an allogeneic organ transplant without immunosuppression. The retrospective nature of these research naturally raises concern about choice bias, and the third result listed above substantiates this concern.
Kerth, 29 years: For circumstances by which operate of the concerned kidney is already significantly compromised and the contralateral kidney is normal, nephrectomy could be thought of. This is in accord with the discovering that phenylephrine, an -adrenergic agonist, induces a larger contractile drive in isolated human ureteral segments obtained from the distal than the proximal ureter (Sasaki et al, 2011). When Nash and colleagues (1995) examined the explanations for nephrectomy in sufferers with renal injuries, 77% required removal because of the extent of parenchymal, vascular, or combined injury. Surgical therapy of ureteric obstruction in idiopathic retroperitoneal fibrosis.
Sven, 62 years: Racial disparity in renal cell carcinoma affected person survival based on demographic and clinical traits. Patients could report downside low back pain for nephrectomy and buttock ache for lithotomy circumstances. These two models have clarified the vasoconstriction-volume interactions that regulate renal hypertension. Even if a voided cytology specimen is abnormal in a patient with an upper tract filling defect, one should be cautious in figuring out the site of origin of the malignant cells.
Sebastian, 30 years: This helps to bridge the world of stenosis and allows a tension-free secondary pyeloplasty. In 1913, Primbs confirmed that Escherichia coli and staphylococcal toxins inhibited contractions of in vitro guinea pig ureteral segments (Primbs, 1913). This lesion has the characteristic "string of beads" look on angiography and normally will involve both renal arteries. This classification system was approved by an international consensus workshop of clinicians and researchers in the subject (Weiss et al, 1995; St�rkel et al, 1997; Zambrano et al, 1999).
References

Desarrolló: Grupo Guadalupe S.R.L.