
Christopher V. Chien, MD
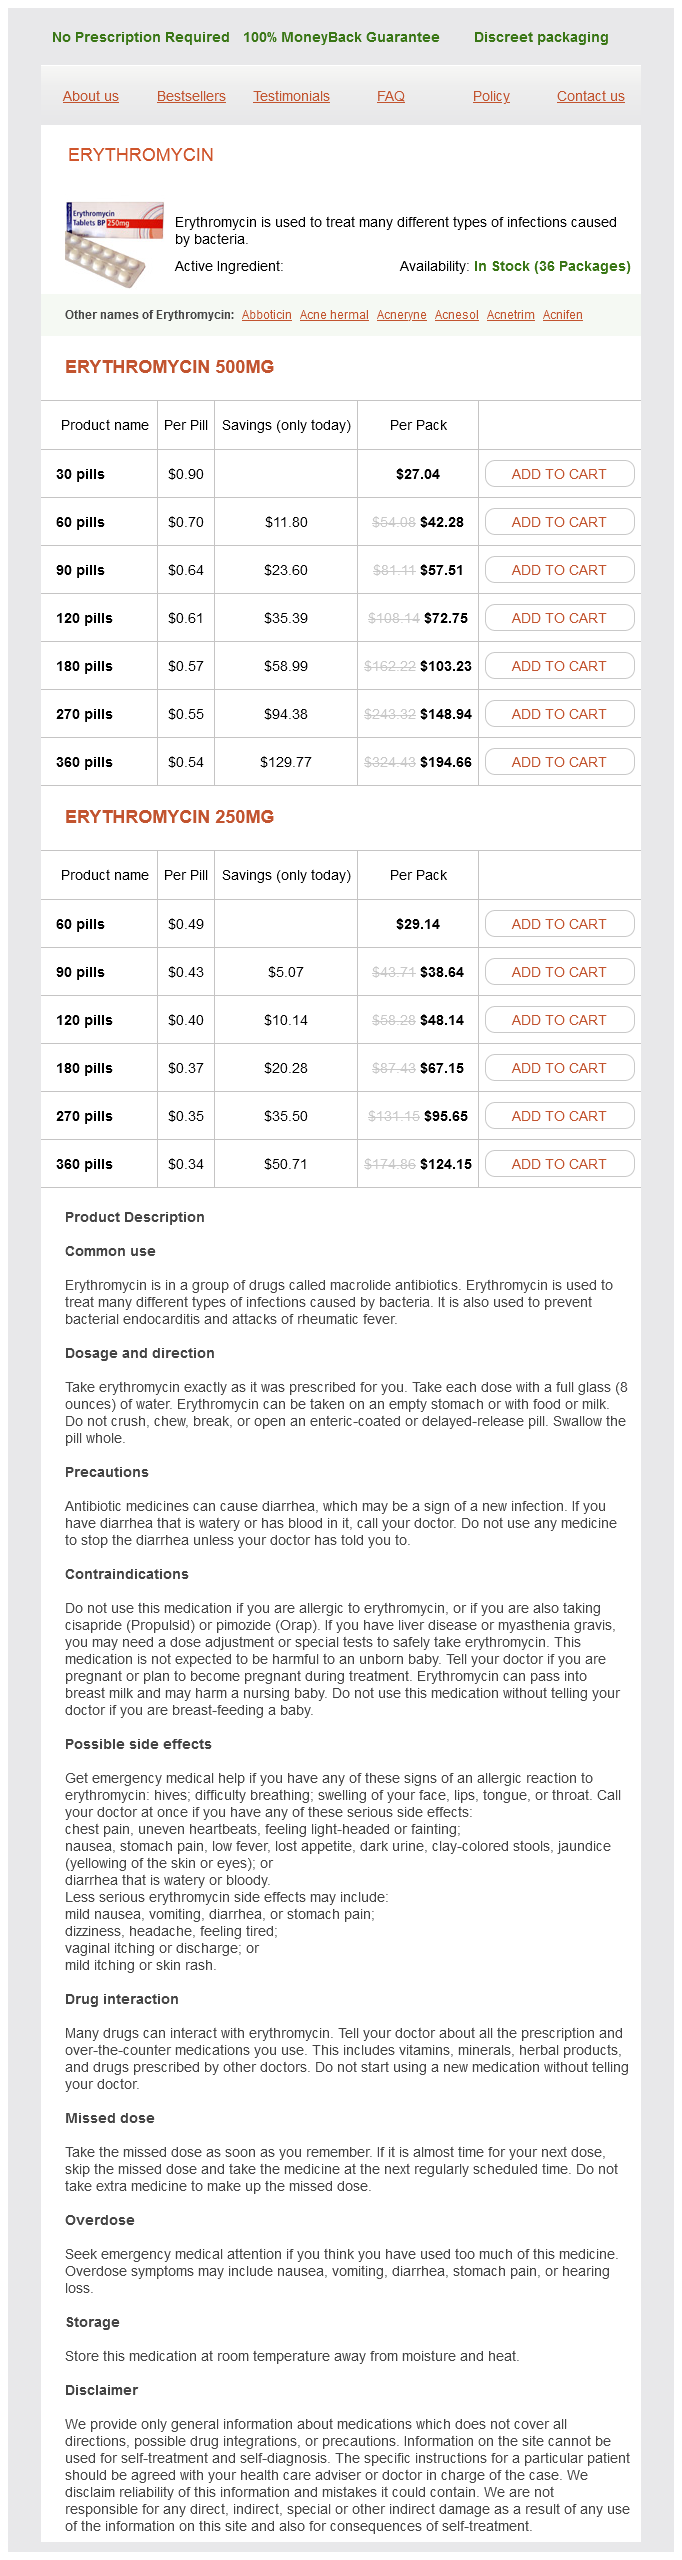
Erythromycin dosages: 500 mg, 250 mg
Erythromycin packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills

Illustration exhibiting insertion of a second triple-loaded suture anchor more superiorly, once more simply off of the articular surface. The sutures from the more inferior anchor have all been handed and are stored in suture savers outdoors of the cannula. The process is repeated, shifting extra cephalad for every set of sutures till all suture pairs have been passed in an analogous mattress fashion. Once all the sutures are handed, attention is turned to finishing the Bankart reconstruction. Tying the remplissage sutures earlier than finishing the anterior reconstruction can limit entry inferiorly and compromise the repair. Once the Bankart reconstruction is complete, the remplissage sutures may be tied from inferior to superior. The posterior cannula is removed and a looped grasper is used to convey the suture saver into the cannula outdoors of the shoulder. The cannula is superior over the suture saver via the deltoid however not via the infraspinatus or capsule. Finally, the location and place of the humeral head relative to the center of the glenoid should be evaluated. They start instant elbow, wrist, and hand exercises and are allowed to add light pendulums after the preliminary postoperative go to 1 week after surgical procedure. Supervised physical therapy begins at four weeks when sufferers discontinue the sling. Other potential problems following remplissage are recurrent instability and degeneration of the infraspinatus tendon and muscle. On the pathological adjustments produced in the shoulder joint by traumatic dislocations, as derived from an examination of all specimens illustrating this harm in the museums of London. Posttraumatic anterior-inferior instability of the shoulder: Arthroscopic findings and medical correlations. Hill-Sachs "remplissage:" an arthroscopic answer for the partaking Hill-Sachs lesion. Risk factors for recurrence of shoulder instability after arthroscopic Bankart repair. Arthroscopic Bankart repair and capsular shift for recurrent anterior shoulder instability: practical outcomes and identification of danger components for recurrence. Reliability and validity evaluation of a glenoid bone loss measurement utilizing the Bernageau profile view in continual anterior shoulder instability. Part I: related biomechanics, multidirectional instability, and extreme glenoid loss. Contact between the glenoid and the humeral head in abduction, external rotation, and horizontal extension: a brand new idea of glenoid track. Arthroscopic remplissage for humeral defect in anterior shoulder instability: is it wanted Paper offered at: thirty ninth Annual Meeting of Japan Shoulder Society; October 5-6, 2012; Tokyo, Japan. Preoperative analysis of the Hill-Sachs lesion in anterior shoulder instability: how to predict engagement of the lesion. Arthroscopic Bankart repair combined with remplissage technique for the treatment of anterior shoulder instability with engaging Hill-Sachs lesion: a report of forty nine circumstances with a minimum 2-year follow-up. Management of anterior glenohumeral instability associated with large Hill-Sachs defects. Resurfacing arthroplasty of the humerus: indications, surgical approach, and clinical outcomes. Combined arthroscopic Bankart restore and remplissage for recurrent shoulder instability. Remplissage repair � new frontiers in the prevention of recurrent shoulder instability: a 2-year follow-up comparative research. The analysis of arthroscopic remplissage by high-resolution magnetic resonance imaging.

Intermediate filaments are composed of twisted strands of a quantity of totally different proteins, including keratin, desmin, and lamin. They present considerable strength to cells and consequently are most extensively developed within the areas of cells topic to mechanical stress (for example, in association with desmosomes). Microtubules are hole tubes about 25 nm in diameter, whose subunits are composed of the protein tubulin. Microtubules additionally radiate from a region of the cell generally known as the centrosome, which surrounds two small, cylindrical bodies called centrioles, composed of nine units of fused microtubules. The centrosome is a cloud of amorphous material that regulates the formation and elongation of microtubules. During cell division, the centrosome generates the microtubular spindle fibers used in chromosome separation. Microtubules and actin filaments have additionally been implicated within the actions of organelles within the cytoplasm. These fibrous components type tracks, and organelles are propelled along these tracks by contractile proteins connected to the surface of the organelles. Cellular Structure, Proteins, and Metabolic Pathways fifty five Cilia, the hairlike extensions on the surfaces of most cells, have a central core of microtubules organized in a sample similar to that discovered in the centrioles. In motile cilia, sometimes located on sure epithelial cells, the microtubules, in combination with a contractile protein, produce actions of the cilia. In hole organs lined with ciliated epithelium, the actions of the cilia help propel the contents of the organ along the floor of the epithelium. An example of that is the cilia-mediated motion of mucus towards gravity up the trachea, which helps take away inhaled particles that might damage the lungs. The different sort of cilium is called a nonmotile, or major, cilium; most eukaryotic cells have one or a small number of nonmotile cilia. Physiologists have identified a giant number of illnesses associated with mutated genes expressed in cilia in several tissues; collectively, these ailments are known as ciliopathies and occur most regularly within the retina, liver, kidneys, and mind. The endoplasmic reticulum is a network of flattened sacs and tubules in the cytoplasm. Rough endoplasmic reticulum has hooked up ribosomes and is primarily concerned within the packaging of proteins to be secreted by the cell or distributed to different organelles. Smooth endoplasmic reticulum is tubular, lacks ribosomes, and is the location of lipid synthesis and calcium accumulation and release. The Golgi equipment modifies and sorts the proteins which would possibly be synthesized on the rough or granular endoplasmic reticulum and packages them into secretory vesicles. Endosomes are membrane-bound vesicles that fuse with vesicles derived from the plasma membrane and bud off vesicles that travel to other cell organelles. Peroxisomes use oxygen to take away hydrogen from natural molecules and in the course of kind hydrogen peroxide. The cytoplasm incorporates a community of three forms of filaments that kind the cytoskeleton: (a) actin filaments, (b) intermediate filaments, and (c) microtubules. These filaments are involved in figuring out cell form, regulating cell motility and division, and regulating cell contractility, amongst different functions. There are two types of cells: prokaryotic cells (bacteria) and eukaryotic cells (plant and animal cells). Within each eukaryotic cell are quite a few membrane-bound compartments, nonmembranous particles, and filaments, known collectively as cell organelles. The membranes that surround the cell and cell organelles regulate the movements of molecules and ions into and out of the cell and its compartments. Membranes encompass a bimolecular lipid layer, composed of phospholipids with embedded proteins. Integral membrane proteins are amphipathic proteins that often span the membrane, whereas peripheral membrane proteins are confined to the surfaces of the membrane. Tight junctions, found primarily in epithelial cells, limit the passage of molecules via the extracellular house between the cells. Identify the placement of cytoplasm, cytosol, and intracellular fluid within a cell. Describe the placement and characteristics of integral and peripheral membrane proteins. Describe the construction and performance of the three types of junctions found between cells.
Diseases
The internal capsule, a boom erang-shaped space of white m at ter, which accommodates ascending and descending projection tracts, is surrounded by basal nuclei and the thalam us (see A, p. The anterior lim b of the interior capsule, runs bet ween the pinnacle of the caudate nucleus and lentiform nucleus; the genu, and the posterior lim b are positioned between the thalam us and the lentinform nucleus, thus at the border between telencephalon and diencephalon. The coronal section that was chosen right here, cut s though the head of the caudate nucleus, which protrudes into the anterior horn of the lateral ventricle. The anterior lim b of the internal capsule passes guess ween the basal nuclei, that are positioned close to each other, and because of the alternating arrangem ent of grey and white m at ter provides the grey m at ter of the nuclei a striated look (corpus striatum). The coronal section (b) illustrates the close topographical relationship bet ween the caudate nucleus and the corpus callosum, which in this im age is positioned supero-m edial to the caudate nucleus and type s the roof of the lateral ventricle. The diencephalon is positioned beneath the t wo cerebral hem ispheres and above the brainstem. The anterior, superior, and lateral part s of the diencepahlon directly adjoint the telencephalon. The posterior a half of the base is positioned on the poorly de ned border with the m esencephalon, the anterior part- ned by the hypothalam us- de has been exposed. The third ventricle positioned within the m edian airplane divides the diencephalon into sym m etrical halves which both comprise paired structures (in the lateral wall of the third ventricle. As a result of the position of the person part s of the diencepahlon, the third ventricle has a quantity of extensions, or recesses. The corpus callosum and the septum pellucidum (the partition wager ween the lateral ventricles) are clearly visible and subsequently helpful anatom ical reference factors. Lo- cated beneath the corpus callosum, the thalam us occupies the biggest space of the lateral wall of the third ventricle. Due to it s projection into the ventricular lum en, the third ventricle is separated from the sm ooth wall of the hypothalam us by a furrow: the hypothalam ic sulcus. The fornix (arch) is an arch-shaped structure that passes above the thalam us and surrounds it. It extends bet ween the (hippocampus which is part of the telencephalon) and the m am m illary our bodies. Topographically, the fornix is occasionally referred to as the roof of the third ventricle. Note: One part of the diencephalon, which is particularly im portant for m otor features, the subthalam us, because of it s far lateral location, can by no means be seen on the m idsagit tal section but only on coronal (see B, p. Diencepha lon Telencephalic vesicle Diencephalic vesicle Mesencephalic (m idbrain) vesicle Rhom bencephalic vesicle Choroid plexus Lateral ventricle Diencephalon Tela choroidea a Corpus callosum Caudate nucleus Diencephalon Telencephalon Choroid plexus Telodiencephalic boundary Portion of diencephalon seen at the base of the mind Tela choroidea Fornix Third ventricle b Mam m illary physique (diencephalon) B Development of the diencephalon from the cranial neural tube Anterior view. The diencephalon and telencephalon each develop from the prosencephalon, or forebrain (see p. As developm ent proceeds, the t wo hem ispheres of the telencephalic vesicle (red) increase, overgrowing the diencephalic vesicle (blue). This process shifts the boundary wager ween the telencephalon and diencephalon until solely a sm all space of the diencephalon could be seen at the base of the developed mind (see A). The developm ent of the telencephalon (red) has progressed significantly in relation to B. The lateral ventricles containing the choroid plexus have already fully overgrown the diencephalon (blue) from behind. The m edial wall of the lateral ventricles may be very skinny and has not but fused to the diencephalon. Bet ween the telencephalon and diencephalon is a vascularized sheet of connective tissue, the tela choroidea. By the adult stage, the tela choroidea and the m edial wall of the lateral ventricle have becom e fused to the diencephalon. Rem oving the choroid plexus and the thin tela choroidea a ords a direct view of the posterom edial boundary of the diencephalon (see B, p. Epithalam us Thalam us (dorsal) Subthalamus Hypothalam us Internal capsule Globus pallidus D Organization of the diencephalon during embryonic development Coronal part of an em bryonic brain (left) and an grownup mind (right) dem onstrating the half s of the diencephalon.

A decrease of arterial blood ow within the carotid system m ost com m only end result s from an em bolic or local throm botic occlusion. Most em boli originate from atherom atous lesions at the carotid bifurcation (arterioarterial em boli) or from the expulsion of throm botic m aterial from the left ventricle (cardiac em boli). Blood clot s (throm bi) m ay be dislodged from the guts as a result of valvular illness or atrial brillation. This produces em boli that m ay be carried by the bloodstream to the mind, where they m ay trigger the practical occlusion of an artery supplying the mind. The m ost com m on example of this entails the entire distribution area of the m iddle cerebral artery, which is a direct continuation of the interior carotid artery. The cerebral veins, like the cerebral arteries, serve speci c territories (see pp. Though much much less frequent than decreased arterial ow, the obstruction of venous out ow is a vital potential reason for ischemia and infarction. With a throm botic occlusion, for example, the quantit y of blood and thus the venous strain are increased within the tributary area of the occluded vein. This causes a drop within the capillary strain gradient, with an increased extravasation of uid from the capillary mattress into the brain tissue (edema). There is a concomitant discount of arterial in ow into the a ected region, depriving it of oxygen. Vascular territory Neurological symptoms Anterior cerebral artery Paralysis of lower lim b (with or with out hem isensory deficit) Bladder dysfunction C Cardinal symptoms of occlusion of the three main cerebral arteries (after Masuhr and Neum ann) When the anterior, middle, or posterior cerebral artery becom es occluded, characteristic useful de cits happen in the oxygen-deprived mind areas equipped by the occluded vessel (see p. In m any instances the a ected artery can be identi ed based on the related neurological de cit: � Bladder weak spot (cortical bladder center) and paralysis of the lower lim b (with or without hem isensory de cit, predom inantly a ecting the leg) on the aspect opposite the occlusion (see m otor and sensory hom unculi, pp. If branches to the thalam us are also a ected, the affected person m ay also exhibit a contralateral hem isensory de cit as a result of the a erent sensory bers have already crossed below the thalam us. The extent of the infarction depends partly on whether the occlusion is proxim al or distal. Middle cerebral artery Hem iparesis (with or without hem isensory deficit) m ainly affecting the arm and face (WernickeMann t ype) Aphasia Posterior cerebral artery Hem isensory losses Hem ianopia 383 Neuroanatomy 18. A cross-section by way of the early neural tube (a) exhibits a central uid lled (cerebrospinal uid) lum en, which is surrounded by so-called "plates": � the unpaired oor and roof plate in addition to � the paired basal and alar plates. Num erous neurons develop In the basal and alar plate as properly as within the interm ediate zone. They type the grey matter because of which these areas enlarge and more and more constrict the lum en leading to the shape ation of the central canal of the spinal cord (c), which m ay becom e even obstructed in som e areas. In the grownup spinal wire, the three grey colum ns are referred to as anterior, lateral, and posterior horns. Morphologically, the grey m at ter which is surrounded by white m at ter on all sides, is considered a nucleus or nuclear group. Each of the three horns could be assigned one m ain operate based on their neurons: anterior horn: som atom otor perform; posterior horn: som atic sensation; lateral horn: control of the autonom ic features of organs. Dorsal rootlets Dorsal root with spinal ganglion Spinal nerve Dorsal ram us Ventral ram us Grey ram us com m unicans White ram us com m unicans Sympathetic ganglion the spinal colum ns encompass segem ents- similar to the indivdual vertebrae- which m eans that the vertebral canal it self is split (see C). It is simply on the openings wager ween particular person vertebrae- the intervertebral foram ina- at that the rootlets that kind the spinal nerves can both enter or exit the vertebral canal. Functionally, a spinal wire segm ent is based a longitudinal division of the spinal wire, which accommodates the cell our bodies of m otor neurons that kind precisely one anterior root. Since the spinal nerve consist s of (m otor) anterior root and (sensory) posterior root, it has m ixed capabilities. For all different spinal nerves, it could possibly be said that in m orphological time period s, a segm ent of the spinal twine is the half the place the rootlets, which m erge to form a spinal nerve, enter or exit the spinal twine. Ventral root Ventral rootlet s Meningeal department Splanchnic nerves B Structure of a spinal twine seg ment Anteriosuperior view of a spinal wire segm ent in addition to a spinal nerve. These nerve rootlet s are groups of axons, which � exit the spinal twine on ist anterior aspect (t ypically axons of m otor neurons, which time period inate in an target organ or autonom ic ganglion) or � enter the spinal twine on its posterior aspect (t ypically axons of sensory neurons, which carry inform ation from a receptor). Sensory innervation of the skin correlates with the sensory root s of the spinal nerves in D. Every spinal twine segm ent (except for C1, see below) innervates a selected pores and skin space (derm atom e).

Care have to be taken to maintain a lateral course such that the tip of the switching stick is at all times lateral to the plexus. The coracoid osteotome is now inserted by way of the M portal and positioned over the glenoid neck through the cut up and the second assistant now maximally externally rotates the arm to cause a blunt split of the medial fibers of the subscapularis. Two switching sticks, one from the A portal and one from the J portal, are used to retract the superior and inferior fibers of the subscapularis. Back bleeding is encountered from the bone and small perforators entering the bone through the subscapularis muscle stomach are cauterized. The coracoid plastic cannulated guide is introduced through the M portal and the final place of the graft is ascertained. The guide is inserted and 2 information wires are drilled into the glenoid neck with the tips of the wires uncovered outside of the affected person and held with artery forceps. These wires must be parallel to each other and the switching stick inserted via the A portal to guarantee parallelism. The cannulated drill information is used to assist drilling both cortices and the anticipated length of screws noted. The cannulated trocar from the Latarjet set is threaded over the inferior guide wire from the posterior pores and skin puncture and is advanced anteriorly till it appears on the anterior glenoid neck. The information wires are now faraway from the posterior side of the patient, forsaking the secured the cannulated trocar. Coracoid retrieval and ultimate preparation: the arm is flexed and the double cannula is launched (with the handle dealing with superiorly through the M portal). Visualizing from the I portal, the cannula and its 2 top hat screws are superior so as to mobilize and transfer the coracoid. The surgeon eburnates the undersurface of the coracoid using a 5-mm burr by way of the J portal. Complete decortication of the undersurface of the coracoid is advisable to guarantee union. It must be noted that the coracoid have to be held nonetheless to stop inadvertent slips inflicting damage to the important neurovascular constructions. Coracoid fixation: the arm is internally rotated and the coracoid is inserted through the subscapularis break up. The inferior hole (adjacent to the origin of the conjoined tendon) in the coracoid is guided over the cannulated trocar. The visualization is modified between the J and the D portal to ensure that the graft is well in contact with the glenoid. Any failure of conformity may be addressed by burring the sharp edges through the E portal. The shoulder is taken via abduction and external rotation and evaluated for stability and graft fixation. Postoperative Protocol Most sufferers are discharged the subsequent morning after their postoperative x-rays are checked. No physiotherapy is really helpful initially and sufferers are encouraged to actively elevate and move their arm. Complications encountered embrace the following: Hematoma postoperatively: Seen sometimes, patients often complain of postoperative swelling of the hemithorax. This is a minor complication and is managed by reassurance, relaxation, analgesia, and cold packs. Despite best efforts, transient neuropraxias have been famous by the senior author. Transient suprascapular nerve palsy on account of a long superior screw directed towards the spinoglenoid notch has occurred. Transient axillary nerve palsy: the writer has experienced 1 case out of 500 patients who suffered from transient axillary nerve palsy, which recovered utterly in 3 months. Graft positioning: this stays the "Achilles heel" of both open and arthroscopic Latarjet. Various respected surgeons have proposed their ideologies; nevertheless, a consensus fails to exist.
Syndromes

Speci cally these nerves are the lesser occipital, great auricular, transverse cervical, and supraclavicular nn. Note: the transverse cervical nerve passes beneath the exterior jugular vein and kind s an anastom osis with the cervical department of the facial nerve. This m ixed loop contains m otor bers from the facial nerve and sensory bers for the neck from the transverse cervical nerve. The investing layer of the deep cervical fascia has been rem oved over the posterior cervical triangle to expose the prevertebral layer of the cervical fascia, which is fused to the pretracheal lam ina on the level of om ohyoid m uscle (see p. Note the exterior branch of the accent nerve, which passes to the trapezius m uscle. This damage restricts the m obilit y of the scapula, and the affected person m ay be unable to elevate the higher lim b beyond 90�. In this dissection, the pretracheal layer of the deep cervical fascia has additionally been rem oved to display the om ohyoid m uscle, which is enveloped by that fascia. Note the phrenic nerve, which runs obliquely over the scalenus anterior m uscle to the thoracic inlet. The sternal end of the clavicle, the anterior end of the rst rib, the m anubrium sterni, and the thyroid gland have been rem oved to expose the thoracic inlet. Note the course of the following buildings: the interior thoracic artery descends parallel to the sternum. In patient s with coronary heart illness, the internal thoracic artery may be m obilized and anastom osed to the coronary artery past the point of the stenosis. The sympathetic trunk, vagus nerve, phrenic nerve, and parts of the brachial plexus are visible, the lat ter passing through the interscalene house (see C). Note also the term ination of the thoracic duct at the jugulosubclavian venous junction and the left recurrent laryngeal nerve. This department of the vagus nerve winds across the aortic arch and ascends to the larynx. It is bounded by the sternocleidom astoid m uscle, the posterior stomach of the digastric m uscle, and the superior stomach of the om ohyoid m uscle. The subm andibular gland can be seen at the inferior border of the m andible and the sternocleidom astoid m uscle has been retracted posterolaterally. The sternocleidom astoid region and carotid triangle have been dissected together with adjacent portions of the posterior and anterior cervical triangles. The carotid sheath has been rem oved on this dissection together with the cervical fasciae, sternocleidom astoid m uscle, and om ohyoid m uscle to dem onstrate all necessary neurovascular structures in the neck: � Com m on carotid artery with it s division into the internal and exterior carotid arteries � Superior and inferior thyroid arteries � Internal jugular vein � Deep cervical lymph nodes alongside the interior jugular vein � Sympathetic trunk together with it s ganglia � � � � � Vagus nerve Hypoglossal nerve Accessory nerve Brachial plexus Phrenic nerve the phrenic nerve originates from the C3�C5 segm ent s and subsequently is part of the cervical plexus. The m uscular landm ark for finding the phrenic nerve is the scalenus anterior, along which the nerve descends in the neck. The (posterior) interscalene area is positioned guess ween the scalenus anterior and m edius and the rst rib and is traversed by the brachial plexus and subclavian artery. The subclavian vein passes deeply by way of the interval type ed by the scalenus anterior, the sternocleidom astoid m uscle (resected), and the rst rib (the anterior interscalene space). The principal arterial vessel on this region is the occipital artery, the second branch arising from the posterior aspect of the exterior carotid artery. The m edially located greater occipital nerve is a dorsal ram us of the C2 spinal nerve, while the laterally situated lesser occipit al nerve is a ventral ram us of C2 that arises from the cervical plexus (see p. The lym ph nodes are positioned on the websites where the nerves and veins em erge by way of the cervical fascia. Note the accent nerve, which crosses the lat-eral cervical triangle at a relatively super cial stage. Topographical Anatomy Occipital artery Splenius capitis Sternocleidom astoid Sem ispinalis capitis Obliquus capitis superior Rectus capitis posterior m inor Greater occipital nerve Vertebral artery Rectus capitis posterior m ajor Obliquus capitis inferior Spinous course of, axis (C2) Third occipital nerve Sem ispinalis cervicis m uscle Splenius capitis Suboccipital nerve Occipital artery Great auricular nerve Transverse means of atlas (C1) Cervical posterior intertransversarius Longissim us capitis Sem ispinalis capitis B Right suboccipital triang le Posterior view. The suboccipital triangle is bounded superiorly by the rectus capitis posterior m ajor, laterally by the obliquus capitis superior, and inferiorly by the obliquus capitis inferior. This m uscular triangle may be seen solely after the trapezius, splenius capitis, and sem ispinalis capitis m uscles have been rem oved.
A optimistic result with important enchancment following a diagnostic intra-articular injection of a short- or intermediate-term anesthetic agent helps the diagnosis. If the cuff restore fails to heal and both a symptomatic residual partial defect or a full-thickness defect are present, consideration may be given to a revision full-thickness repair. Confirm that the deep margin of the rotator cuff could be reduced to the footprint on the higher tuberosity with the arm in an adducted position. Using a loop grasper, cut back the deep layer of cuff to the tuberosity before passing the spinal needle through the deep layer for restore. The spinal needle ought to be passed relatively parallel to the tuberosity before getting into the cuff to keep away from a pressure mismatch between the superficial and deep cuff layers. Retrieve the delivered monofilament suture and the chosen anchor suture limb at the same time to avoid entanglement because the suture is shuttled from deep to superficial through the cuff. Stress distribution in the supraspinatus tendon with partial-thickness tears: an evaluation using a two-dimensional finite factor mannequin. Intra-articular partial-thickness rotator cuff tears: evaluation of injured and repaired strain habits. Debridement of partial-thickness tears of the rotator cuff without acromioplasty - long-term follow-up and review of the literature. Arthroscopy of the shoulder within the administration of partial tears of the rotator cuff: a preliminary report. In situ transtendon repair outperforms tear completion and restore for partial articular-sided supraspinatus tendon tears. Predictive elements of delicate, residual shoulder symptoms after transtendinous arthroscopic cuff repair: a clinical examine. Arthroscopic transtendon restore of partial-thickness articular-side tears of the rotator cuff: anatomical and clinical study. Long-term outcome for arthroscopic restore of partial articular-sided supraspinatus tendon avulsion. Surgical remedy of incomplete thickness tears of the rotator cuff: long-term follow-up. A comparison of two restore strategies for partial-thickness articular-sided rotator cuff tears. The arthroscopic administration of partialthickness rotator cuff tears: a systematic evaluate of the literature. Magnetic resonance imaging, magnetic resonance arthrography and ultrasonography for assessing rotator cuff tears in individuals with shoulder pain for whom surgical procedure is being thought-about. A comparability of medical estimation, ultrasonography, magnetic resonance imaging, and arthroscopy in figuring out the size of rotator cuff tears. Comparison of ultrasonographic, magnetic resonance imaging, and arthroscopic findings n seventy-one consecutive cases. Interobserver agreement within the classification of rotator cuff tears utilizing magnetic resonance imaging. Pathoanatomy is diversified and might embody damage to the posterior capsuloligamentous structures, bony glenoid or humerus, rotator interval, and rotator cuff. While posterior shoulder instability was historically treated with open surgery, this required massive surgical dissections and reported failure charges ranged from 30% to 70%. Advantages of an arthroscopic strategy include its minimally invasive nature in addition to the flexibility to tackle the number of pathoanatomy seen in posterior instability. Senior writer performing (A) a posterior load and shift test and (B) the jerk test. Note that in posterior instability, the patient may have apprehension but usually complains of posterior ache or discomfort instead. Controversial Indications Posteroinferior-dominant multidirectional instability Posterior glenohumeral instability with significant glenoid or humeral bone loss Pertinent Physical Findings Posterior load and shift test: Patient is placed supine on the examining desk to stabilize the scapula. The arm is positioned in roughly 20 degrees of abduction and ahead flexion. A slight axial load is first applied to heart the humeral head within the glenoid, and the examiner then attempts to translate the humeral head posteriorly. Jerk test: Patient is placed supine on the inspecting table to stabilize the scapula. The arm is then barely adducted and a posterior axial load is utilized alongside the axis of the humerus. The examiner seems for a dimple or sulcus between the humeral head and acromion higher than 1 cm.

Displaced fracture of the distal radius in children: components liable for redisplacement after closed discount. If there have been none current I would make the patient as comfortable as possible with immobilization and analgesia and I would request compartment syndrome observations. I would then organize admission for operative fixation on the subsequent out there trauma record. My purpose would be to carry out a closed discount underneath anaesthetic and if there was residual instability I would stabilize the fracture with wires. In fractures with a large Thurston-Holland fragment, screw fixation via this fragment into the other metaphysis, keeping parallel to however staying well away from the physis, is acceptable. However, in this case the metaphyseal fragment is small and this would not be attainable. These would be directed from distal to proximal, one from each side, with the procedure carried out beneath fluoroscopic management to allow for a single cross. I would aim to insert them from simply adjoining to , however not via, the articular cartilage of the femur. The biggest linear development in the lower extremity happens on the distal femoral progress plate. Partial or whole progress arrest by can be attributable to either the initial insult or during surgery by overzealous reduction, by wires or screws, or each. Wires have a small footprint and cross-sectional space so are unlikely to lead to growth disturbance, though I would keep away from a number of passes-hence the use of image management. In this case the wires cross the physis obliquely making them extra more probably to injure a greater space of progress plate. I would permit lively and passive motion on the knee but insist strictly on no weight-bearing with crutches. At each appointment I would carefully assess the leg clinically and radiologically for vary of motion, angular deformity, and leg-length discrepancy. In 2002 Eid and Hafez reported on a retrospective case collection of 151 of those accidents. What are your options for (1) emerging angular deformity and (2) total growth arrest if they were to occur Angular deformity from partial development arrest could additionally be managed by osteotomy or by hemiepiphysiodesis. Complete progress arrest without angulation in a toddler with a contralateral open development plate can be greatest managed by a contralateral epiphysiodesis if predicted to be lower than 5 cm. Answers these are anteroposterior and lateral views of a skeletally immature knee displaying a big lipohaemarthrosis and a tibial eminence (or spine) fracture. Occasionally, manipulation into extension can reduce the fracture and this should be adopted by brace or solid immobilization in as close to extension as attainable. If satisfactory reduction is achieved then the patient could be discharged home with a 1-week fracture clinic appointment. The delicate tissue interposing between the fracture fragments can be the anterior horn of the lateral meniscus, the anterior horn of the medial meniscus, or the intermeniscal ligament. I would goal to remove the impingement to reduction-usually by hooking the intermeniscal ligament anteriorly and pulling it out of the greatest way. Extending the knee typically allows for discount of the fragment, however I could an additional excessive medial or lateral portal in order to utilize a pusher on the fragment earlier than holding it in place with a percutaneous K-wire. I would then use cannulated screw fixation after the delicate tissue interposition has been eliminated. This could be carried out via a excessive anteromedial portal with the knee flexed to 90� and a single move of the guidewire from a superoanterior to an inferoposterior course through the proximal tibial physis. A partially threaded screw with no washer can then be passed over the guidewire to hold the discount. Respect for the expansion plate, hardware placement, and potential problems have to be borne in thoughts always. For rehabilitation the kid can partially weight-bear on crutches with no brace and begin light range-of-movement workouts with the physiotherapist after 2 weeks. Avulsion fracture of the tibial eminence: remedy by open reduction and pinning. Answers this is an anteroposterior view of a skeletally immature affected person demonstrating a tibia and fibula facture on the same level. The majority of tibial fractures in kids can be managed non-operatively with excellent outcomes.

Plane of part in B Lateral ventricle Caudate nucleus, head Corpus striatum Amygdala Caudate nucleus, body Putam en Caudate nucleus, tail Lateral amygdaloid nucleus Cortical amygdaloid nucleus Lateral olfactory stria C Relationship betw een the caudate nucleus and lateral ventricle Left lateral view. In the ventricular system, we can now see the oor of the third ventricle (see B) and the surrounding hypothalam us. The large descending pathway, the corticospinal tract, passes via the interior capsule, which has a som atotopic group. Precentral gyrus Thalam us Internal capsule, posterior lim b Left lateral ventricle Third ventricle Insular cortex Globus pallidus Caudate nucleus Fourth ventricle Claustrum Putam en B Ventricular system Left lateral view. This section shows the complete width of both the inferior horn of the lateral ventricle and the claustrum (believed to be essential within the regulation of sexual behavior). While the airplane in A passed by way of the anterior com m issure, this m ore occipital aircraft slices the m am m illary bodies (see E). Pathological modifications within the m am m illary bodies can be discovered during autopsy of continual alcoholics. An necessary a part of the lim bic system, the m am m illary bodies are connected to the hippocampus by the fornix (see F). Due to the anatom ical curvature of the fornix, its columns are visible in m ore frontal sections (see A), while it s crura seem as extensively separated buildings in m ore occipital sections (see C, p. The septum pellucidum stretches guess ween the fornix and corpus callosum, form ing the m edial boundary of the lateral ventricles (see A and D). The rst construction of the brainstem, the pons, can be identi ed on this part. Plane of section in D Septum pellucidum Fornix Septum pellucidum Fornix, colum n Corpus callosum, physique Fornix, physique Mam m illary our bodies Lum en of third ventricle Mam m illary physique E Midsag ittal part by way of the diencephalon and brainstem Lateral view. Its body borders the body of the lateral ventricle, and a sm all portion of its tail borders the inferior horn of the ventricle (see C and E). Because the pinnacle and body of the caudate nucleus rim the lateral aspect of the anterior (frontal) horn and the body of the lateral ventricle, the caudate nucleus has a curved shape sim ilar to that of the lateral ventricle (see C). Thus, the tail of the caudate nucleus is ventral and lateral in relation to it s head and physique. Panel E reveals that a coronal part through the tail of the caudate nucleus cuts the occipital parts of the putamen. A section in a slightly m ore occipital plane m ay not contain any part of the basal ganglia in any respect (see B). This is the rst airplane that shows the choroid plexus, which can be seen throughout the lateral ventricles. The choroid plexus extends from the interventricular foram en (not seen here) into the inferior horn. Because the foram en lies anterior to the thalam us, the plexus may be seen solely in coronal sections that additionally move through thalam ic constructions. Ventral to the thalam us are the purple nucleus and substantia nigra; these are important m idbrain constructions that bulge into the diencephalon and extend alm ost to the extent of the globus pallidus (not seen here; see B). This section also exhibits how the bers of the corticospinal tract pass via the posterior limb of the interior capsule and proceed into the cerebral peduncles and pons. Plane of section in A Red nucleus Substantia nigra Caudate nucleus, head Caudate nucleus, tail Body of lateral ventricle Tem poral horn Plane of section in A Occipital horn B Red nucleus and substantia nig ra Midsagit tal part. This part passes via the posterior limb of the interior capsule (see additionally C, p. The medial and lateral geniculate bodies, which are component s of the auditory and visual pathways respectively, seem as t wo darker nuclei that ank the thalam us on the proper and left sides at the sam e stage because the com m issure (see F). Here the middle cerebellar peduncle passes laterally towards the cerebellar hem ispheres. Lateral ventricle, physique Caudate nucleus Anterior horn Putam en Tem poral horn Plane of section in D Occipital horn Third ventricle Pineal gland Medial geniculate physique Lateral geniculate physique E Topog raphical relationship betw een the caudate nucleus and ventricular system F the diencephalon (w ith geniculate bodies) and brainstem Posterior view. The occipital part of the hippocampus can be seen below the m edial wall of the lateral ventricle. The cerebellum is related to the brainstem by three white-m at ter stalks: the superior cerebellar peduncle (m ainly e erent), center cerebellar peduncle (afferent), and inferior cerebellar peduncle (a erent and e erent). The superior cerebellar peduncle begins on the posterior aspect of the pons and thus seems in a later section (see B). The super cial veins have been rem oved from the brain when this section was prepared, and only the inner cerebral veins appear in this and the following section. Superior cerebellar peduncle Middle cerebellar peduncle Inferior cerebellar peduncle Rhom boid fossa B Cerebellar peduncles on the brainstem a Posterior view; b Lateral view.

Rinderpest (German for "cattle plague") is thought to have come originally from Asia, and was moved to Africa and Europe through the motion of cattle. The eighteenth and nineteenth centuries noticed many outbreaks in Europe, and within the late nineteenth century an enormous outbreak in Africa is thought to have killed eighty to ninety percent of all of the cattle in southern Africa. Experiments with inoculation to produce immunity started within the eighteenth century, and continued intermittently. In 1762 the primary veterinary faculty opened in France to educate the management of Rinderpest. In 1918 an early vaccine was developed through the use of inactivated tissues from contaminated animals. In the early twentieth century Rinderpest was such a serious problem that it sparked the event of the World Organization for Animal Health. In 1957 a reliable vaccine was developed, and real control of the illness became a possibility. It was not till the mid-1990s, nevertheless, that the world eradication program launched. It was remarkably profitable: the last recorded case of Rinderpest was in 2001, and in 2011 Rinderpest grew to become the second virus declared eradicated (the first was Variola virus, the trigger of smallpox). Rinderpest virus is closely related to Measles virus that infects people, and is assumed to be the progenitor of Measles virus. The eradication of Rinderpest lends hope that Measles virus could also eventually be eradicated through vaccination. Viral elements may be seen in numerous levels of meeting; commonest are the lengthy nucleocapsid constructions that eventually get packaged with a host-derived membrane spiked with viral proteins. Rous continued to attempt to isolate the virus and its cancer-causing abilities for the next few years, after which moved on to other work. The significance of his work was not appreciated until much later, however in 1966 he acquired the Nobel prize for the invention he had made fifty five years earlier. Temin and Baltimore shared a Nobel prize for the discovery of reverse transcriptase in 1975. This potential cancer-causing gene, referred to as an oncogene, occurs in all greater organisms, including people. In 1989 a 3rd Nobel Prize was given to Harold Varmus and Michael Bishop for the discovery of the oncogene. The conversion of a standard cell to a cancerous cell can happen by way of many alternative routes, and viruses are simply one of these routes, but in all circumstances this conversion is rare in nature. The virus was discovered in some batches of the stay attenuated vaccine for polio in 1960. Most people who obtained the Salk vaccine for polio previous to 1961 were in all probability also inoculated with Simian virus forty, and the virus may have been in the Sabin vaccine too. Simian virus 40 is found incessantly in the human inhabitants now, however seems to be latent, though there have been ideas that it could probably be involved in some kinds of human cancerous tumors. During the Fifties and 1960s the thought of rising cells in culture for experimental research was being developed. Monkey cells had been a well-liked alternative for establishing cell strains as they had been just like human cells. In this course of latent viruses typically emerged, and these had been numbered sequentially as they were found. In all there have been around eighty of those simian viruses, but only a few have been studied in depth, with Simian virus 40 being the most well studied. This might be as a end result of when the virus was injected into hamsters, tumors developed. This illustrates the bias in virus research, where pathogenic viruses have been studied whereas nonpathogenic viruses, probably the commonest type in nature, have been ignored. Simian virus forty was an essential device in understanding the basic principals of molecular biology, and it has been used as a system to study many genes in mammalian cells. In surveys of wild fish, the virus is extensively present in many marine fish, usually without illness. In farmed fish, numerous virus strains have emerged to trigger illness in several components of the northern hemisphere prior to now few many years, including Scandinavia, the British Isles, Korea and Japan, and the Great Lakes area of the United States. The virus continues to be found in new areas, in large part as a outcome of spillover from pure infection in wild fish.
Amul, 26 years: Joe Burns receives consulting income from Conmed and Mitek, research help from Conmed, and textbook royalties from Wolters Kluwer Health.
Frillock, 44 years: Immediate open anterior reduction and antero-posterior fixation/fusion for bilateral cervical locked sides.
Aschnu, 58 years: Jerosch, 24 Le Lievre and Takagi, 22 and LaFosse et al 25 report satisfactory outcomes utilizing barely different circumferential capsular releases.
Hengley, 38 years: Covalent disulfide bonds can kind between the sulfhydryl groups of cysteine facet chains to hold regions of a polypeptide chain close to one another; together with hydrogen bonds, ionic bonds, hydrophobic interactions, and van der Waals forces, this creates the final conformation of the protein (tertiary structure).
Khabir, 41 years: Smoking has been proven to enhance the incidence of delayed and non-union in tibial fractures-indeed even being a previous smoker increases the probability of non-union.
Koraz, 52 years: The second issue was the worldwide spread in tropical and subtropical areas within the 1990s, of a sort of whitefly generally recognized as biotype B.
Dolok, 40 years: An arthroscopic passive compression check or Mayo shear take a look at can also be carried out to evaluate for superior labrum instability.
References

Desarrolló: Grupo Guadalupe S.R.L.