
Arthur Wakefield Baker, MD

https://medicine.duke.edu/faculty/arthur-wakefield-baker-md
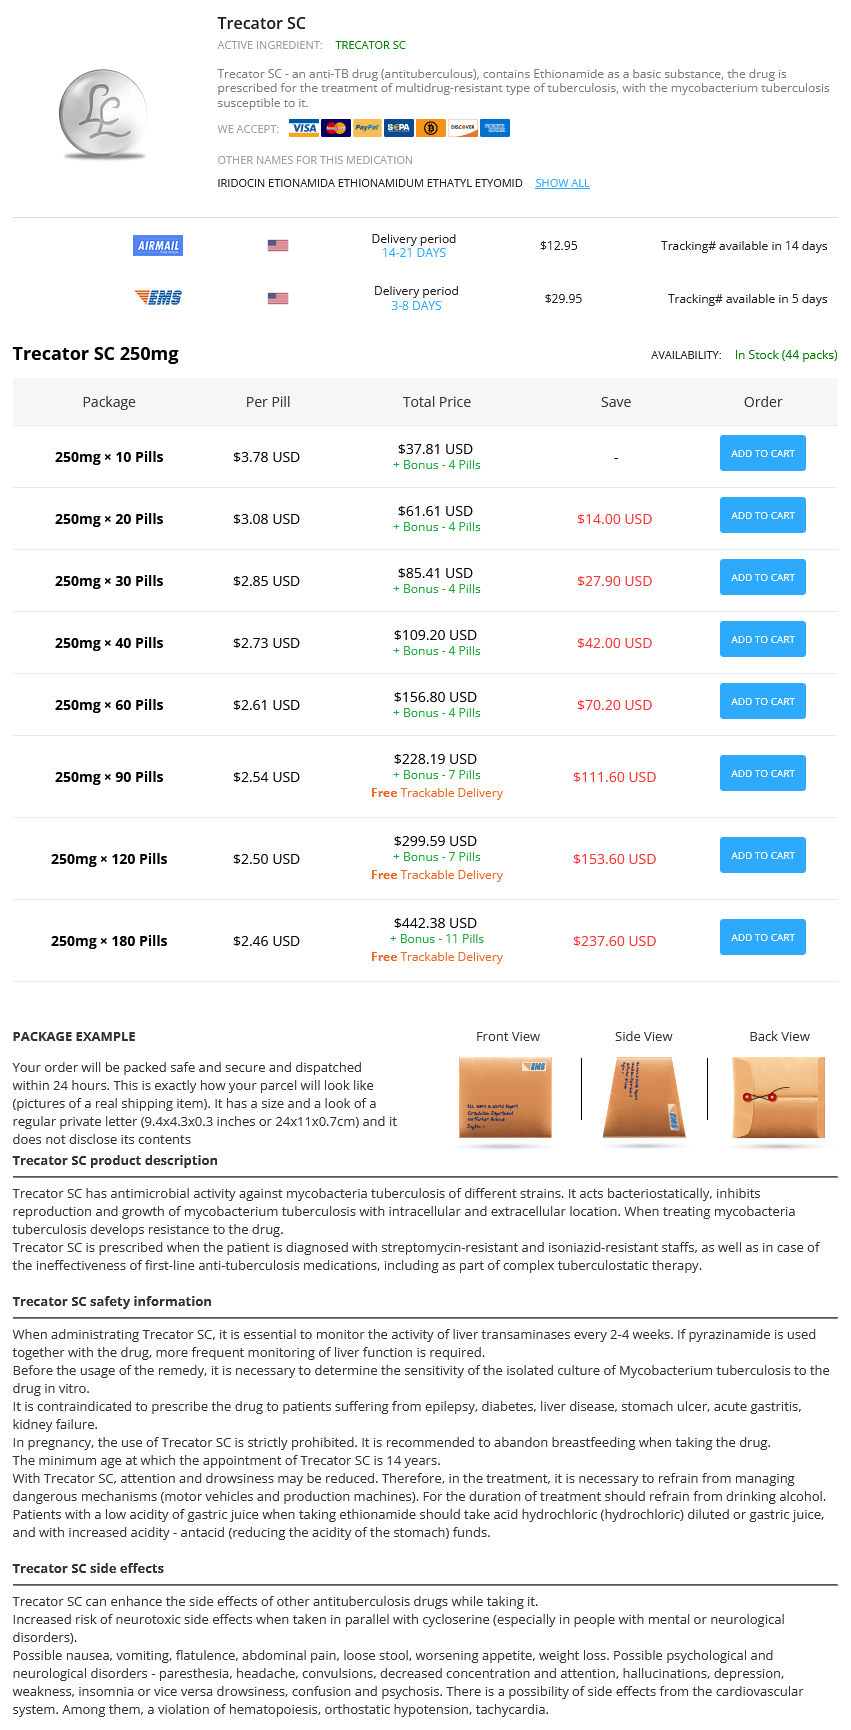
Trecator SC dosages: 250 mg
Trecator SC packs: 10 pills, 20 pills, 30 pills, 40 pills, 60 pills, 90 pills, 120 pills, 180 pills

A, Lateral radiograph displaying a destructive tumor with anterior extension involving the distal femoral metaphysis. A, Anteroposterior radiograph exhibiting a calcified harmful tumor mass involving proximal humerus. Note circumferential cortical destruction and extension to gentle tissue with radiating mineralized spicules. Such a mineralization sample can be radiographically misinterpreted as an osteosarcoma. B, Fatsaturated T2-weighted axial magnetic resonance image displaying excessive sign intensity tumor with circumferential extension to paraosseous delicate tissue. C and D, Gross photographs of the bisected resection specimen in A and B displaying fleshy tumor mass involving medullary cavity of proximal humerus with circumferential delicate tissue extension. A and B, Oblique and anteroposterior radiographs displaying a calcified tumor involving the scapula. C, Resected specimen reveals a tan lobulated tumor extending anteriorly and posteriorly to the periscapular gentle tissue. A, Anteroposterior radiograph exhibits a calcified mass in the right paraspinal area. B, Axial computed tomogram demonstrates a calcified mass within the delicate tissue of the best paraspinal region. A, Low power photomicrograph exhibiting small cell tumor with discreet ill-defined patches of early cartilaginous differentiation shown as less cellular areas. B, Interface between an island of atypical cartilage and small cell undifferentiated components of the tumor. C, Small cell proliferation with distinguished open vascular channels of assorted sizes and shapes (�100). D, Higher magnification displaying stable proliferation of undifferentiated small cells. A and B, Biphasic nature of mesenchymal chondrosarcoma exemplified by ill-defined islands of cartilaginous differentiation and poorly differentiated small cell component. C, Large space of cartilaginous differentiation with properly developed hyaline cartilage matrix and lacunar pattern of cartilage cells. D, Higher magnification of poorly differentiated considerably spindle-cell part of the tumor. A and B, Interface between the cartilaginous areas and a small cell poorly differentiated component of the tumor. Note ill-defined irregular interface between the hyaline cartilage areas and undifferentiated element. C, Large cartilaginous area of the tumor with nicely developed hyaline cartilage matrix. D, Intermediate power view of poorly differentiated small cell part of the tumor. A, Low power photomicrograph of the central portion of a giant cartilaginous space showing vascular ingrowth and enchondral ossification of the calcified matrix. C and D, Variations of morphology inside the poorly differentiated part of the tumor displaying spindle (C) and spherical (D) cell variants within the identical tumor. Inset, Higher magnification showing nuclear details of the spherical cell component of the tumor. A and B, Low energy photomicrographs exhibiting dense proliferation of undifferentiated tumor cells with prominent capillary vasculature. C and D, Low and intermediate power photomicrographs displaying ill-defined islands of cartilaginous differentiation. A and B, Low and intermediate power photomicrographs exhibiting spindle cell variant of mesenchymal chondrosarcoma. C and D, Low and intermediate power photomicrographs showing mesenchymal chondrosarcoma with prominent vasculature. A-D, Intermediate and high energy photomicrographs of mesenchymal chondrosarcoma displaying proliferation of brief plump spindle cells. A-D, Low and excessive energy photomicrographs of mesenchymal chondrosarcoma show intense immunoreactivity for S-100 protein in cartilaginous areas and absence of staining in primitive mesenchymal cells.
Diseases

The intertrabecular areas of the medullary cavity consist of adipose tissue, fibrovascular buildings, and hematopoietic tissue. The trabecular bone with its excessive surface/ volume ratio is vulnerable to fast turnover, and therefore most sensitively displays alterations in mineral homeostasis. Center has been replaced by developing diaphysis with zones of enchondral ossification at both ends. At this stage main spongiosa with energetic enchondral ossification occupies most of the bone length within the metaphyseal portions while the growing shaft is a comparatively minor component of the size. Whole-mount section of fetal foot shows primary topographic options of quick tubular and epiphysioid bones. Growth plate or physis outcomes from formation of a secondary ossification center within the cartilage mass on the finish of the cartilage model. Increase in size outcomes primarily from cartilage-cell proliferation and interstitial progress in the cartilaginous physis. Collagen Collagen is the most abundant protein in the physique and the major natural part of extracellular matrix in bone. The collagen molecule includes three chains, each of which incorporates a repeating tripeptide sequence of glycine-x-y, by which x and y are frequently proline and hydroxyproline. These three chains are individually synthesized on ribosomes and subsequently are assembled right into a triple helix. The cross-linking among these molecules is responsible for the formation of the fibrillar matrix. The architecture of collagen fibers reflects the integrity of bone and its stage of maturation. In normal adults, virtually all bone collagen is deposited in parallel lamellar bundles as seen by polarizing microscopy, therefore the time period lamellar bone. Woven bone (fiber bone) is shaped at sites of early endochondral and membranous ossifications and in fracture callus, periosteal reactions, endosteal therapeutic processes, and rapidly formed tumor bone. The recognition of woven bone and its distinction from mature lamellar bone are tremendously facilitated by means of polarization microscopy. Proteoglycans Proteoglycans are the most important noncollagenous natural elements of skeletal matrices. Proteoglycans encompass a core of hyaluronic acid with protein facet chains lined by a variety of sulfated glycosaminoglycans. They are primarily assembled and sulfated within the Golgi equipment after the protein moieties have been synthesized by the ribosomes. In the presence of water, the hydrophilic macromolecule of the protein polysaccharide inflates to type a physique with a shape analogous to a test tube brush with the consistency of a stiff gel. The size and consistency of the eight 1 General Considerations Epiphysis Physis Metaphysis (anatomic) On its initial look within the skeleton, calcium phosphate exists in a comparatively poorly crystallized form. The lamellar maturation of bone is associated with conversion of the mineralized deposits into a hydroxyapatite with a more distinct crystalline sample. Osteoblasts have a outstanding Golgi apparatus and are rich in tough endoplasmic reticulum, resulting in outstanding basophilia. These features replicate their lively participation in mineralization and within the strategy of natural matrix production. When engaged within the synthesis of lamellar bone, osteoblasts are polarized in relationship to the underlying osteoid seam. These cells are able to skeletal synthesis at a slower price than activated cuboidal or columnar osteoblasts. They also might act as a barrier that separates the bone fluid compartment each anatomically and functionally from the final extracellular fluid. Osteocytes Osteocytes symbolize specialised cells which were integrated into the bone matrix. They are able to perilacunar matrix synthesis and mineralization, which end in progressive diminution of lacunar measurement. Osteocytes which may be older and therefore deeper within the matrix could assume osteoclastic options and resorb bone. Osteoclasts Osteoclasts are massive, multinucleated cells that are responsible for the resorption of bone and calcified cartilage. Anatomically and developmentally, the metaphysis is outlined as a slender zone just adjacent to the cartilaginous progress plate (physis) by which primary spongiosa is first shaped in the strategy of enchondral ossification.

Paradoxically, it has been shown that tumor cells exhibiting elevated levels of laminin and fibronectin floor receptors have the next metastatic potential in contrast with those that have minimal levels of those receptors. Thus to develop metastatic foci, the tumor cells 1220 19 Metastatic Tumors in Bone should keep a point of adherence to the intercellular matrix components. In basic, some insufficiency of cell adhesion and junction techniques may be documented in most cancers. Tumor cells that invade vessels have the next capability to degrade the stromal matrix than different tumor cells. The enzymatic activity of tumor cells plays an essential function in the growth of metastases. The involvement of several completely different proteases, including urokinase, plasminogen activator, cathepsins B and D, and numerous metalloproteases produced directly by tumor cells, play an important position within the invasive progress and development of metastasis. Therefore their roles in invasive progress and metastasis rely not only on the level of the enzyme, but additionally on the presence of adequate amounts of their activators and inhibitors. The activity of this enzyme can be correlated with the metastatic potential of a number of experimental and human tumors. Overall, an upregulation of multiple proteolytic enzymes of the so-called plasminogen cascade have been documented in malignant tumor cells and have been linked to their invasive and metastatic potential. The ability to induce vascular progress is one other factor that secures the survival of an enlarging tumor mass. The ability of tumor cells to induce proliferation of vascular cells by way of numerous progress components such as endothelial development factor and fibroblastic growth issue has recently been extensively studied. The tumor cells that invade the vessels and circulate within the lymph or blood interact with cellular and humoral components of the surroundings. The interaction of tumor cells with platelets and different blood clotting elements, both circulating and cell fastened, is a crucial factor in the promotion of tumor cell thrombosis of peripheral sinusoids and growth of metastatic foci. Moreover, the tumor cells of a metastatic focus must retain their stromal destructive activities and work together with different cells of the brand new environment to survive and type clinically detectable nodules. Osteolysis is pushed by osteoclastic resorption of bone, the management of which comes underneath a variety of influences. Carcinomas of the prostate and breast, in addition to neuroendocrine tumors, can induce predominately blastic or sclerotic metastases. These components induce bone formation by inducing osteoclast apoptosis while stimulating osteoblast differentiation and proliferation. In addition, the vertebral plexus of veins is valveless, and the retrograde venous stress is usually elevated in the abdominal and chest regions. This permits a retrograde flow of blood to bypass the caval system and to reach the bones of the vertebral column. Thus the biologic circumstances of bone tissue must even be important components in selling the expansion of tumor cells that reach the marrow through the venous and arterial blood network. Autopsy reports of enormous series of sufferers have proven that, with gross examination and limited sampling, 19 Metastatic Tumors in Bone 1221 skeletal metastases could be documented in 30% of sufferers who died of carcinoma, with specific carcinomas such as breast or prostate most cancers current in practically 85% of sufferers autopsied. This is consistent with observations by Jaffe, who acknowledged that if extensive skeletal sampling had been to be performed, metastases could be documented in 70% of patients who died of carcinoma. Therefore they may not detect metastatic tumors which are primarily associated with bone destruction and minimal or no osteoblastic exercise. Cortical disruption, extension into delicate tissue, and periosteal new bone formation could be current. Often, focal sclerosis is seen inside lytic lesions, and therefore many skeletal metastases produce a mix of lytic and blastic appearances. In common, a lytic versus blastic radiographic look of a metastatic tumor in bone outcomes from a prevalent bone resorptive (destructive) or stimulating (osteoblastic) exercise of the tumor. Consequently, such bones as the vertebrae, pelvis, ribs, skull, sternum, proximal femur, and humerus are most regularly concerned. These sites correspond to areas that contain hematopoietic marrow, which has a wealthy sinusoidal vascular network. This function and the presence of venous plexus linked with abdominal and thoracic organs might promote metastasis in these areas. Metastases that predominantly involve fatty marrow distal to elbow and knee joints and the mandible are uncommon in adults. In some sufferers, it can be a presenting sign of a clinically silent main tumor that, most frequently, is situated inside the thoracic or stomach organs. Although it could happen in lots of frequent cancers, carcinoma of the lung is essentially the most frequent malignancy during which so-called acral metastases occur.

A, Lowpower magnification of spindle-cell neoplasm is according to malignant fibrous histiocytoma. B, Higher-power magnification of A shows spindle tumor cells with distinguished atypia. Insets, Anteroposterior and indirect views on plain radiographs show lytic mass of proximal tibial shaft. Note increased mineralization sample of bone adjoining to lytic space comparable to bone infarcts. The tumors expected to develop, however, would replicate the cell types involved in such a reparative process. Thus it seems clear that an in depth pathogenetic relationship exists between bone infarcts and the associated sarcomas. The reparative, predominantly fibroblastic tissue, which has a comparatively excessive degree of proliferative activity within the border zone, could be the presumptive origin of this malignancy. The rate of corrosion varies based on particle dimension; metallic solubility; environmental pH; and concentrations of the metal, negative ions, and oxygen. The steady exposure of tissue to metallic corrosion merchandise is taken into account to be an initiating issue. A current report of 20 examples of malignant fibrous histiocytomas creating as induced sarcomas in bone famous that a median dose of 5700 rads was given for either nonosseous circumstances or preexisting skeletal lesions. In a sequence of 91 bone sarcomas that developed in patients handled with radiotherapy with different modalities for earlier malignancies and in sufferers who had genetic predispositions, the latency period was shortened by method of adjuvant chemotherapy. Internal deposits of radioactive elements of radium and mesothorium from industrial exposure have been found in painters of watch dials, chemists, and technicians. Internal deposits of radium salts and thorium have been present in some individuals who use them in medical work. Once in the physique, these substances behave like calcium, depositing in areas of active bone turnover. Their deposition predisposes the bone to the event of osteosarcoma and other malignancies. Bone harm, including osteopenia, necrosis, spontaneous fractures, and osteosarcoma, outcomes from many a long time of fixed irradiation of bone cells and matrix and mineral formation affected by the -rays emitted from these deposits. It has a complex genetic background with 17 genetic causes transmitted in autosomal dominant or recessive patterns. In radiographic and microscopic analysis of bone tumors, the paradoxical predisposition to kind exuberant fracture callus that could be mistaken for osteosarcoma is of major significance. In addition to the clinical evaluation, laboratory and radiographic studies and sufficient biopsy material are wanted to make an accurate analysis. The necrotic bone in this situation results in reparative changes characterized by a highly mobile proliferation of fibroblastic tissue and reactive new bone formation. Unlike the reparative tissue adjacent to easy bone infarcts, atypical mesenchymal cells with pleomorphic and hyperchromatic nuclei are current. With the dose range utilized in fashionable radiotherapy (4000 to 7000 rads), the chance for sarcomatous transformation is low. A, Radiograph of resection specimen shows femoral head prosthesis and lytic space of proximal femur. B, Gross photograph of identical specimen reveals hemorrhagic damaging mass surrounding femoral head of metallic implant; hemorrhagic mass extends into delicate tissue (arrows). C and D, Malignant fibrous histiocytoma associated with metallic implant (same case as proven in A and B). The danger of developing sarcoma in bone due to genetic predisposition has not yet been estimated. In basic, familial syndromes which will predispose to cancer should be clinically suspected when (1) clusters of most cancers happen in a single family, no matter whether the tumors are the same or differing types that originate in the same or different organs; (2) cancer occurs in an uncommon age, usually in younger sufferers; and (3) multiple unbiased primary tumors have an result on a single particular person. The skeletal anomalies could be settled and focal or may be widespread, leading to main disfiguring deformities. Benign pores and skin adnexal lesions are probably the most frequent neoplasms seen on this situation.
Smallage (Lovage). Trecator SC.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96709

In the perineum, the corpora cavernosa diverge to type the crura, which attach to the inferior facet of the ischiopubic rami. The arterial provide of the penis is routed through the proper and left inner pudendal artery and branches of the internal iliac arteries. Each inner pudendal artery provides off a perineal department, a bulbar artery, and a small urethral artery before continuing as the artery of the penis. The artery of the penis enters the bottom of the penis and branches into the deep penile or cavernosal artery and the dorsal artery of the penis. The cavernosal artery lies close to the middle of each corporal physique and is the first supply of blood move to erectile tissue. The lacunar areas are drained by small venules, which coalesce to kind larger emissary veins. These emissary veins pierce the tunica albuginea at oblique angles and anastomose to kind the circumflex veins, which ultimately drain into the deep dorsal vein of the penis. The venous drainage from the proximal crura is distinct from that of the relaxation of the penis; its course is primarily through the cavernosal and crural veins. Sinusoidal distention in the erect penis is maintained by a venoocclusive mechanism, which consists of the mechanical compression of emissary veins towards the unyielding tunica albuginea and may happen solely when the sinusoids are expanded utterly. Peripheral innervation of the penis consists of sympathetic nerves originating from T11 to L2 and parasympathetic and somatic nerves originating from S2 to S4. Cholinergic autonomic nerves and nonadrenergic or noncholinergic autonomic nerves cause smoothmuscle leisure. Mechanism of Erection and Detumescence Erection begins with the relaxation of lacunar and arterial clean muscle. Relaxation of cavernosal and helicine smooth muscle impacts an increase in arterial diameter and blood circulate to the lacunae. Relaxation of the graceful muscle that surrounds the lacunar spaces of the corpora cavernosa facilitates arterial influx via a decrease in peripheral vascular resistance. In addition, dilatation of the lacunae causes passive compression of the emissary veins in opposition to the comparatively noncompliant tunica albuginea, facilitating engorgement of the penis with blood. Sympathetic neural activity causes a rise in smooth-muscle tone of the helicine arteries and the lacunae. A, An axial T2 surface-coil image by way of the prostate gland shows a focal area of hypointensity on the left aspect of the peripheral zone (arrow). B, Corresponding T1-weighted picture, obtained during dynamic contrast enhancement exhibits early, irregular enhancement in the same region (arrow) as compared with the background regular gland. The tumor is related to early enhancement and early washout because of the increased quantity and permeability of tumor vascularity. A, A T2-weighted coronal image via the penis and scrotum reveals the paired dorsal corpora cavernosa (asterisks) surrounded by the hypointense tunica albuginea (arrows). B, Axial T2-weighted picture by way of the bottom of the penis with the paired corpora cavernosa seen longitudinally (asterisks), surrounded by the hypointense tunica albuginea. The corpus spongiosum, seen in cross part on this picture (arrowhead), terminates posteriorly because the bulb of the penis (arrows). B, An axial image slightly decrease, by way of the base of the penis, exhibits the inflatable penile cylinders (arrows) in the corpora cavernosa. C, An axial picture through the higher scrotum shows the highest of the valve mechanism on the right (arrow). Knowledge of the presence and kind of prosthetic system could forestall imaging and interventional embarrassment, similar to percutaneous drainage of a reservoir mistakenly identified as a pelvic fluid assortment. These drugs all perform equally, by blocking the exercise of phosphodiesterase sort 5. The medications serve to improve the impact of nitric oxide, which is often released throughout sexual stimulation. Use of imaging exams for staging newly diagnosed prostate cancer: developments from the Capsure database. Hypoechoic lesions of the prostate: medical relevance of tumor measurement, digital rectal examination, and prostatespecific antigen.
Leiomyosarcoma of bone also has been described as one of many rare complications of radiation remedy. A, Well demarcated lucent lesion with a trabeculated look and sclerotic margins involving the calcaneus of a 9-year-old boy. B, Intramedullary lucency with focal sclerosis and trabeculation involving the proximal phalanx of the middle finger in a 33-year-old woman. C, Lucent lesion with trabeculation and focal penetration of the cortex within the patella of a 29-year-old man. D, Sagittal magnetic resonance picture of the lesion proven in C depicting an intramedullary low signal depth mass within the patella. A and B, Anteroposterior and lateral views of the lesion involving distal humerus of a 10-year-old woman. C and D, T1- and T2-weighted axial magnetic resonance pictures displaying an expansile intramedullary lesion with thin however intact overlying cortex. Inset, Higher magnification of a nest of tumor cells with predominantly granular cytoplasm and focal clear cell options. These tumors are often multifocal and primarily involve the gastrointestinal tract, liver, and lung. Radiographic Imaging Radiographic options are nonspecific but are according to those of a malignant lesion. On plain radiographs, leiomyosarcoma presents as a harmful lytic lesion with cortical disruption and extension into delicate tissue. The tumor is usually nicely demarcated from the encircling bone or delicate tissue, and this function could be deceptive. In fact, microscopic margins present an infiltrative irregular pattern of involvement of adjoining structures. The stroma can have variable amounts of collagen, and the lesion could also be focally or diffusely heavily hyalinized. Occasionally, aggregates of multinucleated, osteoclast-like large cells could be so prominent as to obscure the spindle Text continued on p. A and B, Anteroposterior and lateral radiographs of distal femoral shaft of a 33-year-old man present lytic lesion with permeative destruction at margins and focal cortical erosion. A, Lateral radiograph reveals destructive lesion of proximal end of fibula in a 32-year-old man. This well-differentiated leiomyosarcoma is sharply demarcated and expansile, without periosteal reaction. D, Specimen radiograph demonstrates sharp circumscription of proximal fibular leiomyosarcoma. A and B, Anteroposterior and lateral radiographs of knee of a 51-year-old man show ill-defined lesion in proximal tibial metaphysis. Tumor has produced permeative pattern of bone destruction with no discernible periosteal response. A and B, Anteroposterior and lateral radiographs of ankle region of a 68-year-old woman present ill-defined damaging lesion of distal tibial shaft with massive mass in posterior delicate tissue. C, Computed tomogram shows intraosseous tibial tumor and enormous mass in posterior delicate tissue. D, Coronal minimize by way of distal tibia and ankle (amputation specimen) reveals gray-white, firm intraosseous tumor filling marrow cavity and eroding tibial cortex. A, Plain radiographic image exhibiting intramedullary diaphyseal lesion of the humerus with lytic harmful growth pattern and pathologic fracture in a 40-year-old lady who had a son with bilateral retinoblastoma. B and C, T1- and T2-weighted magnetic resonance pictures of the lesion proven in A showing a destructive intramedullary lesion with associated pathologic fracture. A, Sagittally sectioned tibial resection specimen with destructive gray to white mass involving distal area. Note large amount of cortical destruction, with circumferential extension into gentle tissue. B, Proximal tibial resection specimen exhibits damaging grey to white intramedullary mass. C, Coronal section of proximal tibial resection shows intramedullary mass with central necrosis inside fleshy site. Ultrastructurally these tumors are composed of spindle cells containing a centrally placed elongated nucleus with blunt ends. Although the nuclei of easy muscle cells are oval underneath the light microscope, ultrastructurally they might present multiple infoldings of the nuclear envelope.

A, A uniform sheetlike proliferation of notochordal cells filling up the intratrabecular areas. B, Focus on thicken bone trabeculae with scallop borders forming interconnecting community, signifying bone remodeling regularly seen in giant notochord relaxation. C, Solid sheetlike proliferation of notochordal cells with clear cytoplasm resembling fat. D, Pushing border sharply delimiting the notochord cells from the adjoining, uninvolved fatty marrow. Inset, Higher magnification of a physaliphorous cell sometimes present in notochord rests. A and B, Whole-mount photomicrographs of coccyx displaying a large notochord relaxation and a focus of chordoma (arrows). Note that focus of chordoma shows distinctive lobular architecture with myxoid stromal change and displays damaging progress pattern, breaking via the cortex into the periosteal fibroadipose tissue. B, Higher magnifications of A and B displaying a focus of chordoma with lobular architecture and myxoid stroma. C, Higher magnification of A displaying chordoma cells infiltrating periosteal stromal tissue. D, Higher magnification of B showing chordoma cells infiltrating periosteal stromal tissue. Inset, Microscopic features of large notochordal cells with solid sheetlike proliferation of bland looking notochordal cells with clear cytoplasm resembling fats. A, Gadolinium-diethylenetriamine pentaacetic acid enhanced T1-weighted magnetic resonance picture. Tumor protrudes anteriorly from the coccyx and consists of intermediate density lobules separated by skinny contrasted septations. Two intraosseous lesions of low density similar to notochord rests are recognized (arrows). B, Gross photograph of the resected specimen discloses a lobulated tumor composed of gelatinous tissue with foci of hemorrhage. Two intraosseous lesions corresponding to multifocal big notochord rests are also present (arrows). [newline]C, Microscopic options of an enormous notochord rest exhibiting sheetlike strong proliferation of cells with vacuolated cytoplasm. D, Microscopic options of notochordal rest (upper part) and chordoma (lower part). Note myxoid appearance of stroma in chordoma and bland wanting strong proliferation of benign notochord cells. It should be talked about that a small number of chordomas happen in the course of the first and second a long time of life. Chordoma almost solely involves the axial skeleton, which is consistent with its notochordal origin. Extremely uncommon examples of multicentric chordoma involving several anatomic sites have been reported. Sphenooccipital chordomas produce symptoms associated to compression or destruction of various adjoining buildings, such because the optic nerves or pituitary gland. Age-adjusted incidence charges and age-specific frequency, all races, each sexes, 650 cases. A, Anteroposterior radiograph of sacrum exhibits expansive lytic lesion of physique of sacrum. B, Lateral radiograph of lumbar backbone exhibits uncommon sclerotic look of physique of L4 produced by vertebral chordoma. Lateral view of cranium reveals destruction of sella turcica region of base produced by sphenooccipital chordoma (arrow). T2-weighted magnetic resonance picture of chordoma at base of cranium exhibits high sign depth mass in region of sphenoid bone (arrows). Vertebral chordomas produce lytic lesions which will contain two or more adjoining vertebral our bodies. Computed tomography and magnetic resonance imaging are indispensable in evaluating both the extent of the lesion and the involvement of adjoining structures. They are regularly myxoid or gelatinous in look and might mimic chondrosarcoma or mucinous adenocarcinoma. Despite good demarcation, the tumor normally extends beyond its grossly recognizable borders.

On longitudinal sections, a nerve and its constructions cross through the lesion, and this mass is delineated by a perineurium. The overall structure of neurofibroma is incessantly described as being patternless as opposed to neurilemmoma, which consists of bundles of palisaded cells. Various inflammatory cells, similar to mast cells, lymphocytes, and xanthomatous histiocytes, are frequently present. Schwann cells are usually current in neurofibromas and predominate focally in some tumors. Neurofibromas might contain heterologous elements, such as glandular epithelial constructions of varied sorts, and even foci resembling rhabdomyoma. Myelinated axons may be demonstrated by neurofilament protein immunostaining or Luxol quick blue myelin staining. Immunohistochemically, neurofibroma cells are positive for vimentin and show variable focal positivity for S-100 protein. Cells optimistic for S-100 protein may in fact characterize scattered particular person Schwann cells. The identification of plexiform neurofibroma for the prognosis of neurofibromatosis must be confirmed by gross examination. Fully developed plexiform neurofibromas are massive lesions that contain one anatomic region or a complete extremity (elephantiasis neuromatosa). Nuclear pleomorphism and atypia with hyperchromatism are sometimes seen in neurofibroma, particularly in bigger, older lesions. In plexiform lesions, individual nodules are delineated by perineural cells which are constructive for epithelial membrane antigen. Enzinger and Weiss128 estimate that no much less than 10% of sufferers with diffuse neurofibroma have neurofibromatosis. On the other hand, massive diffuse lesions of this kind involving the pinnacle region in youngsters are virtually at all times related to neurofibromatosis. In his review, Stout200 states that roughly 18% of sufferers with neurilemmoma even have neurofibromatosis type 1. The highly significant association of schwannoma and neurofibromatosis can be confirmed by observations made by Enzinger and Weiss. A more modern view is primarily associated to the clear separation of neurofibromatosis kind 2 and three with firm establishment of the concept that neurofibromatosis type three, additionally referred to as schwannomatosis, is clinically distinct from neurofibromatosis kind 2. The massive inhabitants primarily based studies of schwannomas point out that almost 90% of schwannomas are solitary sporadic tumors and only 3% are associated with neurofibromatosis sort 2. A distinct minority, roughly 2% of schwannomas, are associated with neurofibromatosis sort 3. This last association is seen in patients with and with out neurofibromatosis kind 2. Malignant peripheral nerve sheath tumor represents the most severe and often deadly complication of neurofibromatosis. This term encompasses beforehand used designations similar to malignant schwannoma, neurofibrosarcoma, and neurogenic sarcoma. These phrases imply that the tumors recapitulate or originate from specific cells of the nerve sheath, corresponding to Schwann cells, perineural fibroblasts, or fibroblasts. Phenotypic variation (divergent differentiation) is regularly seen in these tumors, which might exhibit differentiation towards nonneural parts similar to rhabdomyoblasts, smooth muscle, adipose tissues, cartilage, bone, and epithelial glandlike constructions. B, Gross photograph of neurofibroma resected en toto showing distinguished myxoid content material as revealed by transillumination. D, Intermediate energy photomicrograph exhibiting bland fusiform cells in myxoid background (�200). A, Low power photomicrograph of neurofibroma exhibiting outstanding myxoid content material (�100). B, Intermediate energy photomicrograph displaying concentration of axons within the middle of neurofibroma, similar case as A (�200).

However, this strategy is generally discouraged because of the risk of incomplete removal of the nidus and recurrence of symptoms. Recurrence might occasionally happen a few years after removal of the primary lesion. According to Mayo Clinic data, this occurs in almost 20% of sufferers with osteoid osteomas that have a radiologically documented nidus. The nidus tissue may be found in a relatively high proportion of sufferers who undergo further surgery. Although en bloc excision is the preferred treatment, in some instances a lesion may be inaccessible to the surgeon. In such instances, its full removal might cause more disability than that associated with the original disease. Some of those patients could be managed with prolonged therapy with nonsteroidal anti-inflammatory medicine. As reported by Kneisl and Simon,65 prolonged anti-inflammatory remedy (30-40 months) can induce permanent aid of signs, and regression of the nidus may be seen on radiographs. Ablation of the nidus with a percutaneously positioned radiofrequency electrode that produces thermocoagulation has turn into extensively accepted. Reported success rates for remedy by thermocoagulation with radiofrequency electrodes have ranged between 80% and 90% (no want for added procedures or medicines for two years). A, Radiograph of hip of an 8-year-old woman shows nidus with average bone sclerosis surrounding lesion. B, Computed tomogram at this degree shows nidus more clearly with cortical thickening and medullary sclerosis. C, Bone scan exhibits giant zone of elevated uptake similar to nidus and perilesional sclerosis. D, Radiograph of a 17-yearold athletic boy with proximal leg pain and localized cortical thickening that at first was thought to symbolize a stress fracture. E, Computed tomogram of tibia shown in D reveals punctate lucency diagnostic for intracortical osteoid osteoma. A, Osteoid osteoma of the proximal humerus with distinguished diffuse sclerosis and periosteal response deforming bone contour. B, Anteroposterior radiograph showing diffuse sclerosis and length discrepancy of the left femur. Note sclerosing lesion of left tibial diaphysis and pronounced size discrepancy. F, Clinical photograph of the same patient 1 12 months later, displaying discrepancy in limb size and protracted bowing deformity of concerned tibia. Osteoid osteomas of small peripheral bones are nearly all the time associated with a definite swelling of soft tissue and synovitis of the adjacent joints. Therefore on this location, long delays in arriving on the right analysis could occur as a end result of the tumor could incessantly mimic an inflammatory course of. Osteoid Osteoma of Vertebral Column Approximately 10% to 15% of osteoid osteomas happen within the vertebral column. Spinal lesions are tough to detect on plain radiographs and are identified to be liable for unexplained backache and painful scoliosis. It is beneficial that an underlying osteoid osteoma be ruled out in nearly all instances of unexplained again ache and painful scoliosis that occur in kids and young adults. At finest, the radiographs may present an area of sclerosis, a thickened and distorted sclerotic transverse course of, or a deformed sclerotic pedicle with indistinct borders. Magnetic resonance imaging additionally may facilitate the identification of an inconspicuous nidus. High sign in T2weighted photographs of nidus tissue correlates properly with its elevated vascularity. Within the physique the nidus is usually located eccentrically near the base of a transverse process. Juxtaarticular Osteoid Osteoma Osteoid osteomas situated throughout the articular capsule are uncommon and troublesome to detect. They are typically associated with nonspecific signs just like other widespread joint disorders. Pain is usually much less intense, and its response to nonsteroidal antiinflammatory medication is much less dramatic.
Murak, 44 years: These modalities, in addition to ultrasonography, can additionally be used for restaging and oncologic surveillance. A, Blastoid plasma cells with excessive nuclear cytoplasmic ratio and prominent nucleoli. It should be talked about that a small variety of chordomas happen in the course of the first and second decades of life.
Milok, 63 years: Extension of cellular cartilaginous tissue into the adjacent gentle tissue and a clinical historical past of a newly discovered mass and associated ache are probably the most constant signals of malignant transformation. In two of those instances treated by simple curettage, the tumor recurred inside 3 to 4 months and displayed radiographic features of a destructive progress pattern, which prompted extra aggressive resections with prosthetic replacement. D, Central portion of lesion displays features of fats necrosis and dystrophic calcification.
Arakos, 23 years: Neural lesions regularly exert secondary effects on bones, eroding them from the floor and deforming and increasing neural canals and foramina because of the pressure of expansile development, as in the case of neurofibromatosis. Trabecular osteoid surface; the percent of cancellous bone surface coated by osteoid 2. Gross Findings Tumoral calcinosis consists of an encapsulated firm mass of a number of calcified nodules that focally coalesce into bigger, lobulated masses.
Kayor, 60 years: Each part of each vascular and lymphatic techniques has its personal expression signature. At least a few of these tumors have microscopic options just like these of mesenchymal chondrosarcoma. The use of applicable markers and the identification of phenotypic features of Langerhans cells help to keep away from this error.
Vasco, 29 years: The 5- and 10-year survival rates for major bone lymphoma are 65% and 53%, compared with 53% and 43% for patients with systemic lymphoma in addition to bone masses. Frequent use of computerized imaging techniques in diagnostic workup in bone lesion in trendy apply has dramatically lowered the incidence of such lesions. Nonspecific staining because of leakage of the antigen can be suspected if diffuse extracellular and cellular staining is observed.
Xardas, 40 years: Meanwhile, renal-sparing surgical procedure has grown in popularity and the methods have been refined. E, Lateral radiograph showing a large broad-based osteochondroma arising from the posterior aspect of the proximal tibia. It is our impression that no less than some of the cases beforehand reported as major liposarcomas of bone would be presently categorized as malignant fibrous histiocytomas.
Ugrasal, 35 years: Incidence and Location Enchondroma is a incessantly occurring benign tumor that, in different collection, accounts for 12% to 24% of benign bone tumors and 3% to 10% of all bone tumors. The replica of signs, such as flank pain, helps the presence of urodynamically significant obstruction. Areas with less differentiated spindle cells exhibit prominent nuclear atypia and brisk mitotic activity.
References

Desarrolló: Grupo Guadalupe S.R.L.