
Luke Hermann, MD
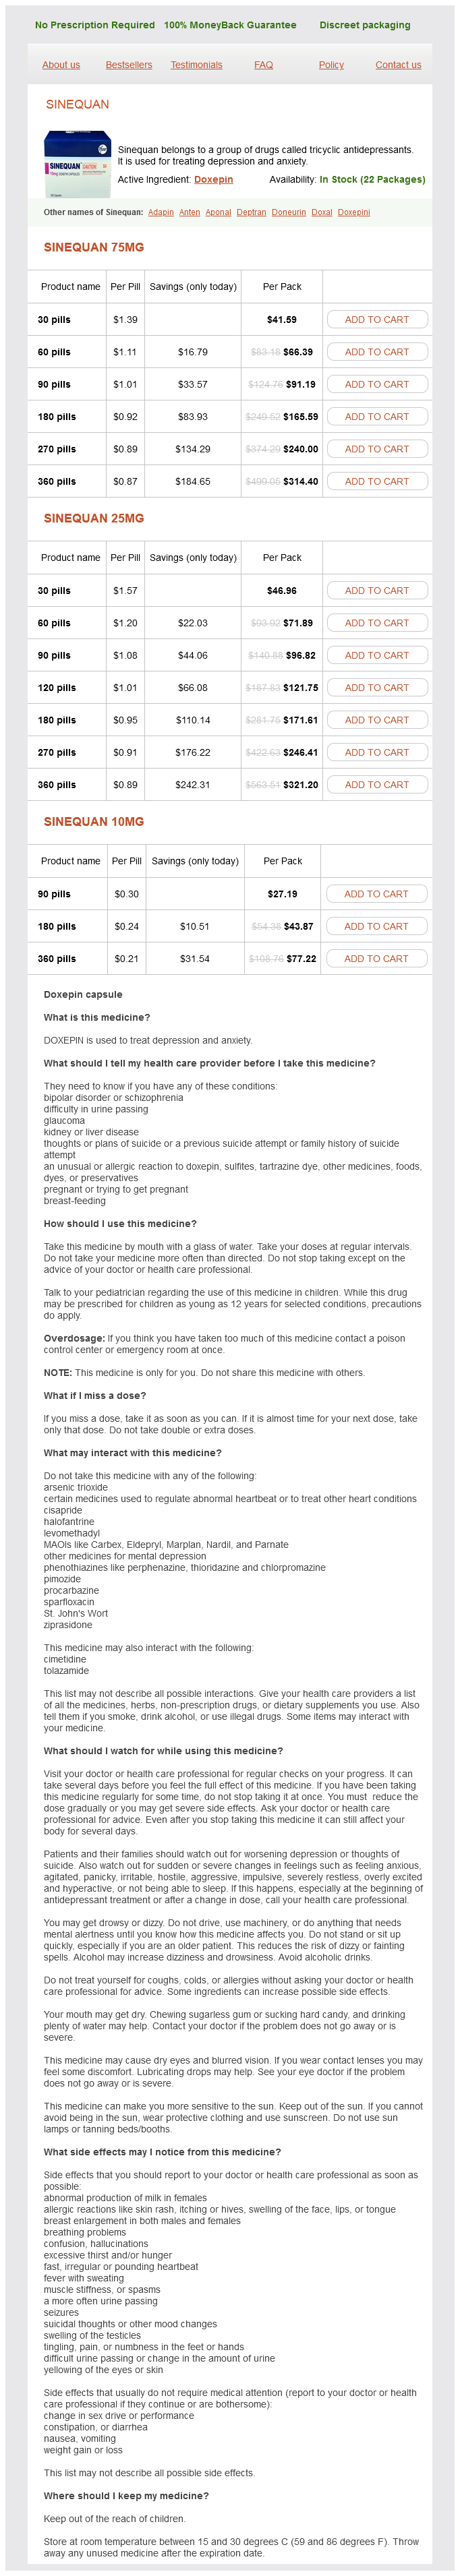
Doxepin dosages: 75 mg, 25 mg, 10 mg
Doxepin packs: 30 pills, 60 pills, 90 pills, 180 pills, 270 pills, 360 pills, 120 pills

These are (a) the descending genicular artery, a department of the femoral artery (on the superomedial aspect), (b) the descending department of the lateral femoral circumflex artery (on the superolateral aspect) and (c) anterior tibial recurrent artery, a branch of the anterior tibial artery (on the inferolateral aspect). Then it comes to lie on the popliteus muscle, under cowl of gastrocnemius and plantaris and subsequently enters the back of leg. It arises from the anterior divisions of L4,5,S1,2 and 3 and runs as part of the sciatic trunk in the gluteal area and proximal thigh. At the superior angle of popliteal fossa, where the sciatic trunk divides into its constituent elements, the tibial nerve separates off and runs downwards to the leg. It continues additional downwards and at the level of the ankle, takes a medial turn to go under cover of the flexor retinaculum, the place it divides into its two terminal branches, specifically, the medial and the lateral plantar nerves. The arteries collaborating in these anastomoses are (from above downwards): the superior and inferior gluteal arteries the medial and lateral circumflex femoral arteries Perforating branches of the profunda femoris artery Muscular branches of the popliteal artery Through these anastomoses, links are established between the interior iliac, femoral and popliteal arteries. Clean the connective tissue sheath enclosing the vessels and nip open if needed. With utmost care, retract the vessels to see the various genicular branches arising out of the popliteal artery. If sufficient retraction is feasible, nerve to politeus may be seen; t runs on the posterior floor of the muscle and turns around its distal border. The two medial arteries and the 2 lateral arteries are joined by vertical anastomoses Thus, a quadrilateral community is formed and this community liesmore on the anterior aspect of the knee joint this quadrilateral network is joined by the descending genicular department of the femoral artery superomedially and the descending department of the lateral circumflex femoral artery superolaterally Inferiorly, the recurrent department of the anterior tibial artery and the circumflex fibular branch of the posterior tibial artery be part of the community. The popliteal lymph nodes could be described in two teams; (1) the superficial group and (2) the deep group. The superficial popliteal lymph nodes are small and lie within the superficial fascia. One of them is somewhat massive, lies on the point where the small saphenous vein pierces the deep fascia and receives lymph from the lymphatics that accompany the vein. The deep popliteal lymph nodes lie throughout the fats of the fossa and encompass the popliteal artery and vein; they obtain lymph from the lymphatics which accompany the deep veins and from the knee joint capsule the lymphatics from the popliteal lymph nodes follow the femoral vessels and drain into the inguinal lymph nodes. Set 1: Articular branches to the knee: Two slender branches, certainly one of which pierces the oblique popliteal ligament and the other accompanies the inferomedial genicular artery; each provide the structures of the knee joint. Set 2: Muscular branches: Five branches; the branches to the 2 heads of gastrocnemius and the plantaris enter the involved muscular tissues at those features where they form the inferior borders of the popliteal fossa; the nerve to soleus enters the muscle on its superficial surface; the remaining nerve of this set, particularly, the nerve to popliteus deserves special description. The nerve runs down on the posterior floor of the popliteus muscle, turns round its distal border and then supplies the muscle on its anterior floor. Set three: Cutaneous branch: this is the sural nerve; from the popliteal fossa, the nerve runs between the two heads of gastrocnemius and then lies on the tendocalcaneus. It then runs downwards and reaches the foot by winding across the again of the lateral malleolus, together with the small saphenous vein the sural nerve provides cutaneous branches to the lateral side and again of the lower third of the leg, the ankle, the heel (the lateral calcaneal branches) and the lateral border of the foot and the little toe, articular branches to ankle and tarsal joints On the dorsum of the foot, the sural nerve communicates with the branches of the superficial peroneal nerve. Set 1: Cutaneous branches: the 2 cutaneous branches on this category are the lateral cutaneous nerve of the calf and the peroneal communicating nerve. It arises in widespread with the peroneal communicating nerve within the popliteal fossa, pierces the deep fascia over the lateral head of gastrocnemius and provides the skin and fascia of the lateral part of the back of leg within the upper two thirds. Set 2: Recurrent branch: It arises instantly proximal to the terminal division of the widespread peroneal and passes forward under cowl of the peroneus longus. It then runs by way of the extensor digitorum longus and reaches the anterior compartment of leg beneath the lateral condyle of tibia. At this degree, it divides into branches which supply the tibialis anterior muscle, the superior tibiofibular joint and the knee joint. They arise instantly below the top of fibula and under cowl of peroneus longus, run ahead and subsequently diverge from one another. Following the tendon of this muscle, the nerve runs obliquely to he lateral a half of the popliteal fossa and passes over the lateral head of gastrocnemius to reach the back of the pinnacle of fibula. Also due to the same purpose, abscesses or tumours within the fossa are inclined to unfold superiorly or inferiorly Because the popliteal artery is carefully related to the femur and knee joint capsule, fractures of the distal femur and dislocations of knee can cause rupture of the artery. Injuries to the popliteal artery and vein could cause an arterio-venous shunt leading to haemorrhage o loss of blood provide to the leg. A popliteal aneurysm (which is an irregular dilatation of the artery) can cause ache and swelling within the popliteal fossa. Such an aneurysm can stretch the tibial nerve or intervene with the blood provide to the nerve. Pain from such a nerve compression is often felt as a referred ache on the skin of the medial aspect of leg and foot.
The starting dosage for acute mania in adults is 250 mg 3 occasions a day or 500 mg as soon as day by day at bedtime. Like valproate, carbamazepine seems much less efficient at treatment and prevention of depression. For treatment of acute manic episodes, the dosage ought to be low initially (200 mg twice daily) after which gradually elevated. Neurologic side effects (visual disturbances, ataxia, vertigo, unsteadiness, headache) are widespread early in therapy, but generally resolve despite continued drug use. Hematologic effects (leukopenia, anemia, thrombocytopenia, aplastic anemia) are comparatively unusual, but may be extreme. Accordingly, full blood counts, including platelets, must be obtained at baseline and periodically thereafter. Carbamazepine induces cytochrome P450 isoenzymes, and might thereby accelerate its own metabolism and the metabolism of different medication (eg, oral contraceptives, warfarin, valproate, tricyclic antidepressants). To keep efficacy, dosages of carbamazepine and these different medication ought to be increased as wanted. Drug merchandise containing carbamazepine are available beneath four commerce names: Carbatrol, Equetro, Epitol, and Tegretol. Lamotrigine may be used alone or together with different mood-stabilizing agents. Side effects embrace headache, dizziness, double imaginative and prescient, and, not often, life-threatening rashes (Stevens-Johnson syndrome, poisonous epidermal necrolysis). To decrease the danger of significant rash, dosage must be low initially (25 to 50 mg/day) after which progressively increased. The goal maintenance dosage is 200 mg/day (if used alone), 100 mg/day (if mixed with valproate), or four hundred mg/day (if mixed with carbamazepine or some other inducer of cytochrome P450). As mentioned in Chapter 31, the antipsychotic drugs fall into two main groups: first-generation antipsychotics (conventional antipsychotics) and second-generation antipsychotics (atypical antipsychotics). Compared with the standard agents, the atypical *As discussed in Chapter 24, divalproex sodium [Depakote] is a combination of valproic acid [Depakene, Depacon, Stavzor] and its sodium salt [Depakene]. Depressive Episodes: Start with 6 mg olanzapine/25 mg fluoxetine once every day in the night. The effective vary for antidepressant results is olanzapine 6�12 mg and fluoxetine 25�50 mg. Acute Mania (with regular liver function): Give in two divided doses as follows: one hundred mg on day 1, 200 mg on day 2, 300 mg on day 3, and 400 mg on day 4. Acute Mania (with liver impairment): Give 25 mg on day 1, then improve by 25�50 mg/day till signs are managed or unwanted effects are intolerable, whichever comes first. Depressive Episodes: Give once-daily doses at bedtime as follows: 50 mg on day 1, 100 mg on day 2, 200 mg on day three, and 300 mg on day four; if needed, increase to four hundred mg on day 5, and 600 mg on day 8. Acute Mania: Start with 2�3 mg as soon as daily; increase to a most of 6 mg as soon as every day; if wanted. Based on tolerability and efficacy, adjust dosage within the range of 40�80 mg twice every day. Aripiprazole [Abilify] Olanzapine [Zyprexa] Olanzapine/fluoxetine [Symbyax] Quetiapine [Seroquel] Risperidone, short-acting [Risperdal] Risperidone, long-acting [Risperdal Consta] Ziprasidone [Geodon] agents carry a decrease risk of extrapyramidal unwanted effects, including tardive dyskinesia. Currently, only three atypical agents-aripiprazole, olanzapine, and ziprasidone-are accredited for long-term use to forestall recurrence of temper episodes. Antipsychotic medicine are used acutely to deal with manic episodes, and long run to assist stabilize temper. In patients with bipolar despair, using an antidepressant alone may induce mania-although the danger seems lower than previously believed. The trough level, measured 12 hours after the evening dose, must be lower than 1. Common unwanted aspect effects that occur at therapeutic lithium levels embody tremor, goiter, and polyuria. Lithium may be teratogenic, and hence should be avoided in the course of the first trimester of being pregnant. Also, except the benefits outweigh the risks, lithium should be averted through the second and third trimesters too. A discount in sodium ranges will cut back lithium excretion, causing lithium to accumulate-possibly to toxic levels.

When pregabalin is discontinued, dosage must be progressively tapered, over 1 week or longer. Interestingly, more than 80% of prescriptions are written for offlabel uses, including reduction of neuropathic ache (other than postherpetic neuralgia), prophylaxis of migraine, therapy of fibromyalgia, and aid of postmenopausal hot flashes. Gabapentin is quickly absorbed following oral dosing and reaches peak plasma levels in 2 to three hours. However, as the dosage gets larger, the percentage absorbed gets smaller as a end result of, at excessive doses, the intestinal transport system for uptake of the drug turns into saturated. The most typical unwanted side effects are somnolence, dizziness, ataxia, fatigue, nystagmus, and peripheral edema. Until further knowledge are available, producers advocate that gabapentin should solely be utilized by nursing girls if the benefits of breast-feeding outweigh the risks to the infant. For adults with epilepsy, treatment begins with a 300-mg dose at bedtime, adopted the next day by 600 mg (in two divided doses), and the subsequent day by 900 mg (in three divided doses). Thereafter, the dosage may be raised rapidly to upkeep levels, sometimes 1200 to 3600 mg/day in three divided doses. Pregabalin has only a few interactions with other medicine, but antagonistic results are widespread, especially dizziness and sleepiness. In distinction to most different antiseizure brokers, pregabalin is regulated beneath the Controlled Substances Act. Dosing is begun at 150 mg/day (50 mg 3 times a day) and could additionally be elevated in a week, as wanted and tolerated, to a upkeep level of 300 mg/day (100 mg three times a day). Dosages above 600 mg/day are unlikely to improve advantages but will improve the chance of adverse effects. Dosing should begin at one hundred fifty mg/day (75 mg twice daily or 50 mg three instances a day) and could also be increased, as wanted and tolerated, to the similar old upkeep degree of 300 mg/day (150 mg twice day by day or 100 mg 3 occasions a day). For patients with significant ache after 2 to four weeks at 300 mg/day, dosage may be increased to a maximum of 600 mg/day (300 mg twice day by day or 200 mg three occasions a day). Dosing is the same as for postherpetic neuralgia, with a most dosage of 600 mg/day. Dosing begins at 75 mg twice day by day, and may be elevated to 225 mg twice every day, if tolerated. Doses above this stage increase the risk of side effects, but offer no improve in benefits. In the United States, the drug is accredited for adjunctive therapy of (1) myoclonic seizures in adults and adolescents age 12 years and older, (2) partial-onset seizures in adults and youngsters age four years and older, and (3) primary generalized tonic-clonic seizures in adults and kids age 6 years and older. Unlabeled makes use of include migraine, bipolar dysfunction, and new-onset pediatric epilepsy. Following oral dosing, levetiracetam undergoes fast and complete absorption both within the presence and absence of meals. Neuropsychiatric symptoms (agitation, anxiousness, despair, psychosis, hallucinations, depersonalization) occur in lower than 1% of sufferers. Because levetiracetam is eliminated by the kidneys, dosage ought to be lowered in sufferers with significant renal impairment. Cognitive results (confusion, reminiscence difficulties, altered considering, lowered focus, problem discovering words) can occur, however the incidence is low at recommended dosages. The drug inhibits carbonic anhydrase, and thereby will increase renal excretion of bicarbonate, which causes plasma pH to fall. Mild to reasonable metabolic acidosis develops in 30% of grownup sufferers, however extreme acidosis is uncommon. Risk components include renal illness, extreme respiratory problems, diarrhea, and a ketogenic food regimen. Prolonged metabolic acidosis can lead to kidney stones, fractures, and development delay. Advise patients to inform the prescriber in the event that they experience hyperventilation and other signs (fatigue, anorexia). If metabolic acidosis is diagnosed, topiramate ought to be given in lowered dosage or discontinued.

Febrile seizures typically manifest as generalized tonic-clonic convulsions of short duration. In generalized seizures, focal seizure exercise is performed extensively throughout both hemispheres. As a rule, partial seizures and generalized seizures are treated with completely different drugs (Table 24�1). Partial Seizures Partial seizures fall into three groups: simple partial seizures, advanced partial seizures, and partial seizures that evolve into secondarily generalized seizures. These seizures manifest with discrete symptoms that are decided by the mind area involved. Hence, the affected person could expertise discrete motor signs (eg, twitching thumb), sensory symptoms (eg, native numbness; auditory, visual, or olfactory hallucinations), autonomic signs (eg, nausea, flushing, salivation, urinary incontinence), or psychoillusory signs (eg, feelings of unreality, concern, or depression). These seizures are characterized by impaired consciousness and lack of responsiveness. This state is adopted by a interval of automatism, during which the patient performs repetitive, purposeless movements, similar to lip smacking or hand wringing. Mixed Seizures: Lennox-Gastaut Syndrome Lennox-Gastaut syndrome is a severe type of epilepsy that normally develops in the course of the preschool years. The syndrome is characterised by developmental delay and a combination of partial and generalized seizures. Seizure varieties include partial, atonic, tonic, generalized tonic-clonic, and atypical absence. Neuronal motion potentials are propagated by influx of sodium via sodium channels, that are gated pores within the cell membrane that management sodium entry. Immediately following sodium entry, the channel goes into an inactivated state, during which further sodium entry is prevented. Under regular circumstances, the inactive channel in a brief time returns to the activated state, thereby permitting extra sodium entry and propagation of another motion potential. By delaying return to the active state, these drugs decrease the ability of neurons to fireplace at high frequency. In axon terminals, inflow of calcium through voltage-gated calcium channels promotes transmitter launch. During an motion potential, influx of sodium causes neurons to depolarize, after which efflux of potassium causes neurons to repolarize. Therefore, we must balance the will for complete seizure control in opposition to the acceptability of unwanted facet effects. Three options exist: neurosurgery, vagus nerve stimulation, and the ketogenic food regimen. Of the three, neurosurgery has the most effective success price, but vagus nerve stimulation is used most widely. Phenytoin, for instance, is beneficial for treating tonic-clonic and partial seizures however not absence seizures. Conversely, ethosuximide is lively in opposition to absence seizures however not towards tonic-clonic or partial seizures. Only one drug-valproic acid-appears efficient against virtually all forms of epilepsy. Making a analysis requires bodily, neurologic, and laboratory evaluations together with a thorough historical past. The historical past should determine the age at which seizures started, the frequency and period of seizure events, precipitating components, and occasions when seizures occur. Physical and neurologic evaluations may reveal indicators of head damage or other problems that would underlie seizure exercise, although in plenty of patients the physical and neurologic evaluations could additionally be regular. Other diagnostic exams which could be employed include computed tomography, positron emission tomography, and magnetic resonance imaging. No drug must be considered ineffective till it has been tested in sufficiently high dosages and for an inexpensive time. Knowledge of plasma drug ranges is normally a valuable tool for establishing dosage and evaluating the effectiveness of a specific drug.

Minimizing Adverse Interactions tamines, glucocorticoids) or withdrawal of fluoxetine. Inform patients in regards to the danger of rash and instruct them to notify the prescriber if one develops. The threat of bleeding with warfarin is compounded by a pharmacokinetic interplay with fluoxetine, which can displace warfarin from binding websites on plasma proteins, causing levels of free warfarin to rise. Preadministration Assessment Therapeutic Goal Alleviation of signs of main melancholy. Doxepin is contraindicated for sufferers with glaucoma or a tendency to urinary retention. If hypomania develops, the affected person have to be evaluated to decide if elation is drug induced or indicates bipolar disorder. Warn patients against using alcohol and all anticholinergic drugs (eg, scopolamine, antihistamines, phenothiazines). Once an effective dosage has been established, the entire every day dose can often be taken at bedtime. If blood strain is low or pulse price is excessive, withhold medicine and inform the prescriber. Inform patients about possible anticholinergic results (dry mouth, blurred vision, photophobia, urinary hesitancy, constipation, tachycardia), and advise them to notify the prescriber if these are troublesome. Inform patients about symptoms of hypotension (dizziness, lightheadedness), and advise them to sit or lie down if these happen. Inform sufferers that hypotension may be minimized by shifting slowly when assuming an erect posture. Preadministration Assessment Therapeutic Goal Alleviation of signs of main despair, especially atypical depression. Advise patients to keep away from hazardous actions (eg, driving, operating harmful machinery) if sedation is important. Warn sufferers not to discontinue treatment once temper has improved, since doing so might end in relapse. Instruct patients to apply the Emsam patch to intact, dry pores and skin of the higher torso, upper thigh, or outer floor of the upper arm as quickly as every 24 hours. Inform patients about signs of hypertensive crisis- severe headache, tachycardia, hypertension, nausea, vomiting, confusion, and profuse sweating-and instruct them to search immediate medical attention if these develop. Take these measurements whereas the affected person is mendacity down and once more after the affected person has been sitting or standing for 1 to 2 minutes. Application-site rash is frequent with transdermal selegiline, and may be managed with a topical glucocorticoid. Inform patients about signs of hypotension (dizziness, lightheadedness), and advise them to sit or lie down if these happen. Manic individuals show overactivity at work and at play and have a lowered want for sleep. Extreme self-confidence, grandiose ideas, and delusions of self-importance are common. Manic individuals often take pleasure in high-risk actions (eg, questionable enterprise offers, reckless driving, gambling, sexual indiscretions), giving no forethought to the consequences. In severe instances, symptoms might resemble those of paranoid schizophrenia (hallucinations, delusions, bizarre behavior). Associated symptoms include disruption of sleeping and eating patterns; problem concentrating; feelings of guilt, worthlessness, and helplessness; and thoughts of demise and suicide. In a real combined episode, sufferers expertise symptoms of mania and despair concurrently. Patients could additionally be agitated and irritable (as in mania), but may really feel nugatory and depressed. The mixture of excessive energy and despair places them at important danger of suicide. The mainstays of therapy are lithium and divalproex sodium (valproate), drugs that can stabilize mood. Many sufferers also receive an antipsychotic agent, and a few may require an antidepressant.

Bitter Herb (Centaury). Doxepin.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96411
The medial facet of the bone has a projection that seems to hold inferiorly and known as the tuberosity. In its regular position, its anterior finish is at a barely greater level than its posterior finish, thus contributing to the longitudinal arch of the foot. The superior or dorsal floor bears three aspects, particularly the anterior, center and posterior sides which articulate with corresponding facets on the inferior floor of talus. It is separated from the posterior facet by a deep groove known as the sulcus calcanei. The inferior or plantar floor of the calcaneus exhibits a prominence in its posterior half known as the calcaneal tuberosity (also called the tuber calcanei). The medial and lateral elements of tuberosity extend additional forwards than its central half and are referred to as the medial and lateral processes (sometimes, the medial and lateral tubercles) respectively of the tuberosity. The superior surface is rough and flat; the inferior surface has a prominent ridge throughout itself and a groove adjoining to the ridge. The medial surface has an articular facet for the lateral cuneiform and the lateral surface is rough with a tuberosity on its posterior facet and a groove immediately anterior to the tuberosity. It articulates proximally with the navicular bone, distally with the primary metatarsal bone, and laterally with the intermediate cuneiform and second metatarsal bones. The three bones articulate with the navicular posteriorly and the first three metatarsals anteriorly. The shortness of the intermediate cuneiform makes the bottom of the second metatarsal project again between the medial and lateral cuneiforms. The bone articulates proximally with the pinnacle of the talus, distally with the three cuneiform bones, and laterally with the cuboid. The posterior surface (also referred to as the proximal surface) is deeply concave and has a single articular side to fit the convexity of the head of talus. The superior floor (also known as the dorsal surface) is tough, has several vascular foramina and merges imperceptibly with the medial and lateral elements, forming a curved surface that conforms to the curve of the dorsum of foot. The inferior floor (also called the plantar surface) can additionally be rough and slopes up anteriorly to attain the proximal surface. The medial part of the bone has a projection known as tuberosity, which may be felt about 3�4 cm under and in front of the medial malleolus. The cuboid bone articulates proximally with the calcaneus; distally with the fourth and fifth metatarsal bones, and medially with the navicular and lateral cuneiform bones. It has six surfaces, particularly the anterior, posterior, superior, inferior, medial and lateral surfaces. The nearly flat anterior surface articulates with the bases of fourth and fifth metatarsal bones by two articular sides that are separated by a ridge. The posterior surface is also articular however has a single massive concavoconvex articular side for articulation with the calcaneus. The superior surface is tough and slopes down laterally to conform to the shape of the dorsum of foot. The lateral finish of the ridge types a projection referred to as tuberosity; the ridge passes forwards and medially throughout the surface. Immediately anterior to the ridge is a groove which lodges the tendon of peroneus longus in life. The medial floor faces upwards and medially; as this surface articulates with lateral cuneiform, the 2 bones collectively assist the transverse arch of the foot. It articulates proximally with the navicular bone, distally with the second metatarsal bone medially with the medial cuneiform bone, and laterally with the lateral cuneiform bone. The medial surface bears an L-shaped aspect, while the lateral aspect bears a vertical aspect. The proximal and distal surfaces could be distinguished by the reality that the whole distal surface is covered by a triangular aspect, however the proximal surface is roofed by a smaller facet. The posterior surface has an oval concave side which is confined to the dorsal two-thirds of the surface for articulation with the navicular. The posterior end bears a piriform side, whereas the anterior surface bears a kidney-shaped facet. The medial floor is non-articular, while the lateral surface bears articular areas for the intermediate cuneiform and second metatarsal bones. The side of a given medial cuneiform can be determined with aforementioned data.
Syndromes
When pain is simply moderate, opioids and nonopioids could be given in a fixed-dose mixture formulation, thereby simplifying dosing. However, when pain is severe, these medication must be given separately as a result of, with a fixed-dose combination, unwanted effects of the nonopioid would turn out to be intolerable as the dosage grew large, and hence would limit how much opioid might be given. Drug remedy of cancer pain ought to adhere to the following ideas: � Perform a complete pretreatment evaluation to identify pain intensity and the underlying trigger. Accordingly, if a affected person has intense pain at the outset, then remedy may be initiated with an opioid (step 2), quite than making an attempt a nonopioid first (step 1). Magnesium salicylate is nonacetylated, and hence, in contrast to aspirin, is safe for patients with thrombocytopenia. Because of this distinction and others, acetaminophen is taken into account individually beneath. Primary beneficial effects are pain reduction, suppression of irritation, and discount of fever. Primary adverse results are gastric ulceration, acute renal failure, and bleeding. Many anticancer medicine suppress bone marrow perform, and thereby decrease platelet manufacturing. Aspirin should be averted because it causes irreversible inhibition of platelet aggregation. Combining acetaminophen with an opioid can produce larger analgesia than either drug alone (because acetaminophen and opioids relieve ache by totally different mechanisms). Acetaminophen has important interactions with two different medication: alcohol and warfarin (an anticoagulant). The mechanism seems to be inhibition of warfarin metabolism, which causes warfarin to accumulate to toxic levels. Opioid Analgesics Opioids are the simplest analgesics out there, and therefore are the first drugs for treating moderate to severe cancer pain. With correct dosing, opioids can safely relieve ache in about 90% of cancer sufferers. Unfortunately, many patients are denied enough doses, owing largely to unfounded fears of habit. With continuous use, tolerance develops to most of those results, with the notable exceptions of constipation and miosis. Continuous use additionally leads to physical dependence, which should not be equated with dependancy. Tolerance can be defined as a state in which a specific dose (eg, 10 mg of morphine) produces a smaller impact than it may when treatment started. Put another way, tolerance is a state during which dosage must be elevated to maintain the desired response. Accordingly, vital tolerance to one opioid confers an identical degree of tolerance to all others. Physical dependence is a state during which an abstinence syndrome will happen if a drug is abruptly withdrawn. The intensity and duration of the abstinence syndrome are decided partially by the duration of drug use and partially by the half-life of the drug taken. Because medicine with a brief half-life depart the physique rapidly, the abstinence syndrome is transient but intense. Conversely, for medicine with lengthy half-lives, the syndrome is prolonged however comparatively delicate. The abstinence syndrome may be minimized by withdrawing opioids slowly (ie, by giving progressively smaller doses over several days). Mechanism of Action and Classification Opioid analgesics relieve ache by mimicking the actions of endogenous opioid peptides (enkephalins, dynorphins, endorphins), primarily at mu receptors and partly at kappa receptors. Based on their actions at mu and kappa receptors, the opioids fall into two major groups: (1) pure (full) agonists (eg, morphine) and (2) agonist-antagonists (eg, butorphanol). The pure agonists can be subdivided into (1) brokers for mild to reasonable pain and (2) brokers for average to extreme ache. In distinction, the agonist-antagonists act as agonists only at kappa receptors; at mu receptors, these medicine act as antagonists. Because their agonist actions are restricted to kappa receptors, the agonist-antagonists have a ceiling to their analgesic effects. Furthermore, due to their antagonist actions, the agonist-antagonists can block entry of the pure agonists to mu receptors, and may thereby stop the pure agonists from relieving pain.

Also, they want to be informed that hypotension could be minimized by shifting slowly when assuming an erect posture. For the hospitalized patient, blood stress and pulse rate must be monitored on an everyday schedule (eg, 4 instances daily). These measurements should be taken whereas the patient is lying down and again after the patient has been sitting or standing for 1 to 2 minutes. Hypertensive disaster is characterized by extreme headache, tachycardia, hypertension, nausea, vomiting, confusion, and profuse sweating-possibly leading to stroke and death. Patients should be knowledgeable about the signs of hypertensive disaster (headache, tachycardia, palpitations, nausea, vomiting, sweating) and instructed to search immediate medical attention if these develop. Options embody sodium nitroprusside (a nitric oxide donor), phentolamine (an alpha-adrenergic antagonist), and labetalol (an alpha/beta-adrenergic antagonist). Patients should be instructed to keep away from all sympathomimetic medication, together with ephedrine, methylphenidate, amphetamines, and cocaine. Sympathomimetic agents may be current in chilly cures, nasal decongestants, and asthma medications; all of these ought to be averted unless permitted by the prescriber. Clinical trials have shown that proscribing dietary tyramine is unnecessary with low-dose selegiline (24 mg/24 hr). These medication have to be used with caution because their effects might be more intense and extended. However, although doubtlessly dangerous, the mixture can benefit certain patients. Two drugs-carbamazepine [Tegretol] and oxcarbazepine [Trileptal]-can significantly increase levels of selegiline. The most common opposed response is localized rash, which develops in about one-third of sufferers. Selegiline transdermal patches are available in three strengths, delivering 6, 9, and 12 mg over 24 hours. Application is finished each 24 hours to intact, dry pores and skin of the higher torso, higher thigh, or outer floor of the higher arm. If necessary, dosage could additionally be elevated to 9 mg/24 hr, after which to 12 mg/24 hr after a minimum of two weeks on the decrease dose. For treatment of depression, bupropion is on the market as two salts: bupropion hydrochloride and bupropion hydrobromide. Bupropion hydrochloride marketed for smoking cessation is available in 150-mg sustained-release tablets offered as Zyban and Buproban. In addition to its use in despair, bupropion, marketed as Zyban and Buproban, is accredited as an aid to quit smoking (see Chapter 39). Unlabeled uses embrace relief of neuropathic pain, therapy of depressive episodes in bipolar disorder, and management of attention-deficit/hyperactivity disorder. Bioavailability is low: In animals, only 5% to 20% of each dose reaches the systemic circulation. In addition, bupropion carries a small threat of causing psychotic symptoms, together with hallucinations and delusions. Like other antidepressants, bupropion might increase the chance of suicide in youngsters, adolescents, and Actions and Uses. Bupropion [Wellbutrin, Budeprion, Mirtazapine Mirtazapine [Remeron] is the primary representative of a new class of antidepressants. The mechanism is blockade of presynaptic alpha2-adrenergic receptors that serve to inhibit release. Mirtazapine blocks histamine receptors, and thus promotes sedation and weight achieve. Mirtazapine is nicely absorbed following oral dosing and reaches peak plasma ranges in 2 hours. Whether these experiences are due to differences in the formulations or are only a coincidence has not been established.
The subcutaneous prepatellar bursa can get infected (bursitis) in individuals just like the housemaids and ground staff who support their weight on the knees for long intervals. The deep infrapatellar bursa is between the ligamentum patellae and the tibial tuberosity. Overuse of the ligamentum patellae or the quadriceps leads to friction between the tendon and the tibia leading to deep infrapatellar bursitis. Upper end of origin from ramus of pubis m Posterior side of femur: � Along a line operating from lesser trochanter to linea aspera � Upper a half of linea aspera f. The profunda femoris vessels and the anterior division of the sf re e Additional Notes on Adductor Brevis re r co of the tr angle. The profunda femoris vessels, and the anterior division of the obturator nerve, lie deep to it. Near the insertion of the muscle, there are a series of osseoaponeurotic apertures for passage of blood vessels. The first and second perforating arter es (or generally only the second) pierce the muscle near its femoral attachment. The upper border of the adductor magnus may fuse with the lower border of the quadratus femoris. The superior a half of the adductor magnus muscle has fibres originating from the pubic ramus and inserted into the gluteal tuberosity. This half is in an anterior airplane compared to the the rest of the muscle and is recognized as the adductor minimus. Adductor magnus is usually described as a muscle of both the medial and the posterior compartments. It extends from the apex of the femoral triangle to an osseofibrotic opening within the adductor magnus through which the femoral vessels move into the popliteal fossa (the opening is often called the adductor hiatus). The canal is triangular in cross-section; its partitions are formed as follows: Anterolaterally by the vastus medialis; Anteromedially by a strong fibrous membrane (vastoadductor fascia) extending from the adductors to the vastus medialis and mendacity deep to sartorius; Posteriorly by the adductor longus (above) and the adductor magnus (below). It ought to be remembered that the vastus medialis inserts into the medial lip of linea aspera within the center third of the thigh. The adductor longus and adductor magnus also insert into the linea aspera immediately lateral to the insertion of vastus medialis. As the main bulk of the vastus medialis curves anteriorly and the adductors curve posteriorly, a muscular gutter is created between the two. The vasoadductor fascia stretches between the medial side of vastus medialis to the adductors thus changing the gutter into a canal. The robust membrane is strengthened by the presence of the sartorius muscle superficial to it. Both nerves are derived from the anterior divisons of the lumbosacral plexus and thus indicate a flexor origin for each elements of the muscle. Testing of the adductors: With the individual in supine place and the knee extended, the adductors are examined by making the person carry out adduction of thigh against resistance. This artery sends main branches to provide the gracilis, adductor longus and brevis these branches kind pedicles of musculocutaneous flaps involving the involved muscle tissue. Additional blood provide to these muscles is thru branches of femoral or medial circumflex femoral or obturator arteries. Adductor magnus receives abundant blood provide from branches of profunda, medial circumflex femoral and femoral arteries on the anterior aspect and from branches of popliteal, medial circumflex and perforating arteries on the posterior facet. The gracilis muscle is used in a number of muscle transplantation and alternative methods. It is used (along with its blood and nerve supply) to substitute any damaged muscle in the hand thus restoring digital capabilities. Strain, tears or avulsion tears of the adductor muscles typically happen at their proximal attachments in aggressive sports activities. The riders actively and continuously adduct their thighs to hold themselves secure on the animals; friction is produced leading to ossification of the tendons or formation of small bones.
Stejnar, 37 years: When switching from oral to rectal administration, dosing is begun with the same dose that was used orally, and then adjusted as needed. The two nerves are the medially positioned tibial nerve and the laterally placed frequent peroneal nerve (Greek.
Lukjan, 63 years: Specifically, whereas the control rabbits slept a median of sixty seven minutes, the pretreated rabbits slept solely 30 minutes-less than half the sleeping time seen in controls. Because of their outstanding anticholinergic actions, these medicine can tremendously improve the antimuscarinic results of atropine and related agents.
Hector, 28 years: A tough groove known as the preauricular sulcus is usually found (especially in females) on this area. Asthma is a continual situation characterized by irritation and bronchoconstriction occurring in response to a big selection of stimuli.
Quadir, 59 years: First, along with activating mu opioid receptors, tapentadol blocks reuptake of norepinephrine, just like tramadol, discussed beneath. Disruption of autonomic perform can produce a selection of symptoms, together with constipation, urinary incontinence, drooling, orthostatic hypotension, cold intolerance, and erectile dysfunction.
References

Desarrolló: Grupo Guadalupe S.R.L.