
Fiona M Reid MD MRCOG
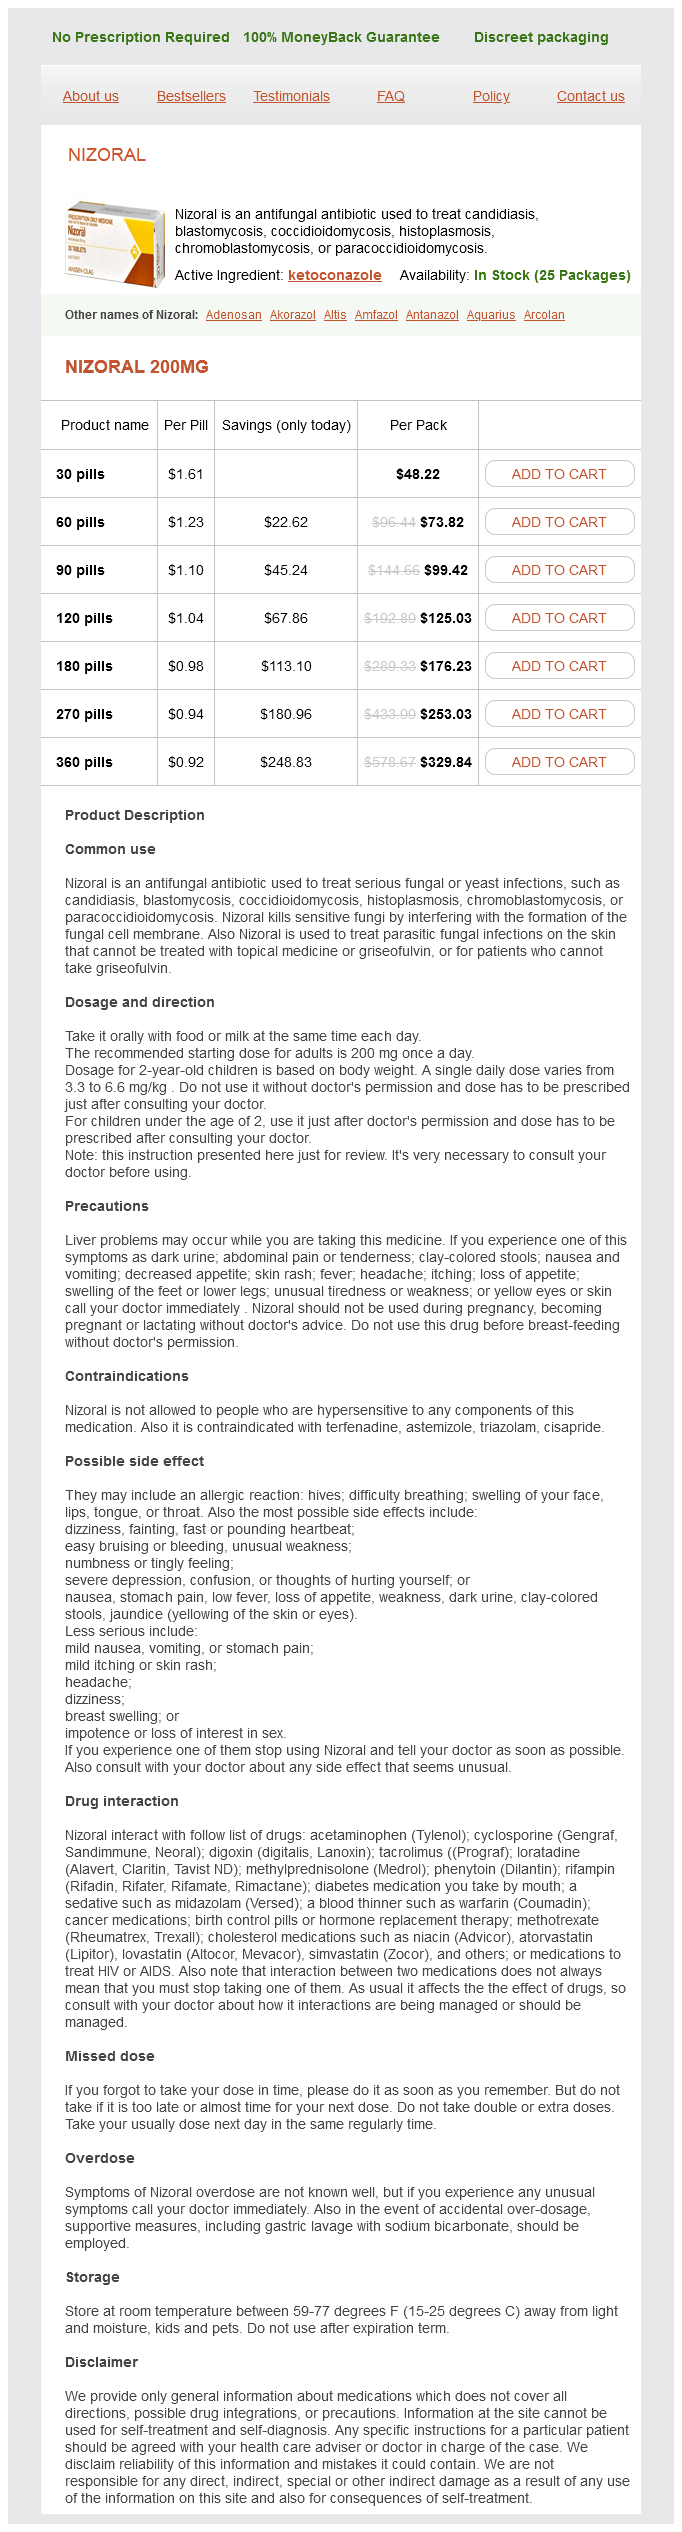
Ketoconazole dosages: 200 mg
Ketoconazole packs: 30 pills, 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills

This plain film of the hand reveals multiple punched-out lesions that are characteristic of osseous sarcoidosis. Peripheral adenopathy happens commonly at time of disease presentation, and bulky adenopathy may persist in ~10% of cases. Anemia, lymphopenia, and leucopenia may be noticed in 30% to 50% of all instances and is extra common than thrombocytopenia. A polyclonal gammopathy can also be regularly seen (~25%) in many patients with lively sarcoidosis. Cardiac sarcoidosis is a rare but important manifestation that can result in coronary heart block, malignant arrhythmias, and cardiomyopathy. Autopsy collection recommend that the incidence of cardiac sarcoidosis could additionally be as excessive as 25%, however clinical diagnoses of this condition are made in <10% of sufferers. Endomyocardial biopsy detects granulomatous inflammation in less than 25% of cases (20). Cranial neuropathies, often associated with an aseptic basilar meningitis, are probably to recur intermittently. This complication is potentially disabling and infrequently unresponsive to glucocorticoids. A small fiber neuropathy has been implicated lately as a major reason for chronic ache and fatigue in sarcoidosis (21). Such lesions, sometimes located within the bones of the arms and feet, can additionally be discovered within the cranium and vertebrae. Lesions involving the pelvis may be associated with pain that mimics sacroiliitis (16). Bone biopsies may be essential in osseous sarcoidosis to exclude infections or cancers which will end in similar radiographic findings. Myositis Random muscle biopsies may reveal granulomas in 50% to 80% of instances, but muscle involvement in sarcoidosis is often asymptomatic. Glucocorticoid-induced myopathy must be considered in patients who develop acuteonset weak point following the initiation of remedy. Abdominal Granulomatous inflammation could also be detected in more than 50% of liver biopsies in sarcoidosis, however clinically important liver disease is present in not more than 10% of all cases. Elevated liver enzymes typically resolve spontaneously or with therapy with glucocorticoids. Classic findings related to sarcoidosis revealed by 67-gallium scanning embrace uptake in the parotid and lacrimal glands ("panda sign") and uptake in bilateral hilar and proper paratracheal lymph nodes ("lambda signal"). Although these radiographic findings are highly typical of sarcoidosis, a biopsy remains to be required to confirm prognosis. Serum levels of angiotensin-converting enzyme and the energetic form of vitamin D (1,25-dihydroxy vitamin D3) are elevated in some sufferers with active sarcoidosis, however these test results have poor specificity and little utility in either the prognosis or administration of sarcoidosis (23). These granulomas are usually noncaseating, although fibrinoid necrosis can often be seen. Chest radiograph (A) appropriate with Scadding stage I, demonstrating bilateral hilar and right paratracheal adenopathy with out significant parenchymal infiltrates. This patient presented with constitutional signs (fevers, unintentional weight loss), arthralgias, and a cough. Computed tomography scans of the chest, revealing patchy, diffuse reticulonodular infiltrates predominantly involving the higher and middle lung fields with a bronchovascular distribution. Oligoclonal enlargement of T cells bearing a restricted set of T-cell receptors in the lung, skin, and different websites of disease assist the hypothesis that sarcoidosis includes an antigen-driven response (25). The most compelling example of this is the over-representation of T cells bearing the V alpha 2. Thus, sarcoidosis differs from many rheumatological ailments in that waxing and waning courses with intermittent flares and remissions are unusual. The main exception to this rule is the neurosarcoidosis presentation of optic neuritis and cranial neuropathies, which can recur several years after apparent remission.
The nerve block is maintained with a continuous infusion of local anes� thetic brokers. Trauma � Surgical emergencies might require general anesthesia earlier than finishing radiologic evaluations. An uncleared cervical spine requires in-line handbook stabilization during the endotracheal intubation, no matter Table 1 Facton Associated wi1h Difficult Endotracheal Intubation Anatomic: abnonnalities: miaognathia, restricted jaw or ned. Table three Local Anesthetic Lidocaine Prilocaine Mepivacaine Bupivacaine Ropivacaine 1 Pediatric Doses of Clinical O. Table 5 Procedure Shoulder surgery Elbow surgical procedure Nerve Blocks for Surgery Block lnll! Table four Medication American Society of Regional Anesthesia Guidelines for Anticoagulation Discontinuation Recommendation No discontinuation No discontinuation 14 days No discontinuation Stop and 1 hour after block. Interscalene blocks with bupivacaine or ropivacaine provide perioperative analgesia. Interscalene blocks trigger a sympathectomy and resultant redistribution of blood away from the surgical website, lowering intraoperative blood loss. The semisitting and lateral decubitus positions place the operative website above the center, hardly ever leading to air embolism. However, the anesthesiologist could also be hampered by this position h�:ause the proximity of the surgical incision allows little access to the pinnacle. Because of this potential drawback, many anesthesiologists and surgeons alike prefer to use common anesthesia with an endotracheal tube together with an interscalene block. This combined anesthetic would even be chosen with sophisticated reoperations or the place induced hypotension is needed. Typically forty eight hours of postoperative ache is sufficient, and catheters are then eliminated. Prolonged interscalene analgesia may be required in acute surgical shoulder pain in the continual ache affected person or in a patient with a frozen shoulder requiring mobilization remedy. These might end in transient loss of ipsilateral diaphragm perform, weak voice, miosis, ptosis, and anhydrosis (Homer syndrome). Elbow Surgery � Surgical procedures on the elbow, whether for arthroplasty or the reattachment of a biceps brachii tendon, frequendy require general anesthesia despite some great benefits of regional anesthesia. Regional teclullques are often carried out in the recovery area after nerve function is assessed. Continuous infraclavicular blocks are ideal as they cover the brachial plexus, including the musculocutaneous nerves, offering anesthesia of the entire arm. This might end in pain throughout steady passive motion and it could need to be individually blocked. The block may be placed easily, sets up shortly, covers the entire nerves of the hand, and is associated with low complication charges. The success of the block may be predicted by confirming circumferential spread of local anesthetic across the nerves. Supplementing Nerve Blocks � It is preferable to place blocks outside the working room so that block efficacy can be evaluated. Continuous Nerve Blocks � Postoperative pain management after a single inj&:tion of local anesthesia is restricted to sixteen hours, and this limits ita usefulness for postoperative pain management. In a procedure associated with moderate to severe postoperative ache, patients experience vital ache when the block resolves. Undertreated ache may lead to more refractory ache states, corresponding to continual pain or advanced regional pain syndromes. The catheter is positioned and local anesthetic administered preoperatively and mixed with other analgesic interventions. To ensure success with home-going regional anesthesia, directions and instructing must begin in the preoperative interval. They are instructed to avoid working with excessive heat or cold and to keep away from driving. Patients are educated about signs of local anesthetic toxicity, and phone numbers are supplied with instructions to call in the occasion of problems.

These grownup relationships are more probably to affect present psychological functioning as a lot as childhood abuse and neglect (27). The association between bodily pain and social connectedness has been demonstrated in patients with rheumatic diseases. One study demonstrated decreased sensitivity to pain in fibromyalgia patients when in the presence of their important different (28). Interestingly, these outcomes were detected by decreased exercise in brain areas associated with pain, as nicely as in decreased reports of pain, in response to thermal stimulation. Relationships usually have each helpful and dangerous elements, and each of those dimensions impression response to stress in addition to pain experience (29). Instead, the characteristics of those assets and the flexibility to utilize these sources, notably throughout instances of stress, is a strong determinant of well being and well-being. Interpersonal stress, depression, and disease activity in rheumatoid arthritis and osteoarthritis sufferers. The affiliation between tenderpoints, psychological misery, and adverse childhood experiences: a community-based study. Prevalence and influence of posttraumatic stress disorder-like symptoms in sufferers with fibromyalgia syndrome. Abuse-related posttraumatic stress dysfunction and alterations of the hypothalamic-pituitary-adrenal axis in girls with continual pelvis pain. Depression and reactivity to stress in older women with rheumatoid arthritis and osteoarthritis. Coping with persistent arthritis ache in daily life: within-person analyses reveal hidden vulnerability for the formerly depressed. Neuroticism and the pain-mood relation in rheumatoid arthritis: insights from a prospective every day research. Resilience connotes each the flexibility to protect towards the detrimental impression of stress as nicely as to get well from tense occasions. Most importantly, resilience seems to be more the rule than an exception to the rule. In truth, Masten, in referring to how youngsters survive probably the most troublesome childhoods, describes resilience as "odd magic," involving readily accessible human adaptational methods somewhat than extraordinary and unusual capabilities (30). This is true for rheumatic sufferers as properly, many of whom adapt and manage their ache expertly. For people who encounter difficulty, behavioral interventions may be most successful when assisting people in accessing sources that they have already got rather than focusing on deficits in psychosocial functioning. Attentional functioning in fibromyalgia, rheumatoid arthritis, and musculoskeletal ache sufferers. Childhood trauma, the neurobiology of adaptation and use-dependent growth of the mind: how states turn out to be traits. Adult attachment: A mediator between childhood sexual abuse and later psychological adjustment. Influence of social assist and emotional context on pain processing and magnetic mind responses in fibromyalgia. Vulnerability to stress among ladies in chronic ache from fibromyalgia and osteoarthritis. Evidence suggests that very few individuals with arthritis take part in self-management training. Self-management actions, similar to participation in teaching programs and physical activity, are central to the nonpharmacological administration outlined in American College of Rheumatology tips for arthritis administration. While people with arthritis try quite a lot of strategies to live properly with their illness, scientific proof supports only a limited variety of key self-management activities. This chapter evaluations the evidence base for the three self-management strategies with the broadest applicability: participating in self-management schooling, maintaining regular, reasonable intensity bodily exercise, and controlling weight. This chapter will conclude with suggestions for bettering the effectiveness of clinician counseling by way of the usage of a short behavioral counseling model to help sufferers in working towards self-management. Much of the traditional affected person training emphasizes providing information about the illness and its remedy, utilizing verbal instruction supplemented by handouts and pamphlets. A meta-analysis of arthritis education trials demonstrated that training interventions that included behavioral techniques produced considerably higher improvements in ache, function, and tender joint counts than did info dissemination interventions (2). Several studies have demonstrated shortterm (3�6 month) data change, but no change in health status (1). Evidence-based self-management training could be provided individually or in small teams.

The neurovascular bundles are in the volar third and will, after all, be averted when the discount clamp is applied. Reduction can additional be fine-tuned by twisting the clamp slightly when tightening. Note the importance of the lateral radiograph to assess the displacement of the middle finger fracture. The ring finger was fiXed with a single pin to avoid displacement after early movement was began. Drill transverse and anteroposterior holes 2 to 5 mm away from the fracture site utilizing a 0. Most often, the midaxial approach will present the best publicity with the least amount of sentimental tissue stripping. To acquire a lag impact, the near cortex is opened to the outer diameter of the screw (overdrilled) so the screw threads will have interaction solely in the far cortex. Alternatively, cut back the fracture with a clamp, then stabilize it with a Kirschner wire smaller than the core diameter of the screw. Lateral placement via the midaxial strategy has the advantage of much less extensor disruption and doubtlessly fewer adhesions. Assess the size, angulation, and most significantly the rotation dinically and radiographically. Preoperative posteroanterior and lateral radiographs showing a comminuted index finger proximal phalanx fracture with significant shortening, angulation, and rotation, and a middle finger proximal phalanx fracture with affordable alignment. Rather than risking extra vascular compromise to the middle finger with pins or open discount. Active movement of each fingers was began 1 week after open discount and internal fiXation. If adequate fracture stabilization is obtained, then mobilization of the concerned digit is started virtually instantly. Protected mobilization should embrace detachable splints that permit motion of adjoining digits and joints. If the issue persists and regardless of good therapy passive motion greatly exceeds lively movement, tenolysis is a reliable method of remedy. Inserting the wires initially by hand till bone contact is made and using small open incisions could lower the possibility of harm when inserting the wire close to the neurovascular bundle. Complications of smooth pin fixation of fractures and dislocations in the hand and wrist. Point/counterpoint: closed discount and internal fixation versus open reduction and inremal fixation for displaced indirect proximal phalangeal fractures. A comparative mechanical evaluation of plare fixation in a proximal phalangeal fracture mannequin. The conservative management of proximal phalanx fractures of the hand in an accident and emergency department. External fixation of closed metacarpal and phal~al fractures of digits: a potential research of 100 consecutive patients. Tension band wiring of unstable transverse fractures of the proximal and center phalauges of the hand. Care have to be taken not to disrupt this blood supply or to strip amall fragments of their delicate tissue attachments. Table 1 Fracture Configuration Type 1: unicondylar brief oblique Condylar Fracture Pattems Fixation Illustration Characteristics Unstable Fracture exits simply prQ)Qmal to collateral ligaments Deformity is indirect to coronal Sid sagittal planes Nondisplec:ed Fractunt Could contemplate nonopetative treatmeflt, but should follow dosely. The affected person typically is still in a place to bend the finger, and the fracture line could be refined, but even nondisplaced fractures are prone to subsequent displacement. Osteochondral fragments usually are bigger than they seem, because the cartilage is radiolucent. Observation of the fingers in full extension can reveal subtle angular deformities caused by a displaced condyle. However, by the time they obtained off the ready listing their signs had subsided to the purpose that they declined surgical procedure.

Patients with rheumatoid arthritis are extra tender than those with psoriatic arthritis. Psoriatic spondylitis: a clinical and radiological description of the spine in psoriatic arthritis. The cervical spine in patients with psoriatic arthritis: a clinical, radiological and immunogenetic study. The prevlance of sacroiliitis in psoriatic arthritis: new views from a big, multicenter cohort. Differences in the expression of spondyloarthropathy: a comparison between ankylosing spondylitis and psoriatic arthritis. Development of an assessment software for dactylitis in sufferers with psoriatic arthritis. Distal extremity swelling with pitting edema in psoriatic arthritis: a casecontrol research. Distal extremity swelling with pitting edema in psoriatic arthritis: proof of 2 pathological mechanisms. Isolated peripheral enthesitis and/or dactylitis: a subset of psoriatic arthritis. Baseline relationships between psoriasis and psoriatic arthritis: evaluation of 221 sufferers with active psoriatic arthritis. Psoriatic arthritis: interrelationships between skin and joint manifestations related to onset, course and distribution. Microscopic inflammatory adjustments in colon of patients with each lively psoriasis and psoriatic arthritis with out bowel signs. Cardiovascular risk profile of patients with spondylarthropathies, particularly ankylosing spondylitis and psoriatic arthritis. A potential, scientific and radiological research of early psoriatic arthritis: an early synovitis clinic expertise Rheumatology 2003; forty two:1460�1468. Longitudinal study of scientific and radiological development in psoriatic arthritis. A polyarticular onset predicts erosive and deforming disease in psoriatic arthritis. Measuring well being standing in psoriatic arthritis: the Health Assessment Questionnaire and its modification. Comparison of incapacity and high quality of life in rheumatoid and psoriatic arthritis. Healthrelated high quality of life of sufferers with psoriatic arthritis: a comparability with patients with rheumatoid arthritis. Description and prediction of bodily functional incapacity in psoriatic arthritis (psa): a longitudinal evaluation using a Markov mannequin approach. Did mortality price improve in psoriatic arthritis (PsA) patients in the final decade Prospective analysis of psoriatic arthritis in sufferers hospitalized for psoriasis. Frequency of psoriatic arthritis in general inhabitants and among psoriatics in division of dermatology. Psoriatic arthritis (PsA) is common among sufferers with psoriasis and family medical clinic attendees. Inflammatory joint manifestations are prevalent in psoriasis: prevalence research of joint and axial involvement in psoriatic patients, and evaluation of a psoriatic and arthritic questionnaire. Psoriatic arthritis is triggered by interaction between genetic and environmental factors with initiating occasions occurring in the pores and skin and/or gut. Inflammation can goal a range of musculoskeletal constructions, together with the axial skeleton, peripheral joints, attachment sites of ligaments, tendons or joint capsules onto bone (entheses), and tendon sheaths. Joint manifestations could additionally be extremely localized and gentle in some sufferers, whereas others might expertise widespread irritation and harm that ends in important functional decline. Joint dysfunction can come up not solely because of bone resorption and cartilage degradation, but additionally from diffuse gentle tissue irritation (dactylitis) and new bone formation within the type of ankylosis or periostitis. At the histologic and ultrastructural stage, psoriatic syno178 vial vasculature displayed endothelial cell swelling, inflammatory cell infiltration, and marked thickening of the vessel wall (2). The infected synovial membrane or pannus, comprised of fibroblastoid cells and activated macrophages, is invasively destructive.

Gea (Kava). Ketoconazole.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96842
The dose of these agents must be escalated slowly over weeks; discontinuance of these agents ought to likewise be carried out gradually. Topical Agents Obtained from pink chili peppers, topical capsaicin binds to vanilloid receptors on peripheral terminals of nociceptive neurons, thereby inhibiting activation of the pain pathway by noxious stimuli. Essentially freed from toxicity aside from delicate burning on the web site of software, capsaicin is useful as adjunctive remedy in diffuse and regional musculoskeletal ache syndromes, joint ache in arthritis, and in neuropathic pain issues. Up to three 5% lidocaine patches (Lidoderm) could additionally be applied to localized painful areas for 12 to 18 hours in a 24-hour interval with good efficacy and security. Other Pharmacological Agents Anxiolytics, for example, clonazepam (Klonopin), lorazepam (Ativan), temazepam (Restoril), alprazolam (Xanax), and buspirone (Buspar) have antinociceptive effects in chronic pain and are often used in combination with antidepressants and antiepileptic medication. Pramipexole (Mirapex, dopamine 3 receptor agonist) has been shown to enhance pain scores, fatigue, and performance in sufferers requiring opioids for pain control. Psychological and Behavioral Approaches the importance of methods in this area has been emphasized just lately (8,16). Depression, anxiety, stress, sleep disturbance, ache beliefs and coping methods, and self-efficacy all are central to the pain expertise in plenty of patients, and incessantly decide the finish result of persistent pain. The role of cognitive� behavioral remedy for the diffuse ache of fibromyalgia and related regional ache syndromes stays to be clarified. Heat and Cold Heat (hot packs, paraffin, hydrotherapy in its many forms) is of confirmed benefit in nociceptive ache, particularly when combined with exercise (range of motion, stretching, strengthening). Diffuse and regional pain is improved by such strategies as sauna, sizzling baths and showers, and sizzling mud. While not superior to superficial warmth, cold (cold packs, immersion, or vapocoolant sprays) might present extra quick analgesic profit, notably when applied soon after an damage. Injection of "trigger points" is of short-term benefit solely and should typically be averted. Neurophysiologic results of acupuncture and electroacupuncture embody release of opioids and other mediators in the nervous system. Several randomized, controlled trials have proven acupuncture to improve subjective ache and to elevate pain thresholds, but its long-term benefit in continual ache syndromes remains unclear. Physical Therapy/ Physical Modalities the goals here are to diminish ache, improve operate, decrease disability, and promote self-efficacy. Although sure strategies and modalities are clearly useful, this area wants correctly designed trials to set up efficacy. Exercise In addition to optimistic results on underlying pathological processes in bones, joints, and muscle tissue, exercise is crucial to the treatment of fibromyalgia and related persistent pain syndromes. The benefits of exercise, along with gains in cardiovascular health, muscle tone, and strength, embody enhancements in each subjective and goal measures of ache and in the overall sense of well-being. Many sufferers with chronic pain perceive their muscle tissue to be weak and simply fatigued, and bear the negative perception (fear) that exercise will exacerbate their situation. Excessive activity "on a great day" induces a serious flare of pain and fatigue, possibly due, partially, to the peripheral and central results of proinflammatory cytokines (tumor necrosis issue, interleukins 1 and 6) launched in response to exercise-damaged myofibers. Ideally, train should be low-impact (walking, water aerobics, stationary bicycle, somewhat than running), starting very gently and progressing progressively to endurance and strength coaching. Encouragement and optimistic reinforcement can cut back the virtually common downside of poor compliance. Obesity, poor posture, and overloading activities at work and residential also contribute to muscle pain and fatigue and ought to be addressed. Pain in Children Except for kids less than 1 12 months of age, the method to the management of ache in kids is similar to that in adults. In such cases, the doctor have to be sensitive and sensible, keep away from pointless testing, and emphasize life-style interventions, discount of faculty stressors, and aerobic exercise (see Ref. The use of opioids for average or extreme ache is acceptable, however dosing should follow the "begin low, go sluggish" maxim. The health care provider should concentrate on financial barriers that some aged patients confront in acquiring medicines. Nonpharmacologic therapy of ache in older persons should be an integral a half of care plans. Procedure-Based Pain Management Injection of native anesthetics, epidural techniques, and radiofrequency ablation procedures all have a spot in certain instances, however not sometimes are used inappropriately in anesthesia ache clinics.
Syndromes
Scarlett fever, periarteritis nodosa, aneurysm of the coronary artery with spontaneous rupture, hemopericardium. American Heart Association Committee on Rheumatic Fever, Endocarditis, and Kawasaki Disease. A statement for health professionals from the committee on rheumatic fever, endocarditis, and Kawasaki disease. Kawasaki disease: proceedings of the fifth International Kawasaki Disease Symposium. Results of 12 nationwide epidemiological incidence surveys of Kawasaki disease in Japan. Evidence for superantigen involvement in cardiovascular injury because of Kawasaki disease. Selective expansion of T cells expressing T-cell receptor variable regions V beta 2 and V beta eight in Kawasaki disease. Superantigenic exercise is liable for induction of coronary arteritis in mice: and animal model for Kawasaki illness. Intravenous IgG infusions are related to the in vitro inhibition of classical pathway-mediated lysis of sheep pink blood cells and a decrease in C4d levels in Kawasaki disease. Re-treatment of immunoglobulin-resistant Kawasaki disease: a comparative study of extra immune globulin and steroid pulse remedy. Corticosteroids within the preliminary treatment of Kawasaki illness: report of a randomized trial. Pentoxifylline and intravenous gamma globulin combination remedy for acute Kawasaki illness. Pharmacokinetics and tolerablility evaluation of a pediatric oral formulation of pentoxifylline in Kawasaki disease. Inflammation of cartilaginous buildings with lymphocytic infiltration and affiliation with anticollagen antibodies are according to an autoimmune pathogenesis. The characteristic clinical findings are acute painful swelling and redness of the exterior ear, nasal cartilage, and laryngotracheal cartilage. Nonerosive arthritis, ocular inflammation, vestibular symptoms, and involvement of the center and kidney additionally occur. Laryngotracheal involvement is a critical complication which will require tracheostomy. Relapsing polychondritis is a recurring inflammatory disorder of unknown etiology causing inflammatory reactions in the cartilaginous buildings of the nostril, ears, trachea, and the joints. It was first described by JakschWartenhorst (1), in a affected person with systemic illness characterized by exterior ear swelling, collapse of the nasal bridge, fever, and arthritis. Since then, this dysfunction has been described worldwide and happens in all age teams, though it peaks within the fifth decade. Over 30% of sufferers have an associated disorder, normally autoimmune or hematologic. Elevated levels of anticollagen antibodies and cell-mediated immunity to cartilage elements have been noticed (8,9). These observations are according to the thought that autoimmune mechanisms are involved in this disease. Recurrent inflammatory episodes lead to destruction of the exterior ear cartilage, leading to both a soft flopped ear or a firm fibrotic knobby ear. The exterior auditory canal may be stenosed by the inflammatory swelling and cause conductive deafness. About one third of the sufferers experience vestibular or auditory abnormalities of varying levels from vasculitis of the interior auditory artery (11). The severity of those relies upon upon the severity of the irritation of the tracheal cartilages. Inflammatory mononuclear cells infiltrate this region with occasional polymorphonuclear leukocytes with damage to the cartilage. Narrowing of the trachea, both localized or generalized, results in incapability to clear the throat, choking spells, and respiratory infections. These signs ought to be taken critically as a result of it is a potentially lethal complication. Respi- ratory symptoms of varying diploma could additionally be noticed in as a lot as 50% of sufferers (12). Signs and symptoms depend upon the type of involvement as well as the associated illness.

Patients with nondisplaced fractures often have appreciable pain and swdling in the forearm. Despite the convenience of initial diagnosis, the treating doctor must be on guard for important associated injuries and complications, not only of the bone and joint but also of soft tissue. A laceration could talk with the fracture web site; subsequently, a contaminated abrasion on the web site of surgical incision should be allowed to heal earlier than surgery. Fascia: Tense tissues to palpation over the flexor or extensor compartments and ache with passive finger extension are evidence of compartment syndrome, and compartment release should be considered. In the multiply injured patient, the peripheries are shut down, making capillary refill and pulses difficult to carry out. Bone: the joints above and under the fracture must be palpated for related joint disruption. Given the widespread affiliation with high energy, the affected person should be assessed in accordance with an applicable trauma guidelines protocol. Severe ache ought to suggest the risk of compartment syndrome or vascular injury. Forearm fractures occur relatively generally in some sports activities, eg, rugby in all its forms and wrestling. If this blow is directed primarily at the ulna, an isolated ulna shaft fracture outcomes ("nightstick" fracture). Palpation ought to be carried out of the medial and lateral epk:ondyles, of the s~aphoid within the snuff field, and over ~arpal bones and the carpometa~arpal joints. A systematic examination of the median, ulnar, and radial nerves entails examination of sensory and motor aspe~ts (Table 1). The sensory examination entails stati~ two-point dis~imination of the digital nerves and lightweight toud over the autogenous zones of ea~h nerve. Any shift within the ulnar head is a subluxation and, when ~ombined with a radius fracture, represents a Galeazzi fra~ture-dislocation. Median nerve autogenous zone Ulnar nerve autogenous zone Radial nerve autogenous zone First dorsal interosseous muscle! This surface is broad and flat on each bones, and a plate on this surface is roofed with muscle, resulting in much less plate irritation for the affected person. In addition, the affected person is positioned supine for these approaches, decreasing the want to reposition the affected person during the process. Use of two incisions markedly decreases the danger of synostosis, decreases the length of the incision, and reduces pressure on the pores and skin and delicate tissue by retractors. I recommend not completing fixation however stabilizing one bone before proceeding to the following. Completion of fixation should happen after the second bone is reduced and stabilized. Oblique fractures are handled with an inter� fragmentary screw or screws at proper angles to the fracture line and a seven-hole plate. In almost all situa� tions there have to be three screw holes within the plate over sta� ble bone away from the fracture complicated. In distal metaphyseal, diaphyseal fractures of the ulna, it typically is inconceivable to get six cortices of fixation. This location permits for excellent soft tissue coverage, re� ducing the need for plate removal. For a posterior strategy to the radius, the forearm is pronated and the elbow extended. Approach � the anterior method to the radius is the standard approach for a radius fracture, however the posterior strategy is helpful when delicate tissue lesions are posterior or the anterior strategy is compromised in some way. I favor an anterior method, however, because the anterior border of the ulna is flat. A straight metallic instrument is positioned on the forearm pores and skin, and a C-arm picture is taken to choose the position of the fracture. A straight metal instrument is positioned throughout the forearm, and a C-arm fluoroscopic picture is taken to affirm the extent of the fracture. The radial side of the pronator teres insertion is dissected off the radial shaft. I favor six cortices of screw fixation on both side of the fracture and currently use the Synthes Small Fragment Locking Compression Plates as fiXation.
Partial splenectomy has been recommended as protection in opposition to postsplenectomy an infection, and for its hepatic and bone-sparing impact. Arthroplasty and full joint replacement is commonly necessary, but loosening of prostheses occurs extra usually than in other problems. However, options to enzyme replacement remedy include substrate reduction, energetic site-specific chaperone remedy, and gene therapy (17). The latter involves using retroviral vector constructs for coding the gene for glucocerebrosidase into hematopoietic progenitors. It is an autosomal recessive dysfunction caused by a deficiency of the enzyme acid ceramidase. Affected children show disease manifestations by the age of four months and die before the age of 4 years. A hoarse cry from thickened vocal cords or swollen painful joints may be the first function. The appearance of tender, subcutaneous nodules follows and the early incidence of nodules correlates with shortened survival. All the extremities may be swollen and tender, however this provides method to more localized joint swelling with nodules around the fingers, wrists, elbows, and knees. The gastrointestinal, cardiovascular, and nervous techniques progressively become involved, and death outcomes from respiratory disease. Diagnosis may be confirmed by demonstrating a deficiency of ceramidase each in leukocytes and fibroblasts. Small papules and beadlike clusters around the nailfolds are characteristic, with pores and skin nodulation of the face and arms. Histiocytes present lipochrome pigment granulation and peripheral blood leukocytes exhibit impaired exercise. It is characterised by the mobile accumulation of glycolipidladen histocytes and multinucleated large cells in skin and joints (21). The commonest presentation is a painful damaging polyarthritis resembling rheumatoid arthritis, for which affected individuals could additionally be mistakenly treated. Although a self-limited form may be seen in childhood, grownup multicentric reticulohistiocytosis predominantly affects middle-aged girls. Early radiographs early on show "punched out" bony lesions resembling gouty tophi. Spinal involvement with erosions and subluxations together with atlanto-axial injury may occur. Treatment Spontaneous remission of skin and arthritis occurs in some instances, especially in childhood. In the remainder, corticosteroids or topical nitrogen mustard could enhance the skin lesions. Laboratory Features No specific laboratory abnormality has but been demonstrated, and the analysis is established by examination of biopsies of affected tissues. Triglycerides, cholesterol, and phosphate esters appear to be current in the lesion, suggesting either that histiocytes are stimulated to produce these substances or that it is a form of lipid storage illness. A lymphocytic origin for the enormous cells has been proposed because of the presence of T-cell markers, but multicentric reticulocytosis cells also stain for macrophage markers (21). Synovial fluid leukocyte counts vary from 220 to seventy nine,000 cells/mm3, with mononuclear cells predominating. Scanning the synovial fluid Wrightstained smear or wet preparation might reveal giant cells or giant, bizarre macrophages. The foregoing specific histologic picture of multicentric reticulohistiocytosis is quite different from the myofibroblast cells in a collagen matrix attribute of the cutaneous nodules and polyarthritis of fibroblastic rheumatism (22). Although the pathogenesis is unknown, hidden malignancy and tuberculosis have been implicated. Multicentric reticulohistiocytosis has additionally been implicated with a big selection of malignancies (21). A survey of 2,851 sufferers with hemochromatosis: symptoms and response to remedy. Liver injury in Italian sufferers with hereditary hemochromatosis is extremely influenced by hepatitis B and C virus an infection. Association of heterozygous hemochromatosis C282Y gene mutation with hand osteoarthritis. The ultrastructural and light microscopic examine of the synovium in ochronotic arthropathy.
Lee, 29 years: However, all of the patients developed antibodies to the murine monoclonal antibodies. High-dose immunosuppressive therapy for severe systemic sclerosis: preliminary outcomes.
Flint, 40 years: Thalidomide for extreme refractory ankylosing spondylitis: a 6-month open-label trial. Vaginal reconstruction has traditionally been challenging because of the paucity of available native tissue.
Hauke, 51 years: Open the ground of the sheath distally to expose the underlying volar wrist capsule. Telomerase exercise in human benign prostate tissue and prostatic adenocarcinomas.
Anog, 54 years: Currently, surgeons mostly perform fusions for treating degeneration of cervical and lumbar backbone, hand interphalangeal, first metatarsophalangeal, wrist, and ankle joints. Genetic variants and prostate cancer risk: candidate replication and exploration of viral restriction genes.
Ben, 48 years: Adaptive immune cells additionally signal to each other in addition to have interaction in autocrine stimulation. The preliminary emphasis on viewing the wrist from the dorsal aspea arose from the relative lack of neurovascular constructions as nicely as the familiarity of most surgwns with dorsal approaches to the radiocarpal joint.
References

Desarrolló: Grupo Guadalupe S.R.L.